
Key takeaways
- FOS describes related short-chain fructans, including sucrose-derived short-chain FOS and oligofructose made by hydrolyzing inulin; the preparations are not interchangeable
- Some trials report easier or more frequent bowel movements, but manufacturer involvement and unresolved product procurement limit the independent evidence
- A rise in fecal Bifidobacterium does not by itself establish less pain, better bowel function or protection from disease
- Gas, bloating and loose stools are relevant trade-offs, particularly for people sensitive to fermentable carbohydrates
- This audit did not establish a dependable FOS-alone treatment for IBS, inflammatory bowel disease or “gut repair”
FOS can change what intestinal microbes ferment. Whether that helps a particular digestive problem depends on the preparation, person and outcome. Under this review's strict funding screen, a generalizable digestive treatment benefit is not independently established. Confidence is high in the ingredient distinctions, but low in a reliable treatment benefit after commercial and unresolved evidence are set aside.
Contents
Evidence summary · What it is · Forms and grades · How it works · Hype versus evidence · Benefits by claim · What works · Risks · Interactions · Who should avoid · Studied doses · Laboratory evidence · Funding · Regulation · FAQs · Sources
Evidence summary
“Excluded” means ineligible for the independent benefit verdict, not disproved. Unknown funding or supply terms remain unknown. Clinical outcomes, laboratory findings and regulatory decisions answer different questions.
| Claim | Evidence | Source | Funding or conflict | Strength |
|---|---|---|---|---|
| Increases frequency with normal bowel function | Public review found a favorable frequency signal | AHRQ 2025 | Underlying commercial study dominated the frequency synthesis | Favorable review finding; independent estimate insufficient |
| Relieves ordinary adult constipation | Positive frequency signal with chicory oligofructose | Buddington 2017 | BENEO financed research and publication; company authors | Insufficient independent evidence; excluded |
| Helps constipation during peritoneal dialysis | Nine completers in a crossover experiment | Meksawan 2016 | University thesis grant; ingredient source and procurement unstated | Very uncertain; not independently verified |
| Treats infant constipation | Primary therapeutic-success comparison not significant | Souza 2018 | Public grants; FQF supply terms unresolved | Insufficient |
| Treats IBS | No overall symptom advantage in two distinct preparations | Olesen 2000; Azpiroz 2017 | Ferrosan; Beghin-Meiji plus public support and Tereos employees | No independent treatment claim established |
| Improves minor digestive discomfort | Symptom-intensity signal in a working population | Paineau 2008 | Ingredient-company authors; full financing incompletely stated | Insufficient independent evidence; excluded |
| “Balances” the microbiome | Increased fecal bifidobacteria in a dose-response experiment | Bouhnik 2006 | Eridania-Beghin Say grant | Surrogate finding; excluded from independent benefit verdict |
| Prevents diabetes through the gut | Primary HbA1c result negative despite microbial changes | Le Bourgot 2025 | Tereos funded and participated | Prevention not demonstrated |
| Treats active Crohn's disease | No clinical benefit and more withdrawals with a fructan blend | Benjamin 2011 | Charity grant plus BENEO-Orafti product support | Blend context only; excluded from FOS-alone inference |
What it is
Fructooligosaccharides, abbreviated FOS, are short chains containing fructose units. Inulin-type fructans have bonds that resist digestion by human small-intestinal enzymes. “Short-chain” is a chemical description, not a guarantee of gentleness.
Two manufacturing routes matter. Enzymatic synthesis from sucrose produces mixtures commonly rich in 1-kestose, nystose and fructofuranosylnystose. Partial hydrolysis of inulin produces oligofructose with a different distribution of molecules. Longer-chain inulin, whole chicory and mixed-fructan products require their own evidence. FDA chemistry review, section III
Terminology varies between papers and labels. There is no single universal chain-length cutoff that makes every product called FOS equivalent. The actual composition and manufacturing route are more useful than a convenient abbreviation. This article discusses both short-chain forms while identifying which was tested; it does not import all inulin findings into the FOS verdict.
Forms and grades
| Form | What to identify | Why the distinction matters |
|---|---|---|
| Sucrose-derived scFOS | Manufacturing route, composition, active-fiber percentage | A study of Actilight-type scFOS does not test every chicory preparation |
| Hydrolyzed-inulin oligofructose | Source plant and molecular distribution | Orafti P95 and the older Idolax intervention belong to this branch |
| Inulin plus oligofructose | Amount and ratio of each component | A response to the combination cannot be assigned to FOS alone |
| Synbiotic or multi-fiber product | Probiotic strains, other fibers and sweeteners | Co-ingredients create additional explanations for benefits and symptoms |
| Food, syrup or flavored powder | Grams of actual FOS, sugars and other ingredients | A scoop or gram of finished product need not equal a gram of FOS |
These are formulation categories, not a brand ranking. The Olesen methods identify hydrolyzed-chicory Idolax; the Azpiroz methods identify sucrose-derived scFOS. Specifications can change, so historical trademarks are not sufficient to establish a match with a current retail product.
“Premium,” “clinical grade” and “natural” do not establish clinical superiority. Batch testing can address identity, purity or contaminants when its methods and results are available; it cannot establish symptom relief by itself.
How it works
Undigested fructans reach intestinal microbes that can use them as substrates. Fermentation can change microbial biomass, metabolites and gas production. Those processes provide a plausible route to changes in stool characteristics, but the direction and clinical importance are not guaranteed for an individual.
For example, a small manufacturer-funded study tested 2.5–10 g/day scFOS and reported a bifidobacterial response. It did not establish treatment of a bowel disease. Bouhnik 2006
A causal chain has several separate steps: the ingredient must reach the relevant organisms, change something biologically meaningful, and improve an outcome that matters to the person. A fecal bacterial count completes only part of that chain. Stool samples also do not directly measure every event along the intestine.
Microbial diversity is particularly easy to oversell. Higher diversity is not an automatically beneficial response to every intervention, and enrichment of a selected organism can change a diversity score without establishing better or worse health. Trials need to connect these changes with symptoms, functioning or disease outcomes rather than treating a preferred microbiome pattern as the endpoint.
Hype versus evidence
“Feeds good bacteria.” Some microbes can use FOS, and trials report compositional changes. The marketing phrase leaves out whether those changes improve the buyer's actual problem.
“Clinically proven for regularity.” The claim needs a named preparation, appropriate population, placebo comparison, meaningful outcome and complete funding record. A result for one oligofructose powder cannot validate every scFOS supplement.
“Works because it causes gas.” Gas is a tolerability outcome. It is not a validated sign that a supplement is repairing the gut, and persistent discomfort is not something that must be endured for a supposed detoxification phase.
“Better tolerated than inulin.” A Tereos-funded observational study reported mild average symptoms during short escalating exposures in healthy volunteers. It had no direct inulin-comparison arm. Its favorable interpretation cannot establish head-to-head superiority or a safe upper limit for people with IBS. Le Bourgot 2022
“The regulator recognizes it, so it treats my condition.” Ingredient safety, permission to count dietary fiber on a label and authorization of a specific health claim are separate decisions. None is blanket approval to treat digestive disease.
Benefits by claim
Adult constipation and regularity Insufficient independent evidence
A publicly commissioned 2025 AHRQ review reached a favorable conclusion for people with normal bowel function: moderate strength of evidence for increased stool frequency with added FOS. Its frequency meta-analysis was dominated by a small high-dose study. That study’s authors were all at Numico Research, so the pooled finding does not become a commercially independent estimate under this article’s rule. It also does not establish treatment for every constipation disorder. AHRQ results, section 3.10, Scholtens 2006 primary report The review’s public funding and methods are described in its 2026 publication.
Buddington's 97-person oligofructose trial found a frequency advantage at the highest tested phase, without a corresponding stool-consistency improvement. It enrolled otherwise healthy adults reporting irregularity and low fiber intake. BENEO paid for the work and publication, and reserved rights to use the data for health-claim applications. Primary trial
Frequency alone is not the whole treatment goal. Comfortable passage, incomplete evacuation, rescue-laxative use and quality of life also matter. Study entry based on reported infrequency is not equivalent to every cause of chronic constipation.
The university-supported Meksawan crossover trial reported better bowel outcomes in older peritoneal-dialysis patients. Only nine completed it; product identity/procurement were insufficiently described, and several medicines were withdrawn under study supervision. Its narrow result cannot justify replacing a renal patient's prescribed bowel regimen. Meksawan 2016
Infant constipation Insufficient
Souza randomized 38 infants and analyzed 36 completers. Therapeutic success was 83.3% versus 55.6%, but the primary comparison did not reach significance even using a one-tailed test. Some secondary measures favored FOS. Public CNPq/CAPES funding was declared; “supplied” product from FQF does not reveal whether it was purchased or donated. Souza 2018
A promising secondary outcome cannot erase an inconclusive primary result. These data do not establish a home treatment for infants, and formula blends containing several oligosaccharides answer a different question.
IBS and minor functional bowel symptoms Insufficient
The Ferrosan-supported Olesen trial used hydrolyzed-chicory oligofructose, with 98 randomized participants. Early symptoms were less favorable than placebo; after 12 weeks there was no significant overall benefit. That result concerns its particular preparation and exposure. Olesen 2000
Azpiroz's sucrose-derived scFOS trial likewise did not demonstrate superior overall IBS or quality-of-life improvement. Reported anxiety and microbial signals do not convert it into a proven IBS treatment. Beghin-Meiji funding and Tereos-employed authors make it commercially involved despite accompanying Spanish public funding. Azpiroz 2017
Paineau reported a symptom-intensity signal in 105 randomized adults with minor complaints. Compliance limitations and manufacturer-affiliated authors temper interpretation. A mildly symptomatic working population should not be equated with all diagnosed IBS patients. Paineau 2008
Microbiome changes and gut repair — Clinical benefit unestablished
A selected microbial increase is a biological observation, not a diagnosis of a repaired gut. The audited studies do not validate consumer microbiome scores as a way to choose an FOS product or prove universal prevention of infection, cancer or intestinal permeability disorders.
This is an evidence boundary, not proof that microbial changes are irrelevant. A useful next trial would measure a prespecified clinical outcome, test whether the microbial change explains it, and replicate the result with transparent noncommercial financing and product purchasing.
Metabolic and mood claims — No dependable gut-mediated treatment established
A 2025 trial randomized 66 adults with overweight and prediabetes. Tereos-funded scFOS changed some body-composition and microbial measures but not the primary HbA1c endpoint or other assessed glucose outcomes. Antidiabetic medication users were excluded. This does not establish diabetes prevention or an interaction with diabetes medicines. Le Bourgot 2025
Mental-health claims also require separate trials with appropriate diagnostic groups and meaningful outcomes. An anxiety-score signal within an IBS experiment is not sufficient to recommend FOS as treatment for anxiety or depression.
Crohn's disease and inflammatory bowel disease — Blend evidence does not support self treatment
Benjamin's trial found no clinical benefit in active Crohn's disease, with withdrawals in 14/54 intervention participants versus 4/49 controls. The study received Broad Medical Research Program funding and BENEO-Orafti sachets. Original report
Crucially, the prospective registry describes the historical intervention as 70% oligofructose and 30% inulin. It is not evidence for isolated sucrose-derived scFOS. The tolerability signal is relevant context for concentrated fructan mixtures during active disease; it does not prove that all fructans worsen every form of IBD.
What works and what remains uncertain
| Goal | What the audited evidence supports | What it does not establish |
|---|---|---|
| Identify the ingredient | Manufacturing route and molecular composition distinguish preparations | Equivalence based on the word FOS alone |
| Change fecal microbes | Commercial trials report measurable changes | A universal healthy microbiome target |
| Improve regularity | Some clinical signals warrant replication | A dependable independent FOS-alone treatment across populations |
| Relieve IBS | Responses and tolerance vary; global efficacy is unestablished here | A standard treatment or guaranteed low-gas option |
| Treat inflammatory disease | A major blend trial was negative | FOS replacing disease-specific care |
| Choose a retail brand | Match actual formulation and tested exposure | A verified best brand or superiority from a trademark |
Risks and side effects
| Risk or uncertainty | What is known | Practical significance |
|---|---|---|
| Gas, bloating and discomfort | Reported in human FOS research; fermentability is relevant | A worsening symptom is a reason to reassess, not evidence of healing |
| Loose stool or diarrhea | Tolerance varies with preparation, exposure and person | Persistent diarrhea deserves attention; no universal symptom-free dose was established |
| IBS sensitivity | Monash identifies FOS among fermentable ingredients that can be poorly tolerated | Check hidden FOS in synbiotic powders and foods during a clinician-guided dietary trial |
| Active bowel disease | The Crohn's mixture trial had more withdrawals | Do not extrapolate healthy-volunteer tolerance to active disease |
| Serious disease or long-term high-dose use | Small, short studies cannot exclude uncommon harms | Avoid interpreting “no significant difference” as comprehensive safety clearance |
The IBS caution comes from Monash's treatment information. Monash is a university program with a commercial app and product-certification activity; its advice is contextual, not conflict-free proof of FOS outcomes. Program revenue disclosure
One participant died during the small dialysis trial; causality was unresolved, and the authors considered a connection unlikely. It would be inaccurate either to call this a proven FOS-related death or to say the study recorded no serious event. Meksawan 2016
Rectal bleeding, constant abdominal pain, vomiting, inability to pass gas, fever or unintentional weight loss alongside constipation warrant prompt medical assessment rather than simply increasing a fiber powder. NIDDK warning signs
Interactions
| Substance or situation | Mechanism or concern | Status | Evidence basis |
|---|---|---|---|
| Prescription medicines taken by mouth | Effects on absorption have not been comprehensively tested for defined FOS preparations | Unknown clinical significance; no universal spacing interval established | Gap in the audited trials |
| Other fermentable fibers or osmotic laxatives | Combined bowel and fermentation effects are plausible | Potential additive intolerance; not a quantified drug interaction | Mechanistic inference, not a validated combination regimen |
| Antibiotics | Altering microbes could modify the response to a fermentable substrate | No dependable timing rule or interaction magnitude established | Exclusion criteria cannot prove an interaction |
| Diabetes medicines | Metabolic effects do not establish pharmacological interaction | Do not adjust medicines based on FOS research | The 2025 trial excluded these users |
| Probiotics in a synbiotic | Effects depend on the exact organism and formulation | Combination evidence does not identify FOS's separate contribution | Formulation and study-design limitation |
| Prescribed renal, bowel or nutrition regimen | Fluid allowance, co-ingredients and disease management matter | Individual clinical review needed | Specialized populations are poorly generalizable |
No comprehensive interaction program was found covering common prescriptions, minerals, other supplements or repeated high-dose combinations. That gap is not assurance of no interactions. The actual label and medicine list matter more than the general description “prebiotic.”
Who should avoid self treatment
People with a known reaction to a preparation should avoid re-exposure. Those whose IBS symptoms reliably worsen with fructans should not assume an FOS powder will be tolerated because it is marketed for digestion.
Active inflammatory bowel disease, suspected obstruction, significant motility problems, dialysis and prescribed fluid or nutrition restrictions require an individualized plan. Children, pregnant or breastfeeding people should not inherit a regimen from a short healthy-adult trial. These are precautionary boundaries, not assertions of proven harm in every listed group.
A restrictive low-FODMAP phase is also a poor setting for casually adding an untested fructan supplement. Such diets should be individualized; the ingredient's name alone does not establish the FODMAP content of every finished food at every serving size.
Dosage and how it was studied
These are research exposures, not suggested starting doses, an optimal range or a maximum safe intake. Papers do not always distinguish grams of preparation from grams of active fructan consistently.
| Research setting | Preparation and reported exposure | Duration | Interpretation boundary |
|---|---|---|---|
| Minor functional complaints | scFOS 5 g/day | 6 weeks | Paineau; commercially involved |
| IBS | scFOS 5 g/day | 4 weeks | Azpiroz; commercially supported |
| IBS | Hydrolyzed-chicory oligofructose, 10 g/day initially, then 20 g/day | 12 weeks overall | Olesen; not sucrose-derived scFOS |
| Adult irregularity | Oligofructose 5, then 10, then 15 g/day | Four weeks per phase | Buddington; industry funded |
| Dialysis-associated constipation | FOS 20 g/day as reported | 30 days per crossover period | Meksawan; specialized supervised setting |
| Healthy-adult tolerance | scFOS 15 or 20 g/day, then 30 or 40 g/day | One week at each exposure | Le Bourgot 2022; no placebo or inulin comparator |
| Prediabetes | 20 g/day preparation described as 95% scFOS | 12 weeks | Le Bourgot 2025; distinguish powder from active fiber |
Dose escalation in a trial is a method, not an instruction to repeat it. The infant and Crohn's experiments likewise do not provide self-treatment regimens. Taking more to pursue a larger microbiome change has no established clinical rationale here.
Animal and in vitro evidence
Laboratory fermentation can show which organisms use a substrate and which metabolites appear under controlled conditions. It cannot reproduce a person's gas handling, pain sensitivity, immune system, diet or medicines. Animal experiments can test mechanisms but cannot establish a human treatment dose or symptom benefit.
For example, a piglet experiment involved Tereos-provided feed/supplements and company-employed authors. Its pre- and post-weaning findings are excluded from human benefit grades. Primary animal report
No animal, cell-culture or fermentation-vessel result was promoted into an independent clinical benefit in this article.
Independent funding tracing
What qualified and what did not
This audit excludes manufacturer, seller and industry-funded outcome evidence, including donated products and other in-kind research support, from the independent benefit verdict. An arm’s-length purchase is not itself sponsorship. Mixed public-commercial finance remains commercially involved. A no-conflict declaration does not settle an acknowledgment of company support; equally, identifying a manufacturer does not prove that it donated the product.
The two apparently less commercially involved clinical reports retain important gaps. Souza names Brazilian public grants but does not clarify its supplier's payment terms. Meksawan names a university thesis grant but does not adequately identify the study product or its procurement. Neither is recast as secretly sponsored, and neither is treated as fully verified independent confirmation.
The university's published thesis-grant rules describe expense claims and publication obligations, but do not reveal this trial's purchases or every upstream source of university money. Chulalongkorn grant rules Brazilian CNPq/CAPES also administer public research support and industry-collaboration programs; institutional status cannot resolve a specific trial's missing procurement record. Official postgraduate funding plan
Who sells FOS and who benefits
Tereos is a French agricultural cooperative. Its March 2026 accounts report a 50% interest in French Beghin Meiji, identify sales of FOS from Tereos France to that venture, and record 10,296 cooperative members. These are ownership and business facts, not efficacy evidence. Tereos 2025/26 accounts, pages 14, 64 and 71
Meiji's 2025 securities report also lists Beghin Meiji as an affiliate. The exact remaining stake was not independently resolved here. Meiji Holdings is based in Japan; its dated 2025 shareholder record identifies large trust/custody accounts, which do not reveal all ultimate beneficiaries or establish control over a trial. Meiji affiliate record; corporate and shareholder record, page 92
BENEO is part of Germany's Südzucker group. Südzucker's share page, retrieved on this review date, reports SZVG holding 64.93% in its own name and on trust, Zucker Invest 10.24%, and 24.83% free float. The page does not date the underlying holdings. This structure is not a finding that shareholders directed a study. Buddington corporate disclosure; Südzucker shareholder disclosure
FOS is an ingredient family, so it has no single owner or manufacturing country. Brand owners, ingredient producers and finished-product sellers can all earn revenue. A French sponsor, Belgian ingredient operation, Japanese affiliate and American research site represent different roles; none establishes the origin of every retail batch.
Commercial success creates an incentive to obtain persuasive outcomes and usable health claims. Academic researchers face publication and career incentives. Public agencies face institutional and political pressures. These are reasons to demand transparent methods and replication, not evidence of dishonesty.
Documented money map
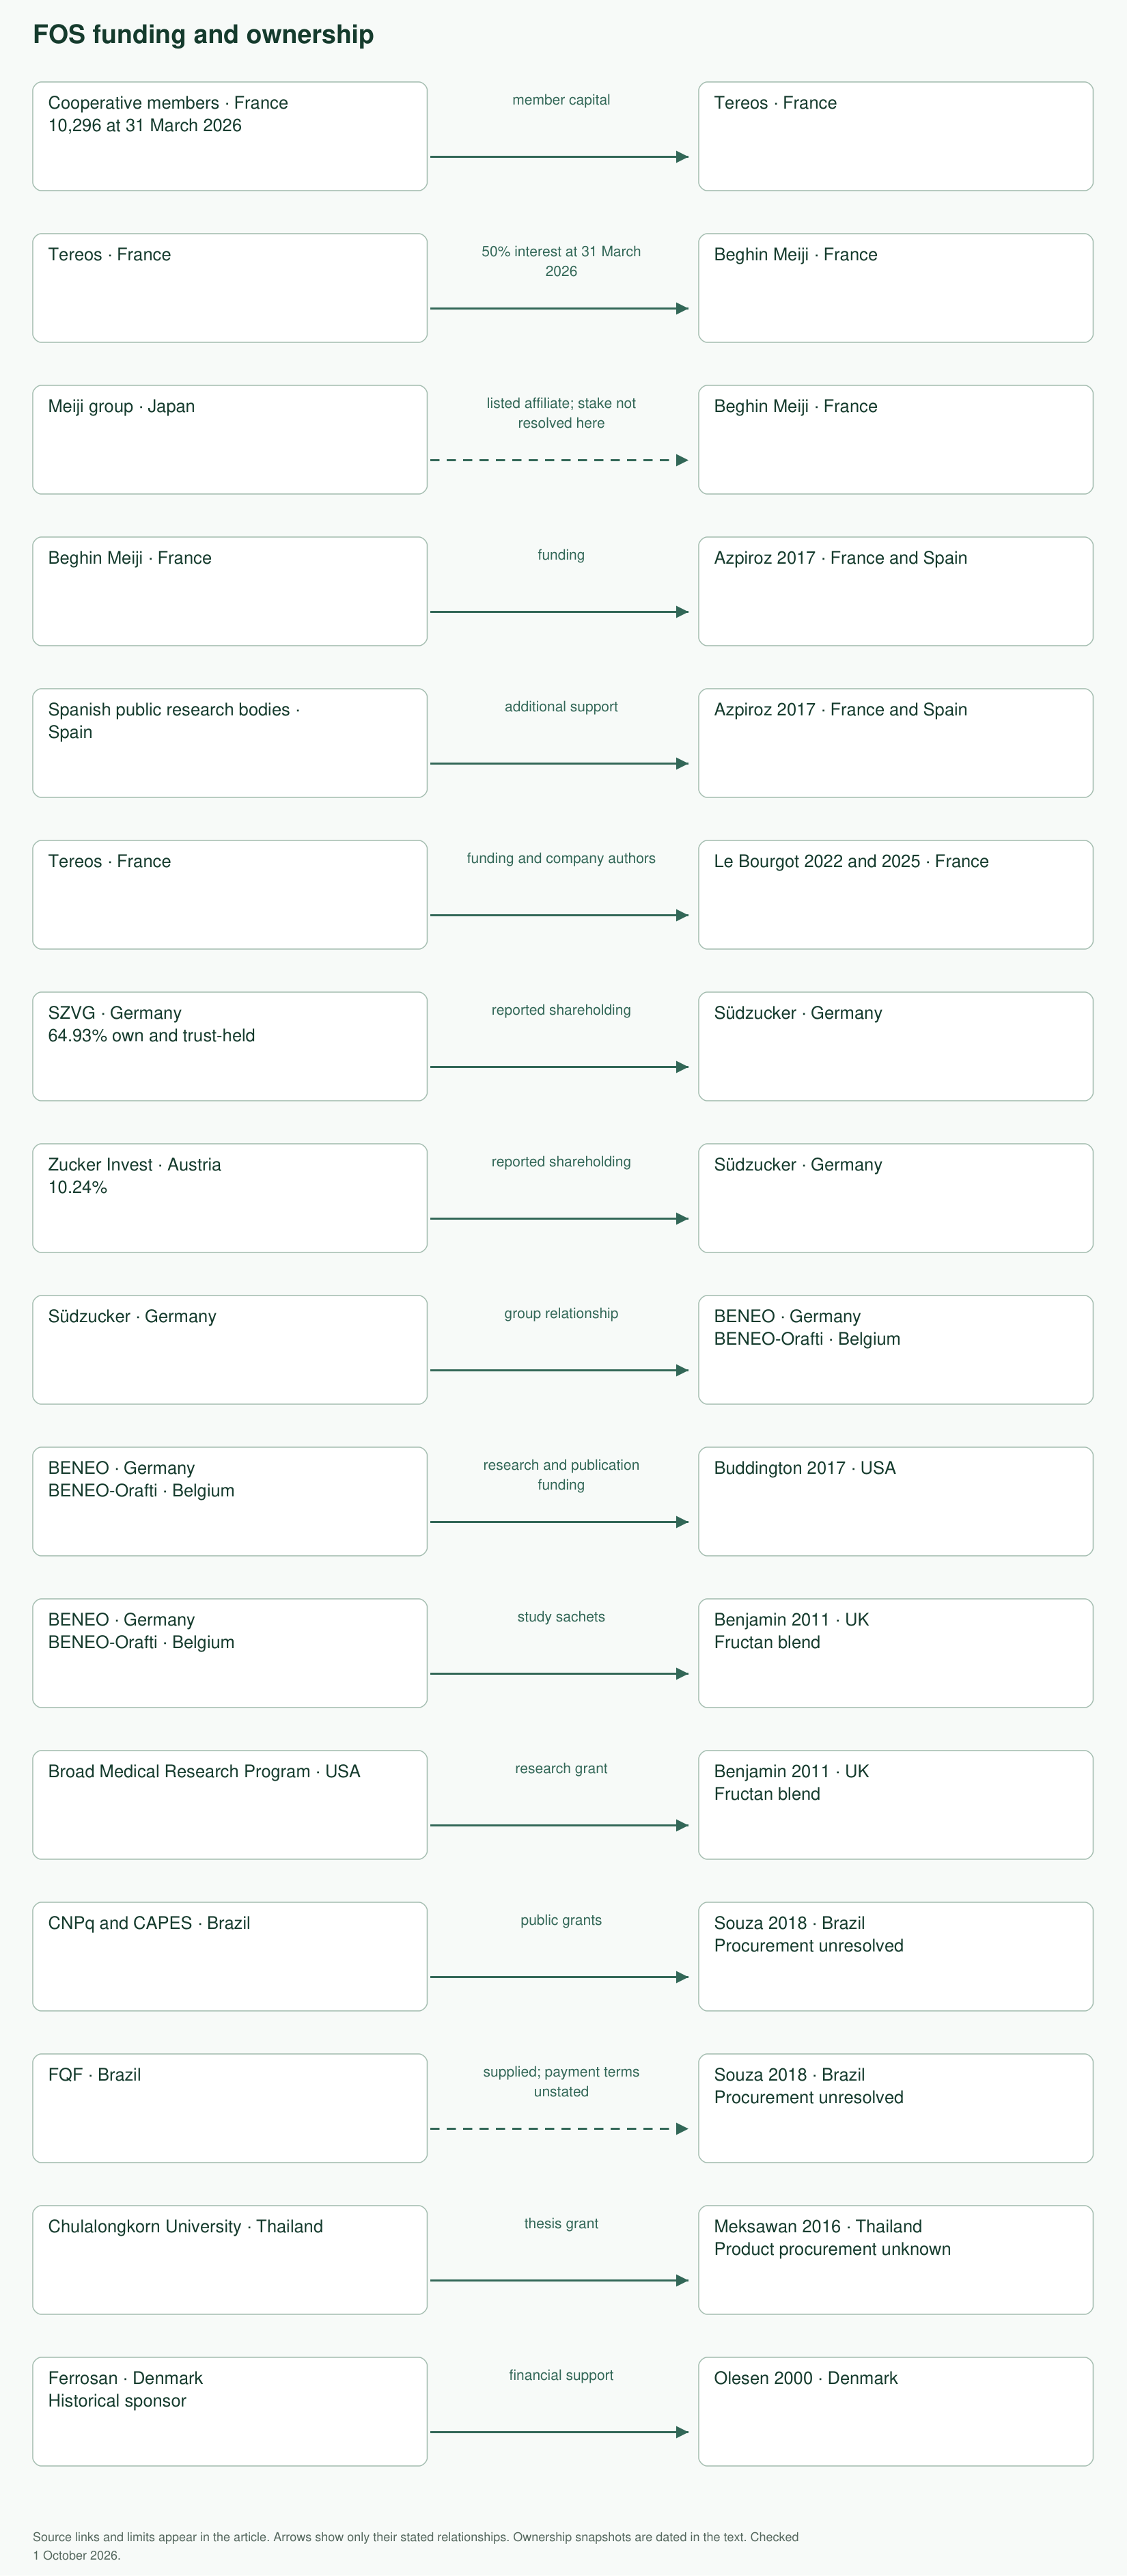
Solid arrows describe documented financial or organizational relationships. Broken arrows identify unresolved supply terms or an affiliate relationship without an assigned percentage.
Accessible relationship list:
- French cooperative members → Tereos → 50% interest in Beghin Meiji; Meiji's affiliate link is documented without an assigned stake here
- Beghin Meiji and Spanish public bodies → Azpiroz funding; Tereos → Le Bourgot 2022 and 2025 funding
- SZVG and Zucker Invest → reported Südzucker holdings → BENEO group relationship
- BENEO → Buddington financing; BENEO-Orafti and Broad Medical Research Program → material and grant support, respectively, for the Benjamin blend trial
- CNPq/CAPES → Souza grants; FQF → supplied products with payment terms unresolved
- Chulalongkorn University → Meksawan thesis grant; ingredient procurement remains unknown
- Ferrosan → historical Olesen financial support
Each trial arrow is documented in its linked original report. Current corporate relationships are not projected backward to imply ownership or influence at the time of every historical experiment. The Broad program originated with the Eli and Edythe Broad Foundation and joined the Crohn's & Colitis Foundation research portfolio in 2014, after this trial; that later move does not identify a new funder for the earlier study. Foundation history, page 10
Source credibility scorecard
Tier 1: no identified subject-specific financial stake after available checks. Tier 2: indirect ties. Tier 3: interested party. Tier 4: maker/seller funding, authorship, donated products or other direct research support; an arm’s-length purchase alone does not qualify. U: unresolved. Grades describe fitness for the use here: A high, B solid with limitations, C interested or materially uncertain, D self-interested promotion. Neither axis is a statistical-quality score.
| Source | Funder or revenue model | Country or jurisdiction | Tier and grade | Accuracy incentive and remaining limitation |
|---|---|---|---|---|
| AHRQ 2025 FOS analysis | US public commission | USA | 1 at review level; A for methods | Transparent synthesis; underlying trials retain their financial ties |
| Balk 2026 review methods report | AHRQ contract; HHS/USDA sponsors; no conflicts reported | USA/Australia | 1 provisional at review level; B | Public protocol and disclosures; not an industry-free trial pool |
| Scholtens 2006 | Numico Research employees; complete budget not separately traced | Netherlands | 4; C | Primary controlled study; commercial research origin, high exposure and small sample |
| Buddington 2017 | BENEO research/publication funding | USA; funder Germany | 4; C | Peer-reviewed trial; commercial data-use interest |
| Meksawan 2016 | University thesis grant | Thailand | U; C provisional | Detailed reporting; tiny sample and unknown procurement |
| Souza 2018 | CNPq/CAPES; FQF supplier | Brazil | U; B provisional | Randomized report; supply terms unresolved |
| Olesen 2000 | Ferrosan support | Denmark; ingredient Belgium | 4; C | Placebo control; historical commercial sponsor |
| Azpiroz 2017 | Beghin-Meiji and Spanish public support; Tereos authors | France and Spain | 4; C | Blinded trial; commercial and exploratory-outcome concerns |
| Paineau 2008 | Beghin Meiji and contract-research affiliations; complete budget unstated | France | 4; C | Primary methods; compliance and financing gaps |
| Bouhnik 2006 | Eridania-Beghin Say grant | France; funding unit Belgium | 4; C | Dose comparison; surrogate outcome and sponsor stake |
| Le Bourgot 2022 | Tereos; paid contract researchers | France | 4; C | Disclosed sponsorship; no placebo or direct comparator |
| Le Bourgot 2025 | Tereos funded design/oversight/publication involvement | France | 4; C | Registered randomized trial; primary result negative, secondary interpretation requires caution |
| Benjamin 2011 | Broad grant plus BENEO-Orafti sachets | UK; USA/Belgium support | 4; C | Prespecified clinical endpoint; blend and commercial material support |
| ISRCTN50422530 | Sponsor-entered registry; Barts NHS/Broad listed | UK; Broad USA | 4; C for sponsor-entered protocol facts | Timestamped record; no independent results validation |
| Piglet FOS study | Tereos products and employee salaries | Research in Belgium; funder France | 4; C | Primary animal methods; no human efficacy |
| Monash IBS information | University program; app and certification activities | Australia | 2; B for context | Clinical/reputational incentives; program has commercial interests |
| Monash app disclosure | App sales support research | Australia | 3; B for its revenue statement | First-party disclosure; promotes paid program |
| NIDDK warning signs | Federal public-health agency | USA | 1; A for general warning signs | Public accountability; not FOS-specific research |
| Chulalongkorn grant rules | University-administered funds | Thailand | 1 provisional; B for rules | Expense/publication accountability; trial ledger unavailable |
| CAPES funding plan | Government research budgets and partnership programs | Brazil | 1 for policy record; A | Official record; cannot identify this study's procurement |
| Tereos accounts | Ingredient revenue, cooperative capital and borrowing | France | 4; C for corporate facts | Reporting obligations; no independent efficacy value |
| Meiji securities report | Food/pharma revenue and shareholder capital | Japan | 4; C for affiliate facts | Financial disclosure; precise affiliate stake unresolved |
| Meiji integrated report | Same commercial group | Japan | 4; C for dated corporate facts | Published register; custody accounts obscure ultimate owners |
| Südzucker share page | Sugar/ingredient revenue and shareholder capital | Germany; investor Austria | 4; C for holdings | Investor accountability; underlying date not provided |
| Crohn's & Colitis Foundation history | Charity donations and philanthropy | USA | 2 provisional; B for program history | Donor/public scrutiny; not a complete historical donor audit |
| FDA 2018 chemistry review | Government agency; industry submissions also evaluated | USA | 2 institutionally; A for stated scope | Regulatory accountability; underlying trials retain their original funding status |
| FDA dietary-fiber FAQ | Government agency | USA | 2 institutionally; A for labeling status | Authoritative policy; not product efficacy approval |
| FDA GRN 990 response | Government review of Tata Chemicals' submission | USA; applicant India | 2 institutionally; A for letter contents | Scoped legal record; applicant evidence is not independent |
| EFSA scFOS 2016 opinion | EU public authority; Beghin-Meiji/Tereos application | Italy / European Union | 1 for assessment; A | Published reasons; applicant's trials remain commercially sourced |
| EFSA Frutalose 2021 opinion | EU public authority; Sensus/Royal Cosun application | Italy / EU; applicant Netherlands | 1 for assessment; A | Transparent evidentiary threshold; no independent replication created |
| FDA funding explanation | Appropriations and product-specific user-fee programs | USA | 2 institutionally; A for financing model | Statutory disclosure; agency-level facts do not establish FOS influence |
| EFSA independence policy | EU public authority | Italy / European Union | 1 institutionally; B for governance design | Published interest-management rules; implementation still matters |
| EU Regulation 2015/2314 | EU institutions/public budgets | Belgium / European Union | 1; A for legal scope | Defines a native-chicory claim, not FOS treatment efficacy |
| EU Regulation 2023/1141 | EU institutions/public budgets | Belgium / European Union | 1; A for legal status | Binding published decision; not a new clinical trial |
FDA receives congressional funding and industry user fees at agency level; this does not identify FOS-specific payment for these decisions. EFSA publishes an independence policy and expert-interest procedures. These safeguards merit scrutiny and do not transform applicant-sponsored trials into independent evidence. FDA funding explanation; EFSA independence policy
The clinical source set is concentrated in European commercial ingredient networks despite research sites on several continents. The audit could not resolve every historical supplier, upstream donor or ultimate beneficial owner. Geography itself is not a quality score.
Regulatory status
In the United States, FDA's current dietary-fiber FAQ includes inulin and inulin-type fructans among additional carbohydrates covered by its labeling enforcement-discretion position pending rulemaking. This should not be described as approval of an FOS supplement to treat IBS or constipation. FDA FAQ
The FDA response to Tata Chemicals' GRAS notice 990 is limited to the notified ingredient and intended uses. It explicitly does not assess labeling claims and does not amount to a formal affirmation of GRAS status under the cited regulation. A no-questions letter is not an efficacy endorsement or permission to improvise an infant-formula regimen. Agency response
In Europe, EFSA did not substantiate the proposed normal-defecation claim for sucrose-derived scFOS in its 2016 assessment. Its 2021 Frutalose assessment also found evidence insufficient, despite a positive trial, because results were not replicated under the proposed conditions. These are scoped, dated assessments, not declarations that the ingredients can never help. scFOS opinion; Frutalose opinion
The European Commission refused the proposed Frutalose regularity claim in 2023. Regulation 2023/1141 The separate authorization for native chicory inulin must not be transferred to an arbitrary FOS product. Regulation 2015/2314
FAQs
Is FOS the same as fructose?
No. The fructose units are linked in chains. Finished preparations may also contain residual simple sugars, so the actual composition still matters.
Is FOS the same as inulin?
They are related fructans, but chain distributions and manufacturing routes differ. Research needs to identify the preparation rather than treating the names as synonyms.
Is FOS a probiotic?
No. It is not a live microorganism. It is commonly used as a prebiotic substrate or combined with probiotics in a synbiotic product.
Does more Bifidobacterium mean the supplement works?
It means the measured microbial outcome changed. A treatment claim still needs meaningful clinical improvement and an appropriate comparison.
Can FOS help constipation but worsen bloating?
Those outcomes can move in different directions. The aim is comfortable, useful bowel improvement, not simply maximizing frequency or fermentation.
Does industry funding mean the result is false?
No. It changes the independence classification and raises the importance of transparency and replication. This review excludes such studies from its independent benefit verdict while reporting them accurately.
Is there a dose that is safe for everyone?
No universal safe or effective dose was established here. Healthy-adult averages cannot determine individual tolerance or safety in children, active bowel disease or complex medical treatment.
Can a synbiotic trial prove that FOS works alone?
Only a design that isolates FOS's contribution can answer that. A favorable result for a whole formula, probiotic combination or inulin blend cannot automatically be assigned to FOS.
Sources and funding
The original human papers, trial registry, regulator records and corporate disclosures linked above form the source set. Company sources were used for identity and financial relationships; their marketing claims were not adopted as independent evidence. The scorecard identifies the purpose and limitations of every cited source.
This is a focused critical review rather than an exhaustive systematic review. No pooled estimate was calculated because preparations, populations and outcomes differ, and commercial support affects eligibility for the independent verdict. A regulator's review does not remove sponsorship from its underlying studies. Product-purchase records, some historical financing and ultimate-owner detail remain unresolved.
The article addresses FOS separately from longer-chain inulin, other prebiotics and probiotics. Mixtures and animal findings remain clearly bounded. No claim is made that every drug interaction or rare adverse effect has been characterized.
Last reviewed: 1 October 2026
Have a question — or want us to cover something?
Ask about anything on this page, or request the next deep dive: an ingredient, a supplement, or a health concern. We use published research, evidence syntheses, and regulatory guidance, with clear source links.
One daily research roundup
Get the topics, key findings and links from our new articles in one email. At most one digest a day, only when there is something new.