
Key takeaways
- Supplemental GOS usually means manufactured beta-galacto-oligosaccharides made from lactose; the alpha-galactosides in beans are chemically different
- Several selected adult studies report microbial or symptom changes alongside documented commercial funding, company authors or manufacturer assistance; some financial chains remain unresolved
- Clinical findings are mixed and preparation-specific; this reviewed source set does not establish a fully verified independent-only estimate of adult IBS or constipation benefit
- More bifidobacteria does not automatically mean less pain, better bowel function or a healthier person
- Product composition, residual lactose and milk-allergen labeling matter; serious allergic reactions to certain GOS preparations have also been reported
Selected GOS preparations have promising symptom findings, but placebo comparisons, populations and doses differ. A constipation trial missed its primary comparison, and exercise results were mixed. More bifidobacteria does not prove symptom relief or gut repair. Known commercial support and unresolved financial chains prevent a fully verified independent-only estimate from these sources. Product composition, residual lactose and milk-allergy warnings matter; serious allergic reactions have been reported. Constipation trial, Exercise trial, Allergy series
Contents
Evidence summary · What it is · Selected formulations · How it works · Hype versus evidence · Benefits by claim · What works · Risks · Interactions · Who should avoid · Studied doses · Laboratory evidence · Funding · Regulation · FAQs · Sources
Evidence summary
The table separates clinical observations from financial provenance. A commercial tie does not make a finding false, and unresolved support does not mean a study is independent. The final column is an editorial eligibility judgment for an independent-only estimate, not a formal GRADE rating or proof of no benefit. Positive subgroups, within-group changes and placebo comparisons are different findings.
| Claim tested or promoted | Evidence | Primary source | Funding or conflict | Independent-only eligibility |
|---|---|---|---|---|
| Relieves IBS | Small early study with 44 completers; original full paper unavailable here | Silk 2009 | Clasado sponsor/funder in trial register | Known commercial support; retained as clinical context |
| Reduces bloating, pain and flatulence | 91 randomized, 83 completed; short symptom-selected crossover, no stool-frequency or quality-of-life improvement | Vulevic 2018 | Clasado funding and employment links | Known commercial support; retained as clinical context |
| Improves constipation | 132 participants; primary comparison inconclusive, selected post-hoc findings positive | Schoemaker 2022 | FrieslandCampina funding and employees | Known commercial support; retained as clinical context |
| Improves functional constipation | 70 randomized, 63 analyzed; selected bowel-frequency and stool-form advantages | Lee 2024 | Neo Cremar support and company author | Known commercial support; retained as clinical context |
| Improves constipation with gummies | 35 university staff; complete methods and outcome tables unavailable | Dey 2023 | Gujarat fellowship; Tata supply acknowledged, payment terms unresolved | Clinical and procurement verification incomplete |
| Prevents travel diarrhea | 523 enrolled; positive protocol-adherent result, evaluable comparison inconclusive | Hasle 2017 | Clinic support and free Clasado materials | Known free materials; retained as clinical context |
| Repairs the gut barrier | Selected marker-change signal; overall marker analysis and another sports pilot inconclusive | Parker 2026, Gough 2025 | Supplied Clasado product or partial company funding | Known support; general healing not established |
What it is
Galacto-oligosaccharides are short carbohydrates containing galactose. Commercial beta-GOS mixtures are generally produced by enzymatically converting lactose into oligosaccharides with different lengths and linkages. “GOS” therefore describes a family of preparations rather than one chemically identical substance. The FDA's scientific review describes this manufacturing and structural variability.
Three distinctions prevent misleading comparisons:
- Manufactured beta-GOS versus legume alpha-galactosides. Raffinose-family carbohydrates in beans and pulses contain alpha-galactosidic linkages. They are often called GOS in FODMAP discussions. Those foods and their response to alpha-galactosidase are not evidence that the same enzyme will digest every beta-GOS supplement. Monash's food and enzyme explanation, production chemistry review
- GOS versus lactose. A preparation may contain both. Lactose intolerance involves difficulty digesting lactose and varies with the amount consumed; milk allergy is a separate immune condition. NIDDK
- GOS versus human milk oligosaccharides. Commercial GOS is not a substitute for the full composition or biological effects of human milk. A shared capacity to influence microbes does not establish equivalence. Infant-formula trials also test a different population and food matrix from adult supplements. Ashley 2012
Selected formulations
| Form | What changes | Interpretation |
|---|---|---|
| Syrup or powder with residual sugars | Proportion of GOS, lactose, glucose, galactose and water | Grams of ingredient can differ substantially from grams of active GOS |
| Higher-purity beta-GOS | Residual-sugar content and oligosaccharide profile | Greater purity is not proof of greater symptom benefit |
| Branded mixtures such as Bimuno or Biotis | Manufacturing process and composition | Match the actual studied preparation; do not infer class-wide equivalence |
| Gummies, capsules and sachets | Dose per serving, sweeteners, fillers and other ingredients | An attractive delivery format is not a clinical endpoint |
| GOS plus FOS, probiotics or other fibers | Several active components | Results cannot automatically be assigned to GOS alone |
| Infant formula | Complete nutritional matrix and age-specific use | Evidence is product- and population-specific |
| Legume alpha-galactosides | Different linkages and food matrix | Keep separate from manufactured beta-GOS evidence |
A useful label identifies the actual GOS amount, the full ingredient list and relevant allergens. It should not rely only on “prebiotic blend” or a powder weight. The Floratrol seller's current label, for example, lists lactose and a milk warning; this demonstrates a labeling issue, not endorsement of that product. Manufacturer label
The cited clinical studies do not establish a validated hierarchy of “clinical grade,” brands or purity levels. Batch quality and efficacy are separate questions; composition, contaminants and allergen suitability of a reader’s specific retail lot remain unverified. Production chemistry, Example seller label
How it works
The proposed pathway is that poorly digested oligosaccharides reach gut microbes, which can use them as substrates. Fermentation changes microbial activity and produces metabolites and gas. Whether that leads to a worthwhile symptom change depends on the person, preparation and exposure.
In an 18-adult, sequential dose experiment, bifidobacterial changes varied between individuals, were significant at 5 and 10 g/day rather than 2.5 g/day, and reversed within about a week of withdrawal. The nonrandomized exposure sequence and microbial endpoints do not establish symptom benefit. USDA support coexisted with a GTC Nutrition partnership grant, supplied GOS and an adviser relationship. Davis 2011
The missing step in many marketing claims is clinical validation. Counting a bacterial group is not equivalent to measuring comfortable bowel movements, sustained relief, ability to eat normally or quality of life. Nor is every increase in a genus beneficial regardless of strain, function and context. EFSA explicitly cautioned that a bifidobacterial effect alone did not predict relief of gastrointestinal discomfort. EFSA 2011 opinion
Hype versus evidence
“Clinically studied” can obscure the comparison. An intervention may change a measurement from baseline while failing to outperform placebo. Subgroup benefits may be exploratory even when the abstract sounds conclusive.
“No external funding” can omit other contributions. Manufacturer preparation and blinding of study products are relevant research roles. The 2026 exercise study documents manufacturer blinding and supply, although payment terms are unstated; a free donation should not be assumed.
“Works at a capsule-sized dose” may describe a laboratory model. The 2025 low-dose paper tested fecal fermentation systems, not people swallowing capsules. Human donors do not turn an ex vivo experiment into a clinical trial. Harthoorn 2025
“Supports the immune system” is too vague to judge. Changes in cytokines or salivary antibodies need not mean fewer clinically confirmed infections. The intended benefit, population and observation period should be named.
“Gut repair” overstates a broad claim. An exercise-injury marker, a cell-culture result or a microbiome shift does not establish treatment of inflammatory bowel disease, food allergy or a generalized “leaky gut” diagnosis.
Benefits by claim
IBS and abdominal discomfort — Mixed short-term findings
Silk’s early study reported selected symptom improvements in 44 completers. The prospective registry identifies Clasado as sponsor and funder. EFSA’s assessment describes 60 randomized participants, complete-case analysis, a placebo-first design and multiple-outcome limitations. The full original paper remains unavailable here; a favorable abstract cannot resolve those methodological concerns or complete financial declarations. Silk 2009, Prospective registry, EFSA assessment
Vulevic’s 2018 report randomized 91 symptom-selected adults and analyzed 83 completers. During two-week treatment periods, bloating, flatulence and abdominal-pain scores improved; stool frequency, stool consistency, quality of life and mood did not differ significantly. The study was not a general IBS population. Clasado funded and supplied interventions; one author was an employee during the trial and two became employees after analysis. EFSA had already assessed the same 91-person study in unpublished form in 2011 and criticized its pooled crossover analysis. These are different documents about one trial, not independent replication. Vulevic 2018, Earlier EFSA assessment
The Wilson reports describe one 69-person, three-arm, four-week trial, not separate replications. Adequate relief was about 67% with low-FODMAP diet plus GOS, 50% with that diet plus placebo and 30% with sham diet plus placebo. The combination-versus-sham contrast cannot isolate added GOS from the diet; bifidobacteria were not restored. The conference abstract, prospective registry and later original financial declarations document Clasado support alongside university and NHS institutional roles. Wilson 2020, 2017 conference abstract, 2023 same-cohort report, Prospective registry
Taken together, these findings justify better trials, not a claim that all GOS products treat IBS. A low-FODMAP plan should not be redesigned from a manufacturer's microbiome claim alone.
Constipation — Primary and subgroup results differ
Schoemaker’s three-week, 132-person trial did not reach significance in the primary full-population comparison (p = 0.095). The prespecified subgroup with fewer than three weekly bowel movements was also inconclusive (p = 0.071). A broader, post-hoc subgroup with no more than three movements was positive (p = 0.027); stool consistency and symptom scores did not show corresponding significant differences. FrieslandCampina funded the trial and employed five authors. The company-hosted report is the same paper as the journal article, not replication. Original trial, Company-hosted copy
Lee’s four-week Korean trial randomized 70 adults with functional constipation and analyzed 63. The reported between-group bowel-frequency advantage was 0.15 movements/day, with improved stool form and one quality-of-life satisfaction domain; other measured quality-of-life domains and transit did not differ significantly. Microbial increases were within-group findings, without significant between-group differences. Neo Cremar supported the work and a company author contributed analysis, despite a no-conflicts declaration. The paper’s continuous-outcome table labels and stated statistical method are inconsistent, adding uncertainty. Lee 2024
Dey’s 35-person university-staff trial reported favorable constipation-related findings, but complete methods and outcome tables remain unavailable here. The original disclosures name a Government of Gujarat fellowship, university support, Tata Chemicals GOS supply and a Syri Research laboratory coauthor. A separate formulation paper reports purchased GOS; that does not establish the clinical batch’s payment terms. A donation or independent purchase is not inferred. Clinical abstract and disclosures, Separate formulation report
These studies differ in formulation, baseline symptoms and analysis. They should not be pooled informally into a universal dose or expected benefit. Frequency alone also misses straining, incomplete evacuation and rescue-treatment use.
Travel diarrhea — Analysis-dependent findings
Hasle’s travelers’ study enrolled 523 people. The protocol-adherent analysis favored GOS (OR 0.56, p = 0.03), whereas the evaluable comparison was inconclusive (OR 0.65, p = 0.08). The strongest reported reduction concerned one-day diarrhea; duration and severity did not improve. The prospective registry names the travel clinic’s support and free Clasado materials. The full original methods and financial declarations remain unavailable here, and these findings do not establish general travel-infection prevention. Hasle 2017, Trial registry
That finding does not establish treatment of an active infection, antibiotic-associated diarrhea or unexplained persistent loose stools. A banana-fiber/GOS product is also a different intervention from GOS alone. No independently established indication for those uses emerged from this audit.
Exercise symptoms and intestinal barrier claims — Limited, mixed findings
Parker’s 2026 trial involved 26 male recreational team-sport athletes taking GOS or placebo for 42 days before a simulated football protocol in heat. The absolute I-FABP group-by-day-by-time analysis was inconclusive (p = 0.064), while a selected peak-change comparison favored GOS (p = 0.048). Lipopolysaccharide-binding protein did not differ. Total gastrointestinal severity and self-reported respiratory episode duration/severity improved, but symptom incidence and several other comparisons did not. Clasado supplied and blinded both products despite a “None” funding declaration; payment terms were unstated. The findings do not demonstrate bowel healing or clinically confirmed infection prevention. Parker 2026
Gough’s 18-person, 12-week recreational-athlete pilot found no significant group-by-time benefit for gastrointestinal outcomes, anxiety, wellness, sleep or recovery. Baseline symptoms were low and no formal power calculation was reported. Variation between participants is not proof of individual treatment responders. Clasado partly funded the study. This small null pilot neither establishes universal ineffectiveness nor confirms benefit in another athletic population. Gough 2025
Ulcerative colitis and immune markers — Exploratory findings
Wilson’s ulcerative-colitis pilot started 17 participants, with 13 completing six weeks and 12 paired microbiome samples. Clinical disease activity, calprotectin and remission did not improve significantly. Some stool and urgency measures changed in an open-label design without a concurrent placebo group; these cannot establish mucosal healing or a replacement for prescribed care. Clasado and King’s College London financed the study, with additional author commercial and invention interests disclosed. Wilson 2021
Vulevic’s 2015 crossover trial included 40 healthy adults aged 65–80 receiving a 5.5 g/day mixture, about 2.64 g active GOS, during 10-week periods. Natural-killer activity and selected cytokines changed, but cytokine results used a smaller sample; bowel function, mood and salivary IgA did not improve significantly, and CRP was higher with GOS. No reduction in clinical infections was established. Clasado funded the study, supplied interventions and participated in design/writing; two authors were employees. Vulevic 2015, Original published paper
Infant stools and formula tolerance — Different question
Ashley’s trial randomized 426 formula-fed infants; 419 consumed study formula and 287 completed. The GOS and GOS/polydextrose formulas also differed from control in other nutrients. Overall growth across days 14–120 did not differ, while selected early stool findings did. Overall adverse-event frequency was similar, but excessive spitting was more common in the GOS arm. Mead Johnson funded the study and company employees contributed. This is evidence about particular infant formulas, not isolated adult GOS efficacy or universal formula tolerance. Ashley 2012
Evidence for GOS/FOS mixtures likewise cannot identify the separate contribution of GOS. Do not add adult powders to infant feeds or alter a prescribed formula using an adult study-dose table.
Lactose tolerance — Unconfirmed as a general supplement benefit
The commercial development history is a useful warning against relying on early positive reports alone. Ritter Pharmaceuticals disclosed that its high-purity GOS candidate RP-G28 missed its prespecified primary and secondary endpoints in a 2019 Phase 3 trial. This is the developer's legally accountable report, not independent trial evidence and not proof that every GOS formulation has identical effects. Ritter 2019 annual filing
GOS is not lactase. This review does not establish that a retail GOS product restores lactose tolerance.
What works and what does not
| Proposition | Verdict | Boundary |
|---|---|---|
| GOS is one standardized substance | Incorrect | Linkages, purity and residual sugars vary |
| Changing stool microbes proves clinical improvement | Unsupported inference | Patient-important outcomes need separate testing |
| Some branded preparations have positive human findings | Yes, as commercially supported observations | Not independent confirmation |
| All constipation or IBS patients should take GOS | Not established | No generalizable independent treatment rule identified |
| Formula blends prove adult standalone benefits | Incorrect extrapolation | Population and intervention differ |
| GOS reliably prevents travel illness | Not independently established | Protocol-adherent subgroup and short illness findings are insufficient |
| A negative or positive sponsored study is automatically false | Incorrect | Funding affects eligibility and scrutiny, not truth by itself |
| Every person will develop gas or benefit from treatment | Unsupported | Individual response cannot be predicted reliably here |
Risks and safety
| Risk or uncertainty | What the record supports | Practical boundary |
|---|---|---|
| Gas, bloating, cramping or altered stools | Fermentation can be uncomfortable; small selected trials cannot guarantee tolerance | A “prebiotic” label does not make worsening symptoms evidence of healing |
| Residual lactose | Present in some preparations; tolerance is dose- and person-dependent | Check the actual label, rather than assuming all GOS is lactose-free |
| Milk allergy | Some milk-derived products explicitly carry a milk warning | Low lactose does not establish suitability for milk allergy |
| GOS-associated immediate allergy | A Southeast Asian case series described reactions in six mothers, five meeting anaphylaxis criteria | Reported serious signal; frequency in general users is unknown |
| Long-term use and special populations | Short studies cannot define uncommon harms or universal safety ceilings | Pregnancy, children and significant bowel disease require context-specific review |
| Unexplained bowel symptoms | A supplement can delay evaluation of a different problem | Persistent symptoms or warning signs warrant assessment |
Soh’s series described immediate reactions in six atopic mothers, five meeting anaphylaxis criteria. Singapore public research financing coexisted with FrieslandCampina-supplied diagnostic GOS and a no-competing-interests declaration. The signal remains clinically relevant; commercial material support does not invalidate it. The selected cases cannot estimate population incidence, and the reactions are distinct from ordinary lactose intolerance. Soh 2017, Lactose-intolerance distinction
Throat or tongue swelling, breathing difficulty, collapse or a rapidly developing severe allergic reaction requires emergency help. NHS anaphylaxis guidance Constipation with bleeding, constant abdominal pain, vomiting or inability to pass gas also needs prompt assessment rather than another fiber experiment. NIDDK warning signs
Interactions
| Substance or situation | Evidence status | Interpretation |
|---|---|---|
| Oral medicines | Comprehensive GOS-specific absorption and pharmacokinetic studies were not identified | No universal spacing rule or claim of “no interactions” is established here |
| Other fermentable fibers or sugar alcohols | Combined digestive exposure differs from GOS alone | Additive symptoms are plausible; exact thresholds remain individual and product-specific |
| Antibiotics or probiotic blends | May change the microbial context; trials often restrict their use | An efficacy interaction cannot be assumed, and prescribed treatment should not be changed |
| Alpha-galactosidase products | Food alpha-galactoside findings address different linkages | Do not assume they neutralize manufactured beta-GOS |
| Milk allergy or lactose intolerance | Product ingredients are material | These are distinct issues; a pharmacist or clinician needs the specific label |
| Low-FODMAP treatment | A small combination trial does not define a general protocol | Assess diet, preparation and symptoms together |
Explicit gaps: The audit did not establish a complete interaction profile for prescription medicines, mineral supplements or repeated high-dose combinations. The absence of a reported interaction in a small nutritional trial is not evidence that every combination is safe. Wilson combination trial, Monash enzyme context, NIDDK lactose distinction
Who should avoid self treatment
People with a previous reaction to the preparation should avoid re-exposure pending appropriate assessment. A known milk allergy requires careful product-specific advice; “milk-derived,” “low lactose” and “hypoallergenic” should never be treated as interchangeable statements.
People with unexplained bleeding, persistent severe symptoms, suspected obstruction, significant inflammatory bowel disease or a prescribed feeding plan should not substitute GOS for evaluation or treatment. Children, pregnant or breastfeeding people and those with complex medical conditions should not extrapolate their own regimen from adult research. These boundaries reflect uncertainty and the consequences of a missed diagnosis, not a claim that GOS is proven harmful in every listed group.
Dosage and how it was studied
These are descriptions of study exposures, not recommendations, starting doses or a proven optimal range. Some papers report the weight of a mixture, others the active GOS content. Those amounts must not be silently interchanged.
| Study context | Reported exposure | Duration | Important qualification |
|---|---|---|---|
| Adult discomfort | 2.75 g/day B-GOS mixture, approximately 1.37 g active GOS | Two-week crossover periods | Vulevic 2018; sponsored |
| IBS plus low-FODMAP diet | 1.4 g/day in the 2020 abstract; 1.8 g/day B-GOS in the 2023 same-cohort report | Four weeks | Wilson 2020; Wilson 2023; unresolved dose-definition difference; combined intervention |
| Self-reported constipation | Nominal 5.5 or 11 g/day; composition table reports 5.2 or 10.4 g DP≥2 GOS in 7.5 or 15.1 g powder | Three weeks | Schoemaker 2022; DP≥3 fiber 3.6 or 7.2 g, lactose 1.7 or 3.5 g; primary comparison inconclusive |
| Functional constipation | Approximately 2 g/day GOS in six capsules | Four weeks | Calculated from 333.33 mg/capsule; Lee 2024 |
| Constipated university staff | 10 g/day GOS in gummies | Thirty days | Dey 2023; abstract-reported exposure; full protocol and clinical-batch procurement unresolved |
| Male athletes exercising in heat | 3.65 g/day mixture, 2.75 g active GOS | Forty-two days | Parker 2026; manufacturer-supplied and blinded; payment terms unstated |
A dose that changes bacterial counts is not necessarily a dose that improves symptoms. Neither a trial's largest exposure nor the absence of severe events during a few weeks defines a general safety limit.
Animal and in vitro evidence
Animal experiments, cell cultures and fermentation vessels were excluded from human benefit grades. They can generate hypotheses and characterize an ingredient, but cannot establish clinical efficacy, a safe human dose or long-term prevention.
The “ultra-low-dose” 2025 experiment used a fecal culture platform with samples from eight adults. Clasado funded it and an employee participated in its design and interpretation. It is laboratory evidence even though the microbes came from people. Its capsule-equivalent terminology should not be read as a successful capsule trial. Harthoorn 2025
Funding and financial relationships
Research funding at a glance
30 disclosure entries. The counts below summarize independence tiers explicitly assigned in this article. They count disclosures, not studies, funding amounts or evidence quality.
Consult this article’s source and funding notes for named funders, countries, relationships and exceptions where available. Institutional backing, researcher interests and trial sponsorship are separate questions. Public funding alone does not establish independence; commercial ties alone do not prove a claim false. This overview is not a new financial audit.
What qualified and what did not
An independent-only estimate would exclude known manufacturer financing, commercial author participation or documented research assistance; an arm’s-length purchase alone is not sponsorship. Public support does not remove a commercial contribution. Unknown funding or procurement remains unknown, and a no-conflicts declaration does not resolve every supplier or author relationship. The clinical findings are retained and assessed separately; no fully verified independent-only pooled estimate is calculated.
Three examples show why this matters:
- Dey's public fellowship coexists with a supply acknowledgment whose payment terms are unresolved
- Parker declares no funding but documents company-supplied interventions and manufacturer blinding; payment terms are unstated
- Soh's public grant coexists with industry-supplied allergy-testing material
Those relationships do not establish fabrication or dictate the direction of the result. In particular, the reported allergy signal and the null sports pilot remain worth describing. The rule is applied to positive and negative outcomes consistently.
Who benefits and where the money comes from
Clasado and Bimuno. Clasado's current contact page identifies its headquarters in Reading, United Kingdom. The UK register for Clasado Limited lists five active controllers through rights concerning trustees: Daniel Damjanovic, Hasan Inetas, Michael Oberhuber, Stefan Wenaweser and Johannes Michael Burger. Reported residences are Switzerland or Liechtenstein. These are control disclosures, not verified personal ownership percentages, citizenship-based judgments or evidence of involvement in a specific trial. Ultimate trust beneficiaries and the complete group ownership chain were not established. Company contact, Companies House control record
FrieslandCampina and Biotis. The Netherlands-based dairy business is owned by its dairy cooperative. The 2025 annual report identifies Zuivelcoöperatie FrieslandCampina U.A. as sole shareholder, and the March 2026 adoption announcement documents member-farmer profit payments. Cooperative ownership still creates a commercial interest in ingredient sales. 2025 annual report, 2026 member-council announcement
Tata. Tata Chemicals is an Indian commercial ingredient supplier. Its FY2025–26 filing reports Tata Sons at 31.90% and Tata Investment Corporation at 5.97% as of 31 March 2026. Tata states that philanthropic trusts own 66% of Tata Sons. Charitable upstream ownership does not resolve whether a specific research supply was independent or commercially supported. These are reported stakes at a stated date, not a live shareholder audit. Tata Chemicals filing, Tata ownership disclosure
Other participants. Neo Cremar's Korean trial involvement, GTC Nutrition's historical US support and Mead Johnson's US formula-study participation are documented in the original papers. Their full current ultimate-ownership chains were not resolved for this audit; no present parent-company relationship is inferred from a historical affiliation.
Headquarters, research country and manufacturing origin are different facts; the cited documents do not trace every retail lot to a plant. The chemistry review acknowledges public PREMIUM financing, whose official record includes industrial partners; this is an indirect connection rather than proof industry controlled the review. Monash discloses app and certification income. Its educational material is used for ingredient and dietary context, not as financially disinterested clinical proof of GOS efficacy. Chemistry review, PREMIUM grant, App proceeds, Certification fees
Documented money map
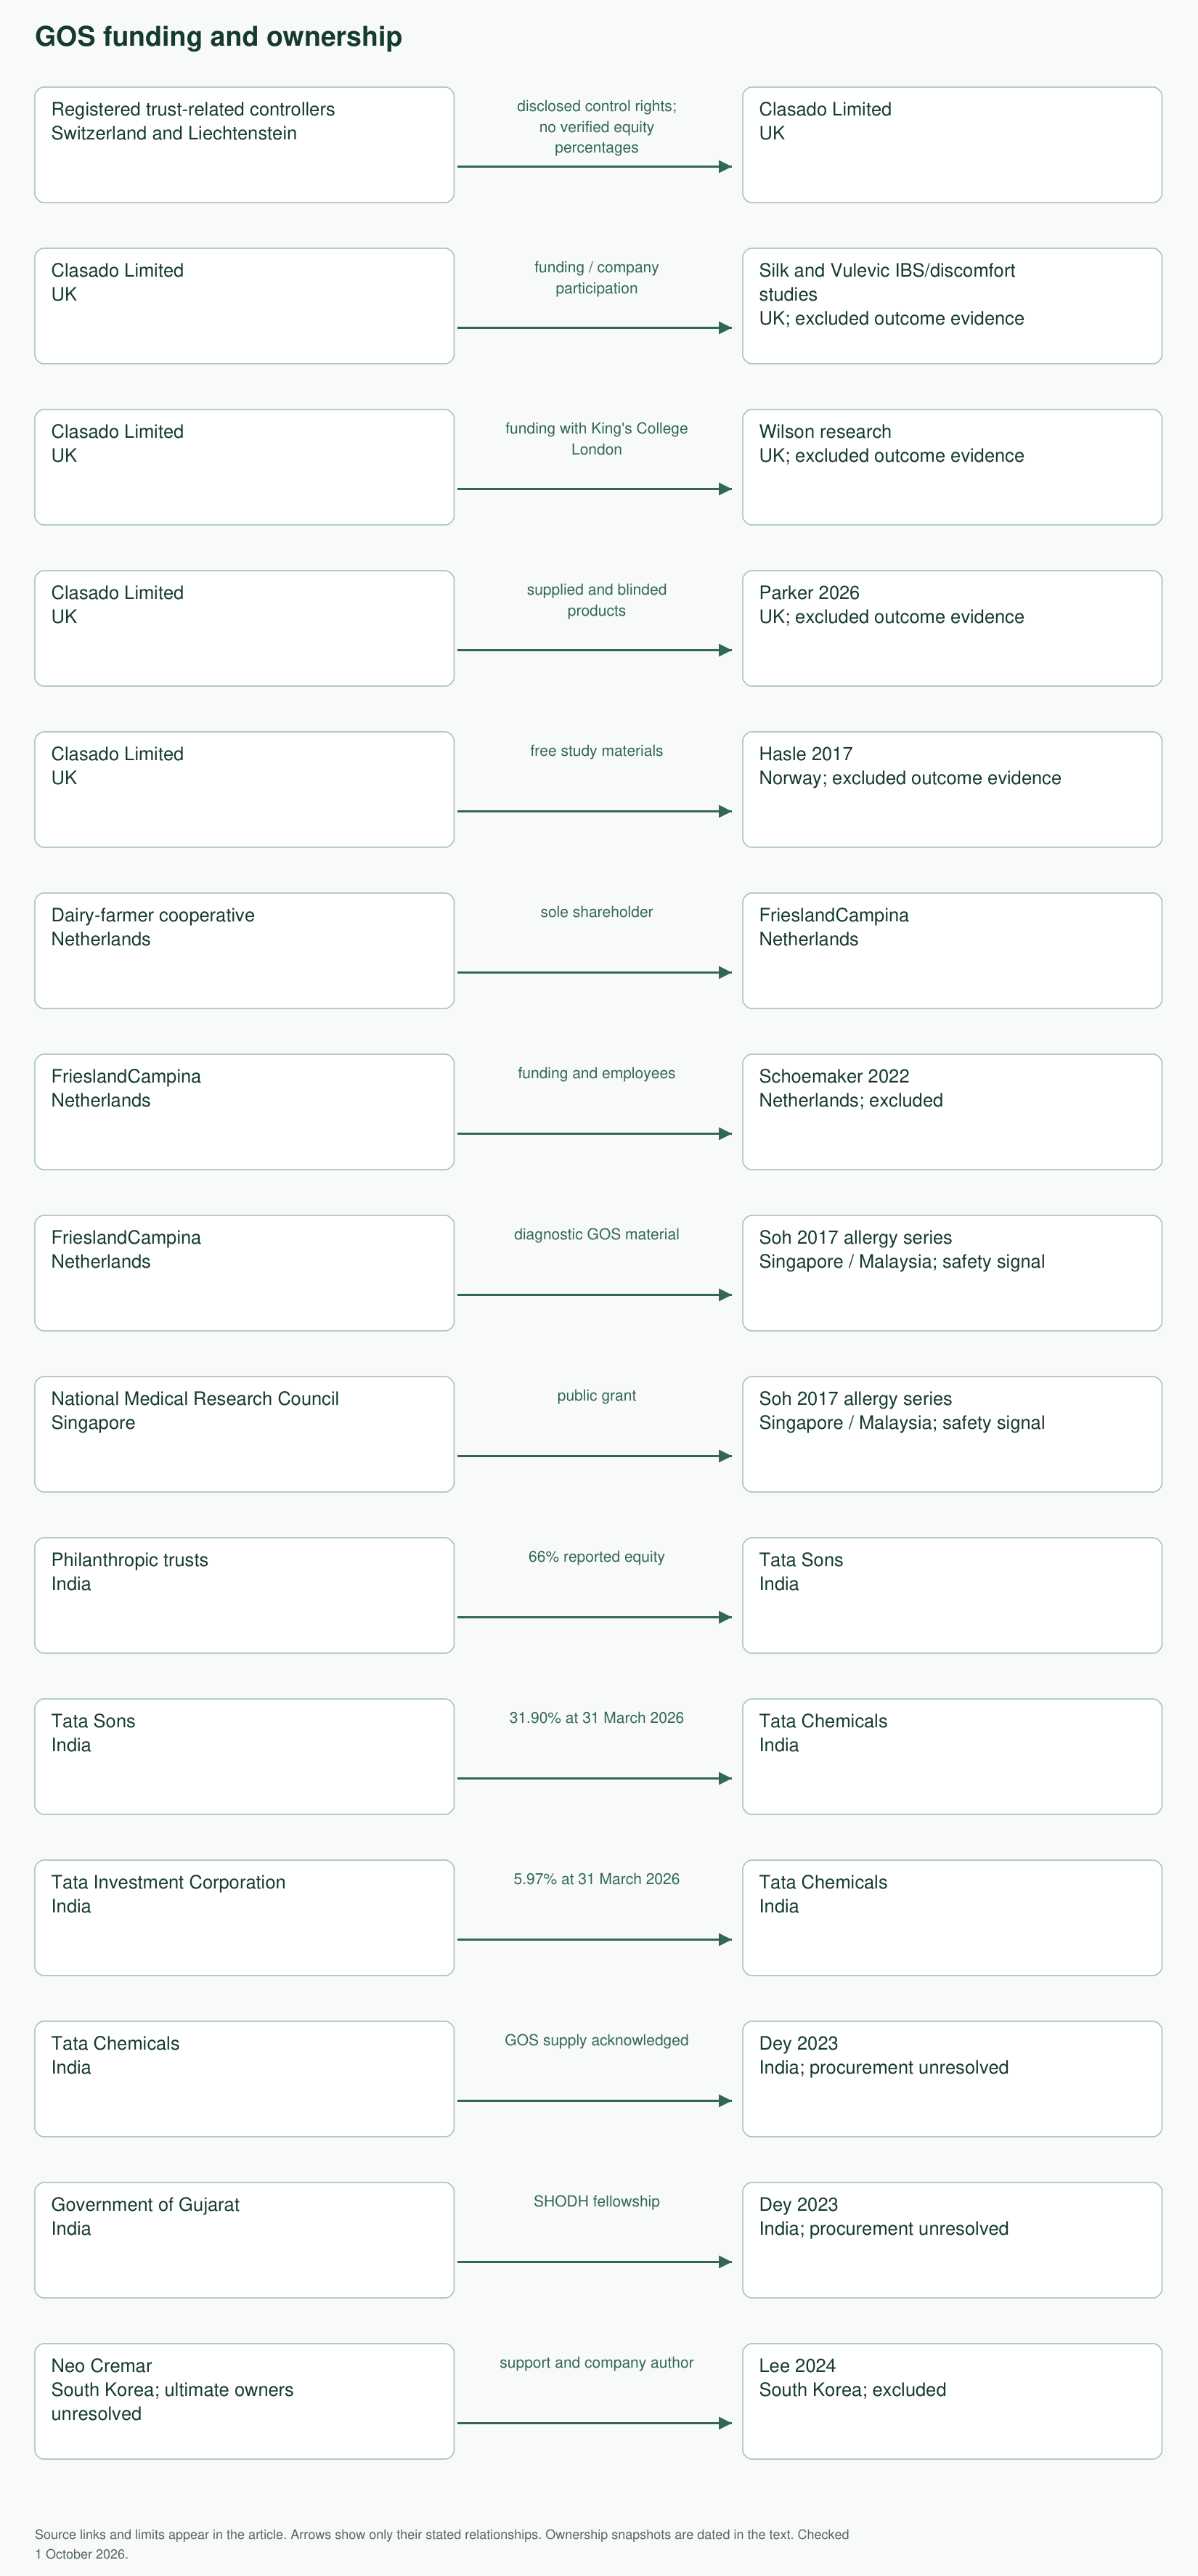
Arrows mean the relationship written on them. They do not imply that all listed businesses share an owner, or that a trustee/controller directed a study.
Accessible relationship list:
- Registered trust-related controllers → control rights over Clasado Limited; beneficiaries and equity percentages remain unresolved
- Clasado → funding or commercial participation in the UK IBS/discomfort and Wilson research; manufacturer supply/blinding in Parker and free materials in Hasle
- Netherlands dairy-farmer cooperative → sole shareholder of FrieslandCampina → funding/employees in Schoemaker and diagnostic material in Soh
- Singapore NMRC → public grant for Soh; that grant does not remove the product-support link
- Indian philanthropic trusts → reported 66% equity in Tata Sons → 31.90% of Tata Chemicals at the filing date; Tata Investment Corporation → 5.97%
- Tata Chemicals → acknowledged GOS supply for Dey; Government of Gujarat → SHODH fellowship for the same research
- Neo Cremar → support and a company author in Lee; ultimate ownership not established
Relationship sources are the primary disclosures linked above and the study-specific references below. A supply acknowledgment without clear payment terms does not prove a donation or an independent purchase. Such unresolved studies are held outside the independent verdict pending clarification.
Regulatory status
The FDA currently lists GOS among additional non-digestible carbohydrates for which it intends to exercise enforcement discretion for dietary-fiber labeling pending rulemaking. Its 2018 science assessment relied on calcium-absorption evidence for that physiological classification. This is not approval of GOS as an IBS or constipation medicine, nor a finding that this review's independent-funding rule has been satisfied. FDA current Q&A, FDA science review
EFSA's 2011 and 2014 Bimuno opinions did not establish the submitted gastrointestinal-discomfort claim. These are historical assessments of specific dossiers, not a verdict on every later study or all GOS products. 2011 opinion, 2014 opinion
EFSA’s historical 2024 budget identifies EU/EFTA contributions and grant-related revenue; its current policy describes conflict management. Neither clears all historical panel disclosures or underlying applicant trials. GAO’s agency-wide FDA review describes appropriations and industry user fees over 2008–2024, particularly for drugs and tobacco; it does not verify a GOS-specific financial transaction. An industry study retains its provenance when a regulator assesses it. 2024 EFSA budget, Current policy overview, GAO agency-finance overview
FAQs
Is GOS a probiotic?
No. It is a carbohydrate substrate, not a live microorganism. A product combining GOS with a probiotic must be evaluated as that particular combination.
Is GOS naturally found in beans?
The word is used for alpha-galactosides in legumes as well as manufactured beta-GOS. The linkage distinction matters. Research on one should not automatically be transferred to the other.
Can GOS improve symptoms even if the studies are commercially supported?
Commercially supported studies can report real effects. The selected sources contain positive, null and exploratory findings, but they do not provide a fully verified independent-only estimate applicable to every preparation or patient. That financial limitation does not establish that GOS cannot help. Discomfort trial, Constipation trial, Korean trial, Gummy trial
Is an increase in bifidobacteria always a good result?
It is a biological measurement. Its clinical meaning depends on whether health or symptoms improve in an appropriate comparison. There is no universal target count established here.
Is GOS safe for lactose intolerance or milk allergy?
Check the exact preparation. Residual lactose and individual tolerance matter, while milk allergy is a different issue. Low-lactose wording is not evidence that a milk-allergic person can safely use the product.
Do studies in infant formula prove that adults should take it?
No. Age, nutritional matrix, co-ingredients and clinical outcomes differ. Formula research also does not authorize adding a supplement to an infant's bottle.
Can it replace laxatives, lactase or treatment for colitis?
The audited evidence does not establish those substitutions. Changing treatment requires a condition-specific clinical assessment.
What is the best dose?
No universal dose is established by these selected studies. Mixture weight, active GOS, degree-of-polymerization definitions and fiber content differ. The table records attributed exposures and a cross-publication discrepancy; it is not a self-treatment schedule. Composition table, 2020 report, 2023 report
Sources and funding
Source credibility scorecard
Tiers and A–D grades are provisional editorial descriptions of interests and fitness for a stated source role, not formal GRADE certainty or proof that every financial chain is known. Tier 1 means no relevant stake identified in available disclosures, Tier 2 indirect ties, Tier 3 an interested party, Tier 4 direct commercial origin or support, and U unresolved provenance. A covers accountable primary records, B sources with limits, C interested or materially uncertain sources, and D direct self-interest for the specified use. An ordinary product purchase is not automatically sponsorship; an official or academic source does not automatically clear trial financing.
| Source | Funding or revenue model | Country or jurisdiction | Tier and grade | Accuracy incentive and remaining limitation |
|---|---|---|---|---|
| Silk 2009 and ISRCTN54052375 | Clasado sponsorship/funding | UK; registry UK | Study and sponsor-entered record 4/C; registry infrastructure separate | Original abstract, registry and EFSA assessment read; full trial methods/tables/disclosures unavailable; small complete-case dataset |
| Vulevic 2018 | Clasado grant; company employment links | UK | 4/C | Full relevant original read; short, symptom-selected crossover; same 91-person study assessed in EFSA 2011, not replication |
| Schoemaker 2022 | FrieslandCampina funding and employees | Netherlands | 4/D for independent outcome use | Full main report and tables read; primary and prespecified subgroup inconclusive, selected post-hoc findings positive |
| Lee 2024 | Neo Cremar support; company author | South Korea | 4/C | Public original main transcription and tables read; selected clinical outcomes, between-group microbial nulls and statistical-label inconsistency |
| Dey 2023 | Gujarat SHODH fellowship; Tata supply terms unresolved; Syri Research laboratory coauthor | India | U/C provisional | Original abstract and financial sections read; complete methods/tables inaccessible; separate formulation paper does not settle clinical-batch purchase |
| Davis 2011 | USDA program plus GTC Nutrition grant/product; adviser tie | USA | 4/C | Full relevant main methods/results/disclosures read; 18-person sequential microbial experiment, not a clinical efficacy trial |
| Wilson 2020 and 2017 conference abstract | Clasado doctoral support | UK | 4/C | Original abstract and complete published conference abstract read; same 69-person cohort as the 2023 report, not replication; full 2020 main paper unavailable |
| Wilson 2023 and prospective registry | Clasado and King's College London; author industry grants and invention interests | UK | 4/C | Full relevant published original and registry read; exploratory secondary predictors, author commercial/patent ties and unresolved dose definition |
| Wilson 2021 colitis pilot | Clasado and King's College London | UK | 4/C | Full relevant original read; open-label attrition, clinical disease/remission nulls and exploratory stool findings |
| Hasle 2017 and ISRCTN74669614 | Oslo travel clinic; free Clasado materials | Norway; supplier UK | Study and sponsor-entered record 4/C; registry infrastructure separate | Original abstract and registry read; positive protocol-adherent but inconclusive evaluable comparison; main methods/disclosures unavailable |
| Vulevic 2015 and original paper | Clasado funding, product supply and design/writing participation; two employees | UK | 4/C | Full relevant methods/results/tables/disclosures read; mixed biomarkers, no clinical infection-prevention endpoint |
| Parker 2026 | No funding declared; Clasado supply and blinding; payment terms unstated | UK | 4/C | Full relevant original read; selected peak-change result, overall marker null and limited symptom signals; purchase/donation terms unresolved |
| Gough 2025 | Partial Clasado funding | UK | 4/C | Full main original and table read; 18-person null pilot, low baseline symptoms; supplement and support contract unresolved |
| Ashley 2012 | Mead Johnson research support and employees | USA | 4/D for independent outcome use | Relevant original main sections and composition table read; other table cells not all assessed; formula co-ingredients and infant population limit transfer |
| Soh 2017 | Singapore NMRC grant; FrieslandCampina diagnostic material | Singapore and Malaysia; supplier Netherlands | 4/C | Full main case series and clinical table read; five of six met anaphylaxis criteria; no population incidence estimate |
| Harthoorn 2025 | Clasado funding; company and contract-laboratory authors | UK and Belgium | 4/D for independent outcome use | Full main original read; eight adult-donor fermentation cultures, not a human dosing or efficacy trial |
| Production chemistry review, 2019 | EU Horizon 2020; Argentine and Portuguese public programs; PREMIUM includes industry partners | Argentina and Portugal; EU | 2/B for chemistry | Relevant chemistry and disclosure sections read; public grant record identifies consortium industry participation, not control of review conclusions |
| Dey formulation report, 2023 | University/laboratory assistance; funding statement “Not applicable”; Tata GOS explicitly purchased | India | U / B for formulation and purchase description | Relevant main formulation methods/disclosures read; table cells not all assessed; a separate small sensory/storage study does not establish clinical-batch procurement or complete independence |
| CORDIS PREMIUM grant record | EU public budget | Belgium / European Union; consortium multinational | 1/A for grant facts | Primary funded-project record; not an efficacy source |
| NIDDK lactose and constipation pages | US federal health institution | USA | 1/A for clinical context | Public-health accountability; general guidance, not GOS trials |
| NHS anaphylaxis page | Public health-service resources | UK | 1/A for emergency context | Clinical review and public accountability; no GOS-specific incidence claim |
| FDA Q&A and scientific assessment | Government appropriations plus agency-level user fees | USA | 2 institutionally/A for regulatory record | Current labeling guidance and relevant 2018 GOS assessment read; agency finance is contextual, not product-specific support or clinical approval |
| EFSA 2011/2014 opinions, 2024 budget and policy overview | Historical EU/EFTA and grant-related revenue; assessments of commercial applicant dossiers | Italy / European Union | Official role / A for regulatory record; individual financial provenance not fully traced | Relevant original assessments, historical budget and policy overview read; detailed panel forms and underlying unpublished trial contracts unverified |
| GAO FDA funding overview | US legislative-branch public funding | USA | 1/A for agency-financing context | Government audit mandate; not a GOS study |
| Monash guidance, app and fee disclosures | University resources; app sales and certification fees | Australia | 3/B for chemistry/context; no independent outcome reliance | Specialist expertise and public disclosure; commercial program interests |
| Clasado contact and UK control register | Seller revenue/capital; UK public registry | UK; listed controllers in Switzerland/Liechtenstein | Company 4/C for identity; registry 1/B | Primary identities/control notices; filed data not a complete beneficial-owner audit |
| FrieslandCampina 2025 report and 2026 announcement | Dairy sales and cooperative/member capital | Netherlands | 4/C for corporate facts | Reporting accountability; promotional interests; no efficacy use |
| Tata Chemicals FY2025–26 filing and Tata Sons disclosure | Commercial revenue/shareholder capital; upstream trusts | India | 4/C for corporate facts | Dated ownership disclosures; no inference of charitable research independence |
| Ritter 2019 Form 10-K | Developer financed by investors and other capital | USA | 4/C for disclosed trial failure | Securities-law accountability; historical corporate account, not independent raw trial analysis |
| Medtrition Floratrol label | Product sales | USA; ultimate owners not traced | 4/C for label facts; D for promotion | Legal labeling duties; current formulation can change |
The clinical record is geographically varied but concentrated around a few commercial ingredient programs, particularly Clasado in the UK and FrieslandCampina in the Netherlands. Multiple countries and journal titles should not be mistaken for independent replication. Government grants, university affiliations and publication in an open-access archive do not establish independence by themselves.
Scope and unresolved questions
Scope: selected digestive, biomarker and safety evidence, not an exhaustive systematic review. Full relevant originals were recovered for several trials, while Silk, Hasle, Dey’s clinical report and Wilson 2020 retain main-paper or table gaps. Other records verify only specific guidance, financial disclosures or dated corporate relationships. Private supply contracts, some supplements and individual financial forms remain unavailable. No complete independent-only trial census, pooled efficacy estimate, retail-lot certification or brand ranking is claimed.
Gaps include complete current ownership chains for several historical sponsors, some study-product procurement terms, upstream donor histories, adequately powered independent replication, long-term clinical outcomes and comprehensive medicine-interaction testing. Source affiliation, nationality and funding are disclosed as context; none alone determines whether a claim is true.
Last reviewed: 3 October 2026
Have a question — or want us to cover something?
Ask about anything on this page, or request the next deep dive: an ingredient, a supplement, or a health concern. We use published research, evidence syntheses, and regulatory guidance, with clear source links.
One daily research roundup
Get the topics, key findings and links from our new articles in one email. At most one digest a day, only when there is something new.