
Key takeaways
- Butyrate is a normal microbial metabolite with important intestinal biology. That does not establish that swallowing extra butyrate treats a digestive disorder (Human biological context).
- Human studies contain promising findings, especially as an addition to usual ulcerative-colitis treatment, but products, populations and results differ (Adult UC trial; Pediatric null trial; Pediatric positive report).
- Positive reports reviewed here include company funding, donated preparations or product transactions left unreported. A dependable general retail-product benefit is not established under the strict financial screen used here (Funded combination trial; Donated UC preparations; UC trial and unresolved supply terms).
- Sodium butyrate, calcium or magnesium salts, tributyrin, fibre fermentation and rectal preparations are different exposures (Tributyrin composition; Sodium exposure; Rectal experiment).
- “Well tolerated” in a small, short trial is not a guarantee of long-term safety. One randomized trial found higher daytime blood pressure with oral sodium butyrate in people with hypertension (Original safety signal).
Butyrate deserves research, but these studies do not establish a general “gut repair” supplement. Selected short-term outcomes, especially UC add-on outcomes, are promising; confidence in a reproducible general retail-product benefit is low because methods, formulations and financing differ. It should not replace assessment of persistent symptoms or prescribed IBD care. Bleeding and dehydration require medical assessment (UC outcomes; Blend outcomes; Barrier pilot; Bleeding warning signs; Diarrhea and dehydration warnings).
Contents
Evidence summary · What it is · Forms and delivery · Mechanism · Hype · Benefits · Verdicts · Risks · Interactions · Who should avoid · Research exposures · Laboratory evidence · Funding and limits · Regulation · FAQs · Sources
Evidence summary
The strength column is an editorial judgment after the finite financial screen below, separate from the clinical certainty assigned by an original study or review. Company-supported and financially unresolved findings remain visible. A public grant or no-conflict declaration does not resolve all payments, product transactions or author relationships.
| Claim | Evidence | Source | Funding/conflict | Strength |
|---|---|---|---|---|
| Relieves IBS symptoms | 79 randomized; 66 completers. Selected symptom frequencies improved, broader severity did not | Banasiewicz 2013; Full original | Complete paper has no dedicated funding/COI or product-payment statement | Insufficient independent confirmation |
| Improves IBS with a combined biotic product | 120 randomized; 101 per-protocol completers. Adequate relief favorable at week 4, not weeks 8 or 12 | Gąsiorowska 2025 | DSM-Firmenich funding, company employees and licensed blend | Combination context only |
| Helps induce adult UC remission alongside treatment | ITT clinical remission favorable; complete endoscopic remission not significantly better | Karłowicz 2025 | Explicit Polpharma donation plus author interests | Promising; excluded from strict independent-benefit basis |
| Helps children with newly diagnosed IBD | One null trial; one positive report with masking and text/table reporting limits | Pietrzak 2022; Goldiş 2025 | Different author disclosures; supply terms unreported | Inconsistent; insufficient |
| Prevents diverticulitis | Favorable small study with predictable allocation and substantial attrition | Krokowicz 2014 | No conflicts declared; full financing/procurement unresolved | Insufficient for prevention advice |
| Repairs intestinal permeability with tributyrin | Healthy-adult pilot did not improve measured permeability | Smith 2024 | NutriScience funding, employee and board ties | No established clinical repair benefit (Full original pilot). |
| Is harmless because it is naturally produced | Blood-pressure increase in one small randomized trial | Verhaar 2024 | Public/foundation support with disclosed indirect commercial interests | Meaningful safety signal; not a universal risk estimate |
What it is
Butyrate is the ionized form of butyric acid, a four-carbon short-chain fatty acid. Gut microbes produce it while fermenting certain carbohydrates. Colon-lining cells use it as an energy source, and it also participates in cellular signalling. These physiological roles explain the interest in supplementation; they do not establish a deficiency diagnosis or a treatment target for an individual. Human formulation and biological context
This review concerns digestive claims for swallowed butyrate salts and the related butyrate-releasing compound tributyrin. Rectal studies are identified separately. Dietary fibre, foods, butyrate-producing bacteria and purified metabolites cannot be treated as interchangeable interventions. Butyrate itself is not a living probiotic.
Forms and delivery
| Form | What differs | Why it matters |
|---|---|---|
| Sodium butyrate | A salt supplying butyrate and sodium | The salt amount, butyrate amount and total capsule weight can differ (Sodium-matched formulation). |
| Calcium or magnesium butyrate | Different accompanying mineral and formulation | Evidence for sodium formulations does not automatically transfer (Different exposures). |
| Microencapsulated or delayed-release products | Lipid matrices, polymers and other coatings | Release location and tested composition are part of the intervention (Microencapsulated trial). |
| Tributyrin | A triglyceride that releases butyrate after hydrolysis | Milligrams of tributyrin are not milligrams of sodium butyrate (Tributyrin preparation). |
| Butyrate plus probiotics or fibres | Multiple active components | A positive result cannot identify which component helped (Combined intervention). |
| Rectal butyrate or mixed-SCFA preparations | Direct delivery to the distal bowel | Results do not establish oral-capsule effectiveness; these are not home-preparation instructions (Rectal research exposure). |
For example, Smith's study tested a powder containing 50% tributyrin with other ingredients. A 200 mg complex supplied 100 mg tributyrin. Product names and headline capsule weights can therefore mislead if the actual active amount is not checked. Formulation details
“Colon targeted,” “postbiotic,” “clinical strength” and “pharmaceutical grade” are not evidence of clinical benefit. A formulation or dissolution description must be assessed separately from the outcomes of the exact product studied. The reports reviewed here do not validate these marketing phrases as efficacy standards.
How it works
Proposed actions include providing energy to colonocytes, influencing inflammatory signalling, altering gene regulation through histone-deacetylase inhibition, and changing epithelial transport or barrier function. Much of the detailed pathway evidence comes from cells, animals or biopsy experiments. Dose, release location, disease activity and the surrounding microbial community can change the response (Experimental barrier study; Gene and clinical outcomes).
Scharf’s 2025 study exposed the colon to 100 mmol/L butyrate for 90 minutes during colonoscopy, then challenged biopsies with deoxycholate in Ussing chambers. Challenged IBS tissue had a favorable transcellular result (p=0.034); paracellular and unstimulated permeability did not improve. This is not a chronic oral symptom-relief trial. Support included Swedish public grants, EFSD/Novo Nordisk and Lantmännen R&D; SAFC Pharma reagent payment terms were unstated (Original methods, results and funding).
Stool butyrate is not a direct measure of all production or tissue use: material can be absorbed before stool collection. Neither a stool change nor a microbiome change alone demonstrates clinical healing. The studies reviewed here measured biological and clinical outcomes separately (Biological context; Stool correlations and clinical outcomes; Separate stool and permeability measures).
Hype versus evidence
- “It feeds the colon, so more must be better.” A normal biological substrate still needs dose-specific efficacy and safety testing when supplemented (Dose-specific safety signal).
- “A larger microbiome diversity score proves recovery.” Microbiome changes are not automatically beneficial and are not a substitute for symptoms, remission or other clinical outcomes (Microbiome and clinical outcomes).
- “Thousands of patients improved.” A large uncontrolled series cannot separate supplementation from usual care, expectation and fluctuating symptoms (Uncontrolled series).
- “The study was randomized.” Randomization to two active doses is different from a sustained placebo comparison; predictable odd/even allocation is also weaker than concealed random assignment (Two active doses; Predictable allocation).
- “A university study is independent.” Public grants, company-supplied products, author relationships and procurement need separate checks (Company support; Public grant and supply terms).
- “Butyrate treats leaky gut.” A broad marketing label does not specify a diagnosis, a validated treatment target or an outcome demonstrated by a particular product (Measured permeability outcome).
Benefits by claim
Irritable bowel syndrome Insufficient independent evidence
Banasiewicz’s trial randomized 79 people (41/38) and analyzed 66 completers (34/32). Debutir 300 mg/day for 12 weeks was added to ongoing IBS treatment. Selected symptom frequencies and adequate relief favored butyrate; broader symptom severity did not. The complete six-page original does not state dedicated funding, author COI or product purchase/donation terms. Allocation concealment and multiplicity adjustment were not reported (Primary record; Complete original paper).
Lewandowski enrolled 3,000 people and collected 2,990 questionnaires after 12 weeks of Intesta 150 mg twice daily. The uncontrolled before/after questionnaire was not validated, and physicians could change other treatment. Symptoms improved, but supplementation cannot be isolated from usual care, expectation or fluctuation. There were 182 discontinuations, including 121 for lack of effect. Bioton partly funded the study; remaining cash and supply terms were unstated (Original methods, results and funding).
Gąsiorowska randomized 120 people; analysis used 101 completers. The daily blend supplied 300 mg sodium butyrate, five probiotic strains totaling 2 billion CFU and 128 mg short-chain FOS. Adequate relief favored it at week 4 (64.7% versus 42.0%), but not weeks 8 or 12; overall IBS severity and QOL did not differ. DSM-Firmenich funded and supplied the arms, with company employees among the authors. This is mixed evidence for the blend, not isolated butyrate (Full original trial and disclosures).
Digestive symptoms in type 2 diabetes and SIBO claims Insufficient
Panufnik randomized 52 adults with type 2 diabetes and IBS; its main change table includes 47 after withdrawals although the analysis is labeled ITT. Symptom resolution and breath-test conversion favored butyrate, with a small HbA1c change; between-arm HOMA-IR did not. The questionnaire was not validated, registration was retrospective and no formal power calculation was reported. Methods describe pain severity, whereas Results emphasize resolution. A breath-test change is not proof of durable SIBO eradication. Bioton provided both preparations with payment terms unstated; the 2024 conference abstract separately disclosed Franek and Rydzewska commercial interests (Full final original; Original preliminary disclosure).
Adult ulcerative colitis Insufficient independent confirmation
Karłowicz randomized 107 adults, with 98 available at 8 weeks. The ITT clinical-remission counts were 16/54 versus 3/53. Clinical and endoscopic improvement favored add-on butyrate; complete endoscopic remission did not significantly differ. Endoscopy was unblinded, recruitment preceded registration and long-term, histological and QOL benefits were not assessed. Polpharma explicitly donated active and placebo; relevant author fees and a Sanprobi shareholding were disclosed. The positive result remains visible outside the strict independent-benefit basis (Original UC trial; Dated registry).
Firoozi’s two reports describe one 36-person trial with 30 completers, rather than independent replications. Partial Mayo and selected inflammatory measures favored butyrate. The 2024 paper also reported sleep/QOL changes; its primary question concerned calprotectin and clock genes. INSF grant 4004581 financed the trial and BodyBio provided capsules, with payment terms unstated. Methods specify 600 mg/day, while abstracts contain inconsistent mg/kg wording. Missing-data and multiple-outcome reporting require caution; abstract doses are not prescribing instructions (2025 publisher record; Full 2025 original; 2024 publisher record; Full companion original).
These studies tested an addition to care. They do not justify replacing prescribed anti-inflammatory treatment or imply prevention of surgery, cancer or long-term relapse (Add-on care; Selected short-term UC trial).
Crohn's disease and broader IBD Insufficient
Facchin’s 2020 pilot randomized 57 adults and analyzed 49 with UC or Crohn’s disease, most already in remission. Clinical activity and calprotectin did not show a clear between-arm advantage. QOL improved within the 14-person treated UC subgroup; this is not an established placebo-controlled QOL benefit. Academic grants, Italian IBD-group support and SILA unrestricted funding plus preparations were reported (Publisher record; Full original methods, tables and funding).
Facchin’s 2026 report randomized 152 adults and analyzed 140 completers. Its main question was microbiome composition; disease activity, calprotectin and QOL were secondary. Both active and inactive IBD were included, and several favorable statements concern within-group change. No endoscopic improvement/remission outcome or independently validated enterotype treatment rule was established. Padua support and SILA grant/preparations were disclosed, with SILA-related author interests. Relevant Methods, patient flow, limitations and finance were read from indexed original passages; the complete numerical tables and supplements were not recovered (Original abstract and COI; Publisher report; Indexed institutional original).
Pediatric inflammatory bowel disease Insufficient and inconsistent
Pietrzak's Polish trial had 72 completers and found no added benefit for remission or disease activity after twelve weeks. The study used university statutory funds and declared no external research funding; public academic funds covered article-processing charges. An author reported lecture fees from Alfasigma, Polpharma and Berlin-Chemie. Product procurement remains a separate question. Pietrzak 2022
Goldiş reported remission in 36/44 versus 21/44 children after 12 weeks. Internal Victor Babeş University funds and no author conflicts were declared. Allocation concealment, masking, placebo composition/provider and power were insufficiently reported. Text and Table 3 reverse the severe-disease counts, and the Figure 3 narrative describes a nonsignificant 12-week score comparison despite stronger clinical language elsewhere. These inconsistencies reduce confidence in the positive report; product procurement also remains unreported (Complete original report).
Diverticular symptoms and prevention Insufficient
Krokowicz allocated 73 people by odd/even medical-history numbers; 52 completed 12 months. Reported symptom-defined episodes were 2/30 versus 7/22, with imaging-supported episodes 1/30 versus 5/22. Predictable allocation, attrition, few events and the symptom definition limit prevention inference. Authors declared no conflicts, but the full main paper does not state cash or Debutir supply terms (Original main methods, outcomes and COI).
Tursi’s retrospective study retained 59 of 72 patients. Pain decreased from median 5 to 1 without a control; stool form did not significantly change. Exclusions included recurrence, diverticulitis and added treatment, making completer selection important. The primary question concerned microbiome composition. No financial support or commercial conflicts were declared, but SILA product payment terms were unstated. Abstract and Methods dose descriptions conflict, so this report does not provide reliable dosing instructions (Full original methods, flow, tables and declarations).
Diarrhoea prevention and general bowel regularity Insufficient
The travelers’ trial randomized 60 people; 42 returned questionnaires. Diarrhea was reported by 1/22 versus 8/20. The capsules combined sodium butyrate with fumaric, citric, sorbic and malic acids. The small, self-reported, 30%-attrition study cannot isolate butyrate. The recovered full paper explicitly names Mifarmex funding and states no sponsor role or competing interests. Funding amounts, ownership and supply terms remain unknown (Primary record; Complete original paper).
Selected constipation or diarrhea symptom changes in IBS studies do not establish effectiveness for every cause of altered bowel habit. The finite reports reviewed here do not establish a dependable independently replicated regimen for chronic constipation, infectious diarrhea or general “microbiome restoration” (Selected IBS outcomes; Uncontrolled IBS series; Travel combination trial).
Tributyrin and intestinal barrier claims Insufficient
Smith enrolled 29 healthy adults; 24 completed a 7-day placebo lead-in and 21 days at one of two active doses. There was no concurrent placebo throughout treatment and no formal power calculation. Measured permeability, microbiome diversity, glucose/insulin and inflammatory markers did not improve; triglycerides increased in the higher-dose group. NutriScience funded and supplied preparations, with employee/board interests and employee authorship. This is a short healthy-adult tolerability pilot, not demonstrated digestive-disease treatment (Publisher record; Full original paper).
What works and what does not
| Claim | Verdict | Notes |
|---|---|---|
| Butyrate has relevant intestinal biology | Established biological rationale | A rationale is not a supplement recommendation (Biological rationale). |
| A particular oral product reliably relieves IBS | Not independently established | Small, mixed and formulation-specific evidence (Small IBS trial; Mixed blend trial). |
| Added butyrate may improve selected UC outcomes | Promising research signal | Short trials, commercial support or procurement uncertainty (Selected UC outcomes; Small UC trial). |
| It can replace prescribed IBD treatment | Unsupported | Trials generally retained background care (Background care retained). |
| Higher stool butyrate proves healing | Unsupported | Surrogate and causal inference are different (Correlations, not treatment target). |
| Tributyrin is clinically superior to every salt | Not established | No adequate comparative outcome basis located (Tributyrin pilot; Different sodium trial). |
| Every formulation is harmless | Unsupported | Safety depends on exposure and population (Population-specific safety signal). |
Risks and reported side effects
| Aspect | Finding | Source |
|---|---|---|
| Gastrointestinal tolerance | Nausea and diarrhoea were reported in an uncontrolled diverticular cohort; attribution was uncertain | Tursi |
| Short tributyrin exposure | Some digestive discomfort; higher-dose group had increased triglycerides | Smith (Actual tolerability and lipid results). |
| Blood pressure | A small trial found higher daytime systolic and diastolic pressure with sodium butyrate | Verhaar |
| Mineral exposure | Sodium-containing products add sodium; calcium/magnesium preparations have their own accompanying mineral | Product composition matters; the hypertension trial sodium-matched its comparator (Sodium-matched comparator). |
| Long-term and vulnerable-population safety | Small selected samples cannot exclude rare harms or establish pregnancy, breastfeeding or general pediatric safety | Trial populations and exclusions described above (Selected children; Short healthy-adult sample; Selected hypertension sample). |
Verhaar randomized 23 people; two withdrew before baseline, leaving 21. The trial stopped early versus the planned 50. Four weeks at 3.9 g/day sodium butyrate, with a sodium-matched comparator, increased daytime systolic pressure by 9.63 mmHg (95% CI 2.02–17.20) and diastolic pressure by 5.08. Whole-24-hour and nighttime differences were not significant. This is a selected hypertension safety signal, not a risk estimate for every dose. Antihypertensive withdrawal occurred under supervision and must not be copied at home (Original trial methods and BP results).
Vomiting blood, black tarry or bloody stool, severe abdominal pain or dehydration requires prompt medical assessment; signs of shock require emergency care. Persistent or worsening diarrhea, especially with IBD or vulnerable health status, should be assessed rather than repeatedly treated with supplements (Bleeding warning signs; Diarrhea warning signs).
Interactions and evidence gaps
| Substance or condition | Mechanism or concern | Severity/status | Source |
|---|---|---|---|
| Hypertension or blood-pressure treatment | Blood-pressure increase in one oral trial | Clinically relevant caution; not a demonstrated interaction with every antihypertensive | Verhaar |
| Diabetes medication | Glycaemic changes occurred in a small study | No established drug-adjustment rule; do not change therapy on this basis | Panufnik |
| Mesalazine, biologics and other IBD medicines | Selected trials retained background care | Co-administration is not comprehensive interaction clearance | UC trial |
| Sodium restriction, kidney or heart disease | Salt and excipient load is product-specific | Requires label-based clinical review, not a universal contraindication inferred from the ingredient name | FDA supplement advice |
| Added probiotics, fibres or minerals | Additional components carry separate effects | Assess the complete preparation | Combination trial |
The papers reviewed here do not constitute a comprehensive human interaction program. That is an access/evidence boundary, not proof that interactions cannot occur. They do not establish a universal spacing interval or justify converting laboratory gene effects into a clinical interaction list (Selected combination trial; Selected add-on UC trial; Gene and clinical research).
Who should avoid unsupervised use
People with unexplained bleeding or significant diarrhea need medical assessment. Active IBD, hypertension, kidney/heart conditions or complex medication use call for review of the exact product and existing care. The selected pediatric trials do not establish a general self-treatment regimen, and the finite papers reviewed here do not establish general pregnancy or breastfeeding safety (Bleeding guidance; Diarrhea warnings; Medicine and label advice; Hypertension signal; Selected pediatric null trial; Selected positive pediatric report).
Laboratory reagents, animal-feed products and improvised enemas are outside the evidence for human oral supplements. Do not replace prescribed medicine or hydration treatment with butyrate (Actual supplement and medicine advice; Hydration/referral guidance; Non-oral laboratory exposure).
Research exposures and clinical instructions
These are research exposures, not suggested doses. They should not be combined into a “safe range” or converted across salts, matrices and tributyrin products.
| Use case | Studied dose or preparation | Duration | Notes |
|---|---|---|---|
| IBS observational series | Sodium butyrate 150 mg twice daily | 12 weeks | Uncontrolled; Bioton-supported; Lewandowski |
| Adult UC add-on trial | Microencapsulated sodium butyrate 300 mg twice daily | 8 weeks | Donated product; background care continued; Karłowicz original |
| Iranian UC study | Methods state 600 mg daily | 12 weeks | Abstract dose conflicts with methods; do not use it as prescribing guidance; Firoozi (Methods dose and abstract discrepancy). |
| Pediatric IBD | 150 mg twice daily in the Polish trial; 150 mg daily in the Romanian trial | 12 weeks | Different studies with conflicting results; Pietrzak, Goldiş |
| Diabetes-associated digestive symptoms | Sodium butyrate 1.5 g daily | 12 weeks | Selected population; Panufnik |
| Tributyrin tolerability pilot | 200 or 400 mg complex, supplying 100 or 200 mg tributyrin | 21 active-treatment days after 7-day placebo lead-in | No sustained concurrent placebo; Smith (Complex versus tributyrin dose). |
Follow the exact product’s label and clinician instructions; a trial formulation should not be assumed interchangeable with an opened, crushed or different product. The studies reviewed here do not establish a universal maximum safe dose, ideal timing or long-term course (Label and clinician advice; Specified trial preparation; Different formulation).
Animal and in vitro evidence excluded from conclusions
Butyrate can affect inflammatory pathways, epithelial cells and microbial communities experimentally. That supports testable hypotheses. It does not establish clinical remission, prevent cancer or justify supplement–drug combinations (Experimental human-tissue outcomes; Proposed gene mechanisms).
Scharf’s acute colonoscopic exposure and challenged biopsy experiment remain distinct from chronic oral treatment. A human-derived tissue outcome is not a patient symptom outcome. Microbial or gene changes alone do not demonstrate that a person will feel better. No animal dose is converted into a human regimen here (Mechanistic experiment; Clinical versus gene endpoints).
Reported funding and financial limits
Research funding at a glance
33 disclosure entries. The counts below summarize independence tiers explicitly assigned in this article. They count disclosures, not studies, funding amounts or evidence quality.
Consult this article’s source and funding notes for named funders, countries, relationships and exceptions where available. Institutional backing, researcher interests and trial sponsorship are separate questions. Public funding alone does not establish independence; commercial ties alone do not prove a claim false. This overview is not a new financial audit.
Who pays and who profits
There is no single owner of the molecule. Companies earn revenue from ingredients, proprietary delivery systems, finished supplements and related health products. The relevant question is who supported each tested preparation and each report.
- Polpharma, Poland: donated the 2025 UC trial preparations. Its June 2026 corporate offer document reports Polpharma Group Holding B.V., Netherlands, as the sole shareholder of Z.F. Polpharma, and identifies Jerzy Starak as the ultimate beneficial owner through the described holding chain. The English document is an informational translation; the Romanian original prevails. Ownership does not prove control over trial conclusions. Trial acknowledgment, company ownership disclosure
- Bioton, Poland: partly sponsored the large IBS series and provided the later diabetes-trial products. Its 2024 management report records Yifan Pharmaceutical’s indirect 31.65% stake through two entities, based on the shareholder list of 11 March 2025. This is a dated ownership snapshot, not a verified October 2026 cap table. Report (Official Chinese corporate identity).
- SILA, Italy: the Butyrose business is based in Noale and sells microencapsulated preparations. It supported the Facchin research. Its sustainability report describes a GAE International holding-company milestone; the accessible material did not establish a complete current beneficial-ownership chain or share percentages. Company, 2024 report
- NutriScience, United States: funded the tributyrin pilot. Frontenac announced a recapitalization in August 2026; its stake and transaction terms were not disclosed. This later ownership event should not be backdated as funding the 2024 trial. Investor announcement (Original 2024 sponsor).
- BodyBio, United States: the Iranian reports identify this product supplier but do not resolve payment terms. The company describes itself as a third-generation family business with manufacturing in Millville, New Jersey. Exact private shareholdings were not verified. Company disclosure (Original supplier statement).
- DSM-Firmenich: financed the IBS combination study and had company coauthors. The trial identifies Kaiseraugst, Switzerland; its governance disclosures describe shareholder nomination rights. The exact current beneficial ownership behind every holding was not established here. Trial, 2025 governance report (Swiss parent and dual headquarters).
Public and nonprofit funding also needs scrutiny
The Romanian pediatric report declares internal university support, while the Iranian work names INSF. Neither statement resolves every product transaction. Verhaar’s safety study lists public and academic funding alongside foundation support and author commercial interests. The Novo Nordisk Foundation is a Danish enterprise foundation whose assets are managed through its wholly owned Novo Holdings; it is not equivalent to an entirely industry-unconnected funding source. These distinctions affect provenance without making a safety finding disappear. Foundation’s own description (Romanian declared funds; Iranian grant and supplier; Safety-study funds and interests).
The finite clinical reports reviewed here include Polish, Italian, Romanian, Iranian, Dutch, Swedish and US settings. Country describes context rather than study quality. Replication should concern a chemically characterized preparation and important patient outcome, with financing disclosed separately (Poland; Italy; Romania; Iran; Netherlands; Sweden-led experiment; US pilot).
Money map
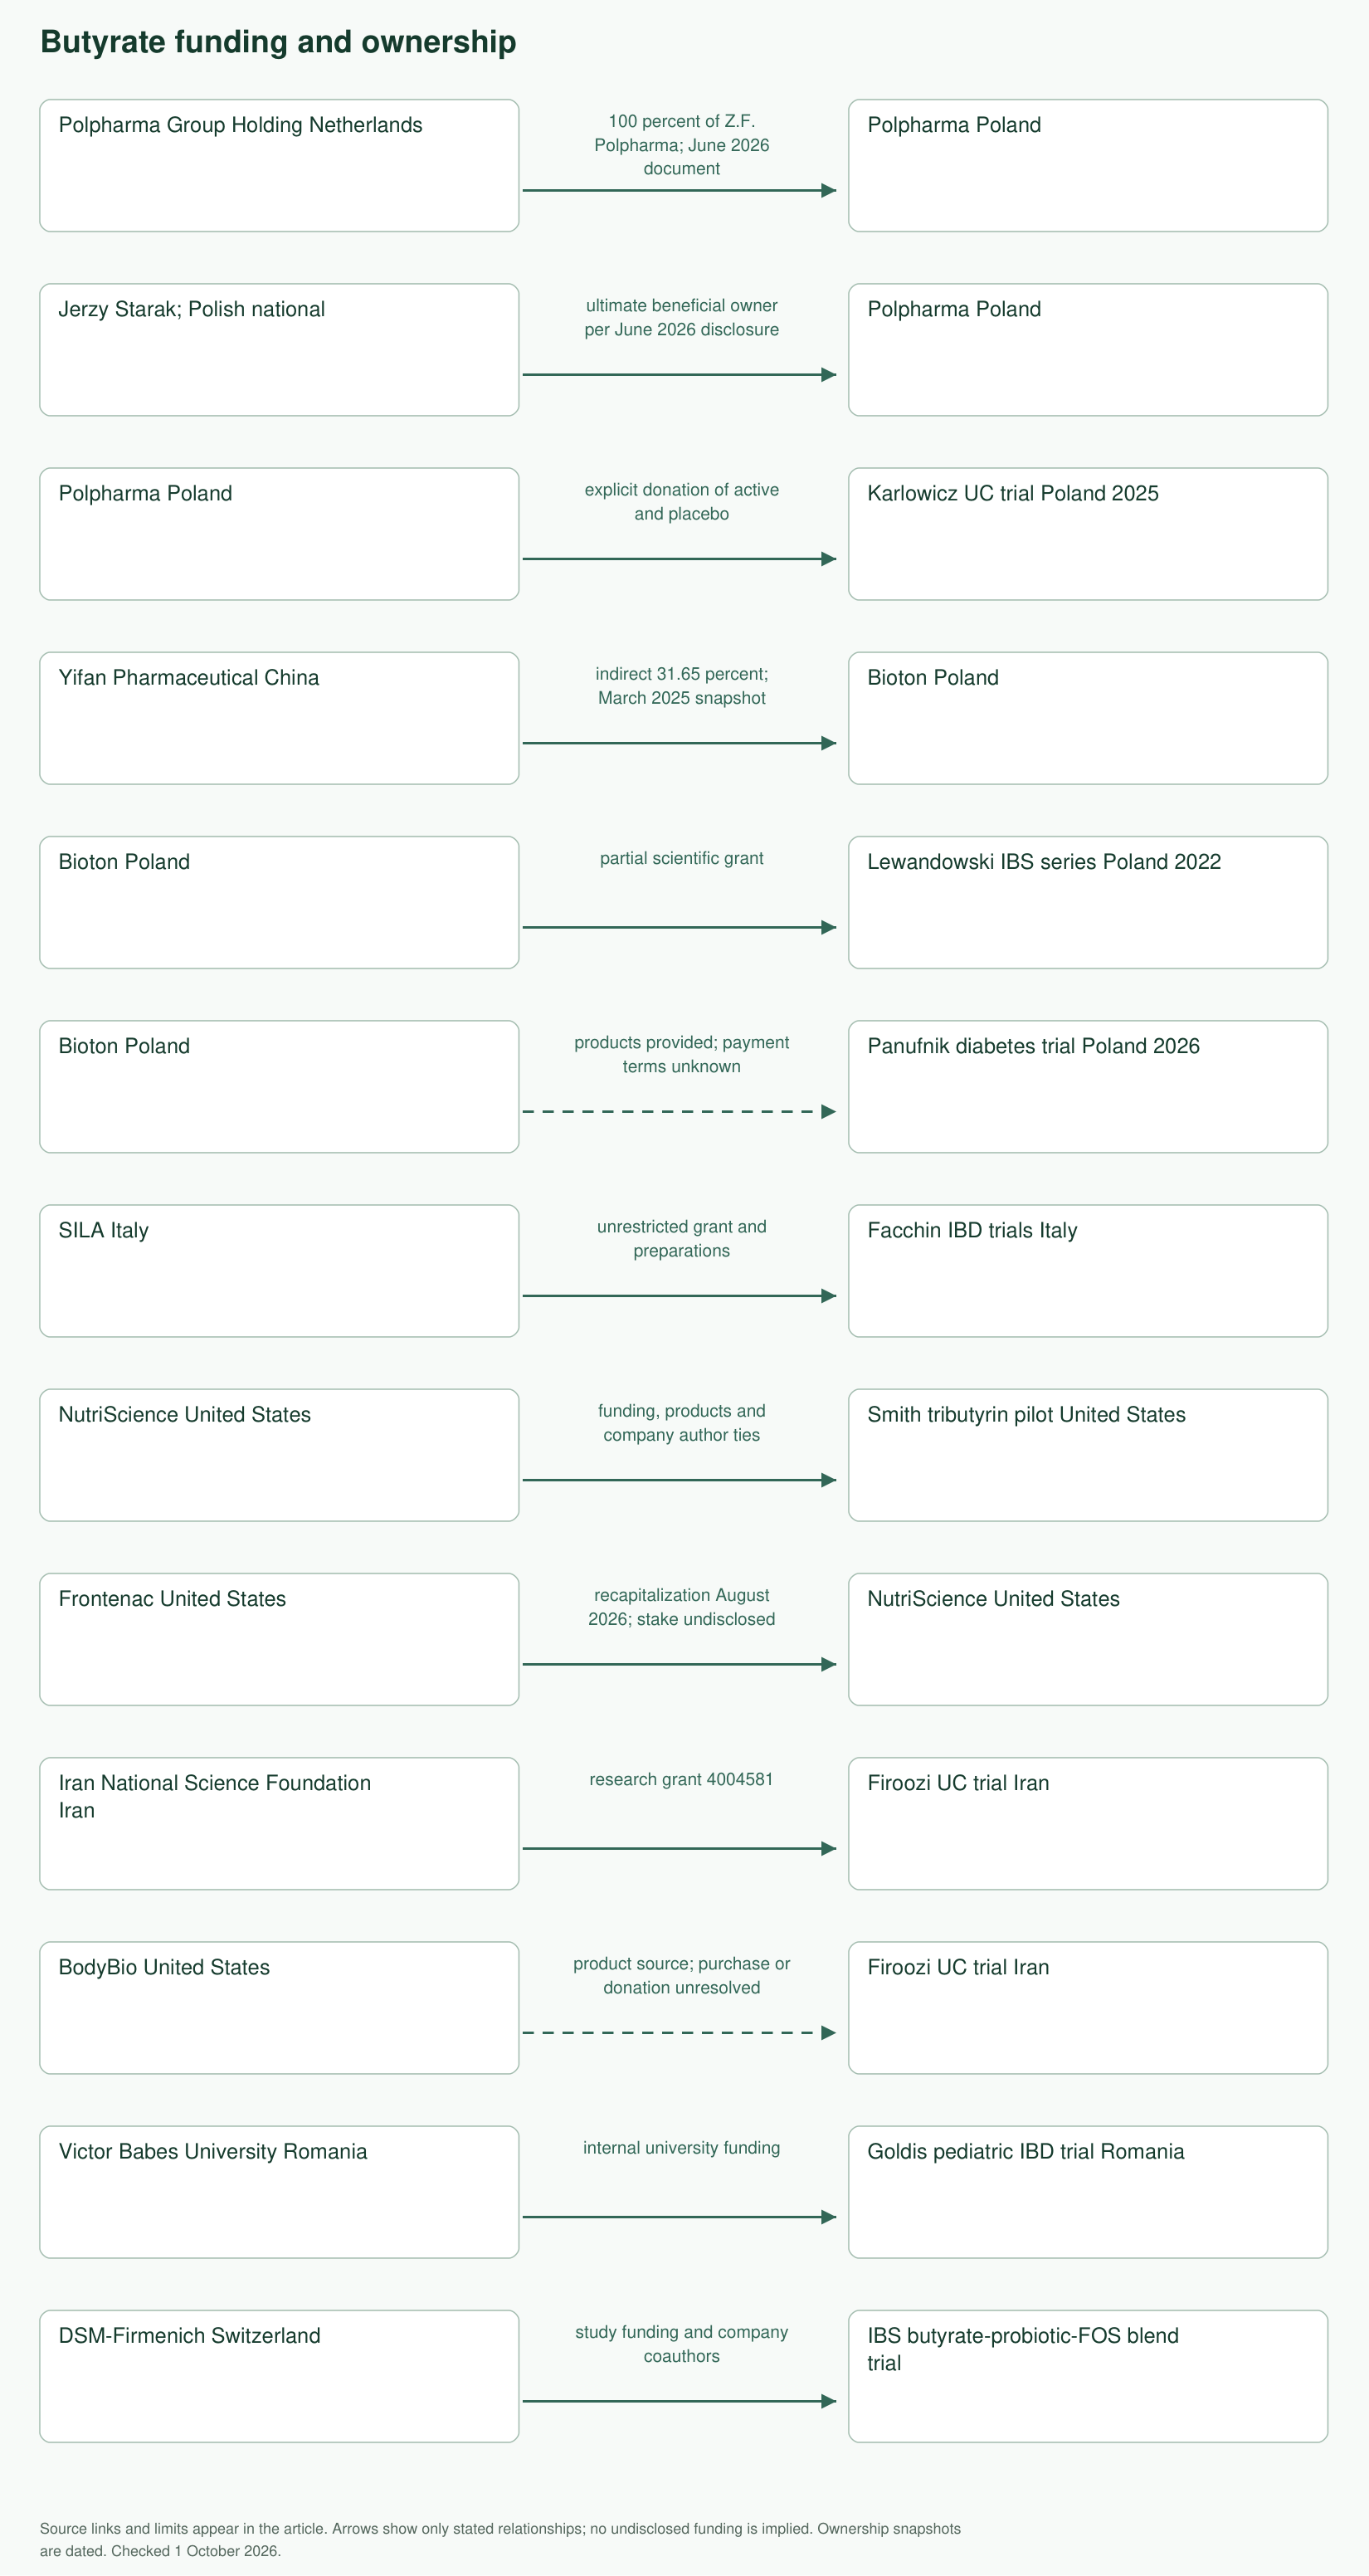
The arrows below show only documented relationships. Dashed arrows mark unresolved transaction terms, not hidden funding allegations.
Plain-text version:
- Polpharma Group Holding, Netherlands → 100% of Z.F. Polpharma, Poland, in the June 2026 disclosure (Dated ownership disclosure).
- Jerzy Starak → reported ultimate beneficial ownership → Polpharma; this is not a direct 100% shareholding claim (Beneficial-owner statement).
- Polpharma → donated preparations → Karłowicz UC trial (Explicit donation).
- Yifan Pharmaceutical, China → indirect 31.65% dated stake → Bioton, Poland (Dated percentage; Chinese identity).
- Bioton → partial grant → Lewandowski IBS series (Partial scientific grant).
- Bioton → preparations provided → Panufnik trial; payment terms unresolved (Preparation provision).
- SILA, Italy → grant and preparations → Facchin IBD research (SILA support; Indexed original 2026 support; Italian location).
- NutriScience, United States → funding, products and author interests → Smith tributyrin pilot (Actual sponsorship and author roles).
- Frontenac, United States → August 2026 recapitalization → NutriScience; stake undisclosed (Dated US transaction).
- INSF, Iran → grant → Firoozi trial (Grant and Iranian affiliation).
- BodyBio, United States → product source → Firoozi trial; donation versus purchase unresolved (Supplier; US company identity).
- Victor Babeş University, Romania → internal funds → Goldiş pediatric trial (Declared internal funds).
- DSM-Firmenich, Switzerland → funding and company authors → combination IBS trial (Funding and company authors; Swiss parent identity).
How this changes the verdict
Clear manufacturer funding or donated materials exclude an outcome from the independent benefit basis. A purchased retail ingredient would not itself constitute sponsorship. Ambiguous “provided” wording stays unresolved. Positive findings are neither erased nor promoted into certainty because of a funder's identity.
The finite evidence reviewed here does not establish a reliable general retail-product benefit after the strict financial screen. This is not proof that butyrate never helps. Better confirmation would require concealed allocation, prospective clinical endpoints, characterized preparations, longer safety follow-up, transparent cash/product terms and independent replication (Small historical trial; Positive donated-product trial; Mixed funded combination trial).
Regulatory status
United States
Dietary supplements are not approved by FDA for safety and effectiveness before marketing. A supplement listing, manufacturing claim or structure/function statement is not approval to treat IBS or IBD. FDA explanation
European Union and product-specific categories
SILA describes Butyrose as a food for special medical purposes. This is a company's product classification, not a blanket clinical endorsement of butyrate. EU rules distinguish foods used for dietary management under medical supervision from medicines. The precise product and national status must be checked; the category alone does not establish effectiveness for a claimed disease. Company description, European Commission framework
Research preparations
A clinical-trial formulation or rectal research preparation is not automatically an authorized self-treatment product. This article does not certify the market status, purity or batch equivalence of every retail brand (US disease-claim boundary; EU category boundary).
Frequently asked questions
Is butyrate the same as a probiotic?
No. Butyrate is a metabolite. A probiotic contains living microorganisms. A combination product needs assessment of both components and the exact strains (Metabolite plus living strains).
Does a low stool result mean I need a supplement?
This review did not identify a validated stool-butyrate threshold that establishes a supplement indication. Stool concentration is not a direct measurement of all production, absorption or cellular use (Biological context; Stool correlation; Stool measurement).
Is tributyrin better than sodium butyrate?
The formulations differ, but a generally superior clinical outcome has not been established. Compare the tested product, dose, population and outcome rather than marketing about delivery alone (Specific tributyrin pilot; Different salt/population).
Can it replace fibre?
A purified metabolite does not reproduce all effects of a fibre-containing food or a specific prebiotic. Those interventions need their own evidence and tolerability assessment (Multiple active components).
Why report positive trials but still give an insufficient grade?
The grade answers a narrower question: what is reliably established after commercial outcome evidence is excluded and missing provenance remains unresolved? It is not a judgment that all positive trials are false (Positive and null sponsored outcomes; Positive donated trial).
Is it safe indefinitely?
That has not been established. Short trials, selected participants and incomplete interaction research cannot provide a universal long-term guarantee (Short selected sample; Specific safety signal).
Sources and funding notes
Tier 1 indicates no identifiable relevant financial stake in the declarations and finite checks available here; Tier 2 indirect ties; Tier 3 interested professional relationships; Tier 4 maker/seller support or affiliation; U unresolved terms. These provisional editorial classifications do not clear every payment, individual interest or underlying donor. A–D grades concern provenance/accountability for the stated use, not clinical methodological certainty. No-conflict statements are reported rather than independently certified.
| Source | Funding, ownership/revenue and country | Tier/grade | Accuracy incentive and remaining gap |
|---|---|---|---|
| Banasiewicz 2013; Complete original | Poland; no dedicated cash, COI or procurement statement in complete six-page paper | U / B provisional | Full main Methods/clinical tables read: 79 randomized, 66 completers; limited frequency signals, broad severity null |
| Lewandowski 2022 | Poland; partial scientific grant from Bioton | 4 / D for efficacy | Original methods disclose uncontrolled design; sales stake and no comparator |
| Gąsiorowska 2025 | DSM-Firmenich funds/prepares/supplies; employees; Nordic Biotic license and Cukrowska position | 4 / D for outcome finance | Full relevant main read; 120 randomized, 101 per-protocol; week-4 relief positive, later relief null; not isolated butyrate |
| Panufnik 2026 | Bioton provided preparations, terms unstated; final no-conflict statement; earlier author interests | 3 / C; procurement unresolved | Full relevant main/back read; 52 assigned, 47 changes despite ITT label; retrospective, nonvalidated, pain-endpoint mismatch |
| Diabetes 2024 conference report | Same Polish study context; Bioton provision and Franek's Bioton research/speaking ties | 3 / C for disclosure context | Primary contemporary disclosure; brief preliminary report, not a second trial |
| Karłowicz 2025 | Polpharma explicit donation; relevant commercial fees and Sanprobi shareholder | 4 / D for outcome finance | Full relevant main and separate financial footnotes read; short follow-up, unblinded endoscopy; ITT clinical remission favorable, complete endoscopic remission nonsignificant |
| ISRCTN14915997 | Polish Ministry institutional sponsor; hospital-clinic funder; Polpharma preparations | 4 / C for provenance/dates | Complete 6-page record read; recruitment 2021–23, registration February 2025; no trial attachments audited |
| Firoozi 2025 publisher; Full original | INSF 4004581; no COI declared; BodyBio supply terms unstated | U / B provisional | Full relevant main/tables/back read; 36 randomized, 30 completers; dose and missing-data/reporting inconsistencies |
| Firoozi 2024 publisher; Full original | Same INSF grant/BodyBio source; Iranian/Canadian academic affiliations | U / B provisional | Full relevant main/tables/back read; same registered cohort, LOCF; calprotectin/clock genes primary; not replication |
| Facchin 2020 publisher; Full original | Padua SID/BIRD, Italian IBD group, SILA unrestricted grant and preparations | 4 / D for outcome finance | Full pertinent main/tables/back read; 57 randomized, 49 available; UC QOL within-group signal, disease activity/calprotectin null |
| Facchin 2026 abstract | SILA-related author fees; indexed original Padua and SILA grant/product statement | 4 / D for outcome finance | Original abstract/COI plus indexed original sections read; full numerical tables and supplements unavailable |
| Facchin 2026 publisher; Institutional original | Padua funds and SILA unrestricted grant/preparations; supplier payment terms unstated | 4 / D for outcome finance | Indexed original Methods, enrollment, limitations and finance read; full direct download failed; no endoscopic endpoint |
| Pietrzak 2022 | Poland; university statutory funds, no external research funding, public academic APC; Alfasigma, Polpharma and Berlin-Chemie lecture fees | 3 / C; procurement unresolved | Null finding retained; mixed pediatric diagnoses and limited power |
| Goldiş 2025 | Victor Babeş University internal funds; no COI declared; product provider/payment unspecified | U / B provisional | Full main/table/caption/back read; positive remission counts, inadequate masking details and internal text/table/figure inconsistencies |
| Krokowicz diverticular trial | No COI declared; complete main has no cash or product-payment statement | U / B provisional | Full main Methods/results/COI read; predictable allocation, 73 allocated/52 complete; separate numeric Table1 not read |
| Tursi 2025 | No financial support or commercial conflicts declared; SILA procurement terms unstated | U / B provisional | Full relevant main/tables/back read; retrospective selected completers, no comparator, abstract/Methods dose conflict |
| Krokowicz travelers record; Full original | Mifarmex funded; sponsor no-role and no competing interests stated; exact payments/ownership unknown | U / B provisional | Full 6-page original read; 60 randomized, 42 returned; mixed acids, self-report, 30% attrition |
| Smith 2024 publisher; Full original | NutriScience grant/products; employee, former employee and board interests | 4 / D for outcome finance | Full pertinent main/tables/back read; healthy adults, 29 enrolled/24 complete, active-dose phase without concurrent placebo |
| Scharf 2025 | Swedish Research Council, EFSD/Novo Nordisk, Lantmännen R&D and Knowledge Foundation; no COI declared | 4 for industry-supported research / C for mechanism | Full relevant main/tables/back read; acute colonoscopic/ex-vivo experiment, selective challenged transcellular finding; no chronic oral patient endpoint |
| Verhaar 2024 | Netherlands-led; academic/ZonMw/NIH, Leducq and Novo Nordisk Foundation support; Caelus, Zehna and other author ties | 2 / B for limited safety use | Randomized sodium-matched comparison; small sample, indirect commercial interests |
| Polpharma ownership document | Polish company-origin transaction disclosure; Dutch holding chain | 4 / C for corporate facts | Formal disclosure accountability; English translation and dated snapshot |
| Bioton 2024 report | Polish listed-company report; China-linked indirect shareholder | 4 / C for corporate facts | Financial reporting accountability; March 2025 holdings not a current cap table (Official Chinese identity). |
| SILA company page | Italy; seller revenue from human/animal nutrition and related products | 4 / D for promotion, C for identity | First-party identity; private ultimate ownership incomplete |
| SILA sustainability report | Italy; company-funded 2024 reporting | 4 / C for dated corporate context | Formal public account; no complete ownership percentages verified |
| Frontenac announcement | US private-equity investor; commercial investment returns | 4 / C for transaction facts | Direct participant; promotional framing and undisclosed terms |
| BodyBio company page | USA; family-owned seller by its own disclosure | 4 / C for identity | Primary self-description; exact ownership not independently verified |
| DSM-Firmenich governance | Swiss corporate issuer with international operations and investor interests | 4 / C for governance facts | Formal annual disclosure; no efficacy inference (Swiss parent and dual headquarters). |
| Novo Nordisk Foundation | Denmark; enterprise foundation with investment/ownership income through Novo Holdings | 2 / C for its own financing description | Public grantmaking accountability; corporate interests disclosed |
| NIDDK GI bleeding | US NIH education; exact page budget/individual editor finances unreported | U / A for clinical warnings | Complete pertinent warning/referral text read; general guidance, not butyrate incidence |
| NIDDK diarrhea | US NIH education; page-specific budget/individual finances unreported | U / A for clinical warnings | Complete pertinent symptom/dehydration/referral text read; general safety, not individual diagnosis |
| FDA supplement guidance | US regulator; agency financing separately sourced to GAO, page-specific budget/individual finances unknown | U / A for regulatory scope | Complete relevant guidance read; not supplement approval or butyrate efficacy |
| GAO FDA funding audit | US legislative oversight; summary reports agency budget authority and user fees | U / A for finite financing facts | Official summary/highlights read; complete audit Methods/report unavailable; no clinical outcomes |
| European Commission FSMP framework | EU public legal institution; page-specific and individual finances not reported | U / A for category scope | Complete pertinent regulatory framework read; not a specific product efficacy/authorization audit |
GAO’s February 2026 summary describes FDA agency-wide funds from budget authority and regulated-industry user fees over 2008–2024. This does not identify who paid for an individual consumer guidance page or imply that a particular supplement seller did so (Official audit summary).
Scope and remaining gaps
This is a focused critical review of the sources cited here through 1 October 2026, rather than an exhaustive registered systematic review. Complete relevant clinical main sections were read where accessible. Facchin 2026 remains limited to original abstract/disclosures and indexed Methods, patient flow, limitations and finance; complete tables/supplements were not recovered. Some other supplements, protocol histories, historical cash/COI statements, private invoices, current beneficial ownership and long-term safety remain unverified. Retrieved text, primary abstracts and declarations were not treated as interchangeable with all original outcome tables or complete financial clearance. No adverse motive is inferred from a missing disclosure.
Last reviewed: 1 October 2026.
Have a question — or want us to cover something?
Ask about anything on this page, or request the next deep dive: an ingredient, a supplement, or a health concern. We use published research, evidence syntheses, and regulatory guidance, with clear source links.
One daily research roundup
Get the topics, key findings and links from our new articles in one email. At most one digest a day, only when there is something new.