
Key takeaways
- Alginate is a family of gel-forming polymers; reflux medicines usually contain a specified alginate salt and other ingredients (Ingredient identities; Medicinal formulation).
- Manufacturer-linked trials report relief of heartburn and regurgitation, but the strict independent-evidence verdict remains insufficient (Selected symptom endpoint; Actual commercial support).
- Add-on treatment results are mixed. Symptom improvement does not establish healing of esophagitis or prevention of complications (Selected positive symptoms; Null confirmatory comparison; Healing is a separate outcome).
- Gaviscon formulations differ across countries, strengths and age groups; the brand name alone does not identify the intervention (UK Advance; UK Double Action; UK Infant; US label).
- Sodium, potassium, calcium, other antacids and medicine-spacing instructions require a product-specific check (Specific mineral and spacing warnings; Different warnings; US antacid label).
- A large Chinese Gaviscon trial was retracted. It must not be retained as reliable positive evidence through a later review (Excluded original; Formal retraction).
Selected alginate products have a plausible physical role in reflux management. The finite studies reviewed here include favorable commercial symptom trials, null comparisons and substantial methodological limits. Formulation matters; evidence for plain alginate, chronic throat symptoms and routine pediatric treatment remains limited. Complete relevant originals were read where accessible; several studies remain limited to abstracts or other primary records. Missing financial terms do not establish independence, and funding concerns do not prove ineffectiveness (Formulation-dependent trial; Null confirmatory result; Revised-margin trial; Gifted infant preparation).
Contents
Evidence summary · What it is · Forms and delivery · How it works · Hype versus evidence · Benefits by claim · What works · Risks · Interactions · Who should avoid · Research regimens · Laboratory evidence · Funding and access · Regulation · FAQs · Sources
Evidence summary
Commercially supported studies are described for context and excluded from the independent benefit verdict, whether their result is positive or null. A study can be well designed and financially interested at the same time. U denotes an unresolved funding or procurement issue, not misconduct.
| Claim | Human evidence | Primary source | Funding or conflict | Verdict after independence screen |
|---|---|---|---|---|
| Relieves heartburn and regurgitation | Positive seven-day combination trial; original abstract read, full Methods/tables unavailable | Wilkinson 2019 | Five Reckitt-affiliated authors; complete finance/supply terms unresolved | Insufficient independent evidence |
| Comparable to omeprazole for episodic heartburn | Short noninferiority trial using French Gaviscon | Pouchain 2012 | Reckitt grant, company authors and paid study/writing support | Excluded |
| Improves symptoms remaining on a PPI | Selected benefit in small trial; larger confirmatory comparison null | Reimer 2016; Registry support; Coyle 2017 | Reckitt sponsorship/support verified for Reimer; Coyle company funding/writing and employees | Mixed commercial results; insufficient independent evidence |
| Plain non-bicarbonate alginate adds benefit | Lamina G plus PPI did not outperform PPI comparison | Kim 2019 | Taejoon support | Excluded; no general proof for powders |
| Treats laryngopharyngeal reflux | Placebo-controlled trial was null; active-comparator trial had important limitations | Tseng 2018; Pizzorni 2022 | TTY Biopharm and DMG Italia, respectively | Insufficient independent evidence |
| Improves infant regurgitation | Selected short-term signals; sequential and unblinded crossover designs | Salvatore 2018; Baldassarre 2020 | First: no study support declared, outside ties and procurement unknown; second: explicit product gift and consultancy | Insufficient for routine or unsupervised use |
| Improves reflux with newer barrier blends | 100 randomized, 96 per-protocol; positive open-label rescue-use result | Spada 2025 | Nekkar product/partial grant; CRO author; Fondazione Roma acknowledged | Excluded; multiple components, interim stopping and reporting limits |
| Heals erosive esophagitis or prevents complications | Symptom studies do not answer these endpoints | Studies discussed below | No independently verified alginate-alone basis established here | Insufficient (Rescue use without repeat endoscopy; Erosive disease management). |
What it is
Alginates are polysaccharides commonly extracted from brown seaweed. Their mannuronic- and guluronic-acid units form chains whose properties vary with source and processing. Alginic acid and its sodium, potassium, ammonium and calcium salts are related materials, with distinct specifications. Magnesium alginate also appears in medicinal formulations. EFSA ingredient assessment
A seaweed food, culinary thickener, sodium-alginate powder, infant feed preparation and licensed reflux medicine are therefore different products. They should not inherit each other’s efficacy, safety or dose. Alginic acid is the acid form; sodium alginate is a salt. The words are sometimes used loosely in summaries, but the actual formulation should decide which research is relevant (Distinct food-additive specifications; Specified medicine; Specific liquid trial).
This article focuses on oral reflux-related uses. It does not establish benefits for alginate wound dressings, dental materials, injectable products, microbiome optimization, IBS or general “gut repair.” A shared polymer is not enough to transfer evidence across routes and indications.
Forms and delivery
| Formulation | What matters | Evidence-transfer limit |
|---|---|---|
| Alginic acid or food-grade alginate salts | Polymer source, viscosity, purity and intended use | Food-use suitability does not establish a therapeutic reflux formulation (Food specifications and assessed uses). |
| Sodium alginate without bicarbonate | Gel behavior differs from gas-generating combinations | Lamina G evidence concerns its specified liquid, not every powder (Lamina G formulation). |
| Alginate with bicarbonate and calcium | Gas generation, gel strength and antacid activity work together | Benefit initially belongs to the combination (Mechanism discussion; Combination composition). |
| Magnesium-alginate blends | May include simethicone, gums or other barrier ingredients | Neither magnesium alginate alone nor sodium alginate can claim the entire result (Gastrotuss blend). |
| Infant sodium/magnesium-alginate preparations | Designed for mixing with feeds or water under precise instructions | Adult liquids and household alginate cannot substitute (Exact infant composition and mixing). |
| Tablets versus liquids | Concentration, coingredients and administration differ | Equal volume or tablet count does not mean equal alginate exposure (Tablet trial; Specified suspension). |
A country and formulation check
These are examples of label composition, not instructions to take them. Company-authored labels are used to identify products and warnings, not as independent proof of efficacy.
| Specific product | Composition example | Source and provenance |
|---|---|---|
| UK Gaviscon Advance Peppermint suspension | Per 10 mL: sodium alginate 1,000 mg and potassium bicarbonate 200 mg; calcium carbonate is also present as an excipient | Reckitt SmPC on emc |
| UK Gaviscon Double Action Mint suspension | Per 10 mL: sodium alginate 500 mg, sodium bicarbonate 213 mg and calcium carbonate 325 mg | Reckitt SmPC on emc |
| UK Gaviscon Infant | Each sachet: sodium alginate 225 mg and magnesium alginate 87.5 mg | Reckitt SmPC on emc |
| US Gaviscon Extra Strength liquid | Active antacids per 5 mL: aluminum hydroxide 254 mg and magnesium carbonate 237.5 mg; sodium alginate is listed as inactive without a quantified dose | Haleon label on DailyMed, updated February 2026 |
“Inactive” is a regulatory label category, not evidence that an ingredient cannot have a physical effect. It also does not establish equivalence to a UK product with a declared alginate dose. The US label includes more than one strength; the row above identifies the Extra Strength liquid specifically (Active/inactive ingredient categories; Different quantified UK product).
The useful comparison is exact formulation, country, dose unit, preparation and clinical setting. A familiar trademark or a larger alginate number alone cannot establish the best product.
How it works
An alginate can form a gel in an acidic environment. In suitable reflux formulations, bicarbonate releases carbon dioxide that becomes trapped in the gel, helping form a floating layer above stomach contents. Calcium can strengthen the structure, while antacid components also change acidity. This is a formulation-dependent physical mechanism; alginate itself is not interchangeable with an acid-suppressing drug. Formulation and mechanism discussion in the primary Lamina G study
That mechanism suggests several different research questions:
- Does a product form the expected gel under specified conditions?
- Does it change measured acid exposure or reflux events after a meal?
- Does it improve troublesome symptoms compared with an appropriate control?
- Does it heal damaged tissue or prevent a complication over time?
Each step needs its own evidence. Seeing a raft or changing a pH tracing does not establish long-term healing. A product can affect acidity without preventing every physical regurgitation event. Non-acid reflux, reflux hypersensitivity and disorders that resemble reflux also complicate interpretation (Diagnostic and healing distinctions; Rescue-use endpoint).
Hype versus evidence
“Forms a barrier” is a mechanism claim. It does not establish cure, permanent repair or protection against every cause of throat symptoms (Non-reflux throat conditions; Limited symptom trial).
“As good as a PPI” needs the actual endpoint and margin. A short noninferiority study of symptom timing cannot establish equal healing, equal long-term control or suitability for a patient who has a different diagnosis (Prespecified symptom-time margin; Changed margin).
A large sample cannot rescue a retracted study. The 1,107-participant Sun trial was retracted in 2018 because of serious protocol and compliance problems. Its results are excluded for reliability as well as commercial support. A review that includes it needs an updated analysis; a pooled estimate does not remove the problem. Original record marked retracted, primary retraction notice
“No funding” can still accompany donated products. Baldassarre's infant study explicitly thanks Aurora Biofarma for gifted preparations and discloses a consultancy. An investigator's control of analysis is relevant, but does not make donated-product research financially independent. Primary disclosures
A clinical practice recommendation and this funding screen answer different questions. Clinicians may consider regulated products using the total evidence and an individual patient's needs. This article asks what remains established after a stricter commercial-exclusion rule. It should not be read as a request to discontinue prescribed treatment.
Benefits by claim
Heartburn and regurgitation in adults Insufficient independent evidence
Wilkinson’s original abstract reports 424 people randomized to Double Action tablets or placebo for seven days. A response meant at least a 1.5-point fall in the combined RDQ heartburn/regurgitation dimension; 47.8% versus 33.2% responded. Five authors had Reckitt affiliations. The figures below are abstract-reported symptom outcomes; full original Methods, numerical tables and financial declarations were not recovered (Original abstract and affiliations).
| Result in the commercially linked trial | Estimate |
|---|---|
| Participants meeting the symptom-score response threshold with product | 47.8% (Original abstract symptom endpoint). |
| Participants meeting the same threshold with placebo | 33.2% (Original abstract symptom endpoint). |
| Odds ratio, with 95% confidence interval | 1.85, 1.23–2.78 (Original abstract symptom endpoint). |
The response threshold was an improvement of at least 1.5 points in the combined questionnaire dimension. It was not complete freedom from reflux, an endoscopic healing endpoint or a long-term prevention outcome. The study is excluded from the independent benefit basis (Original abstract symptom endpoint).
Pouchain recruited 278 people and analyzed 241 per protocol. In the 14-day double-blind, double-dummy trial, the first 24-hour heartburn-free period occurred after a mean 2.0 days in both arms; the difference of 0.01 days (95% CI −0.41 to 0.43) met the prespecified 0.5-day margin. A secondary day-7 measure favored omeprazole. Reckitt funded the grant, study operations and writing. This short symptom-timing result does not establish equal mucosal healing or long-term replacement of PPIs (Full original methods, results and disclosures).
Symptoms despite a PPI Insufficient independent evidence
Reimer randomized 136 people; the official registry analyzed 134 for its primary endpoint. Seven-day HRDQ change and symptomatic nights favored Gaviscon Advance, while several other symptom/satisfaction comparisons were nonsignificant. The registry names Reckitt as sponsor and monetary/material supporter. Coyle’s 262-person confirmatory study reported response of 51% versus 48% (OR 1.15, 95% CI 0.69–1.91), without placebo superiority. Coyle discloses Reckitt funding, writing support and employee authors. Full final journal Methods/tables were not recovered for either; the favorable smaller result should not stand for all PPI breakthrough symptoms (Original abstract; Actual registered results; Sponsor and support; Original confirmatory report).
Differences in formulation and study design prevent treating these as interchangeable experiments. They also make selective quotation of the smaller positive study misleading. Persistent symptoms warrant checking the diagnosis and existing treatment plan rather than assuming that every breakthrough symptom is another episode of acid reflux (Diagnostic and PPI assessment).
Kim randomized 120 people, with 46 and 47 in the main efficacy comparison. Four-week Lamina G plus omeprazole did not improve the primary final-week symptom-resolution outcome over omeprazole plus placebo: 58.7% versus 57.5%, p=0.903. Taejoon supported the study. The small alginate-only reference group was not powered to establish noninferiority. This specified non-bicarbonate liquid does not clear a household powder or every other alginate formulation (Full original methods, tables and funding).
Laryngopharyngeal reflux and throat symptoms Insufficient
Hoarseness, throat clearing and cough are not specific proof of reflux. Symptom and laryngeal appearance scores should not be treated as equivalent to a confirmed reflux mechanism or healed esophageal injury (Extraesophageal diagnostic cautions).
Tseng’s original abstract reports 80 adults enrolled for eight weeks. Both groups improved, but Alginos did not outperform placebo on the reported symptom or impedance measures. The publisher identifies TTY Biopharm funding and a sponsor no-role statement. Full original Methods, numerical tables and supporting data were not recovered, so this remains a partial original-source review (Original abstract and funding record).
Pizzorni planned 128 participants but randomized 50; 40 supplied follow-up outcomes. The DMG-funded Gastrotuss blend was compared with omeprazole plus lifestyle advice. Participants were unblinded and there was no placebo-only group. The original 4-point noninferiority margin failed; the authors widened it to 7 points after under-recruitment. These choices weaken an unqualified equivalence claim, and the mixture cannot establish an isolated magnesium-alginate effect (Full original methods, flow, analysis and funding).
These findings do not establish an independently verified alginate treatment for all chronic throat symptoms. An appropriate trial would confirm the target condition, use a suitable blinded control and retain its prespecified analysis (Null placebo result; Comparator and analysis limits).
Infant regurgitation and pediatric reflux Insufficient independent evidence
Salvatore enrolled 43 infants and obtained 40 usable traces, comparing a baseline day with the next day on hospital-available preparations. Selected reflux-episode and symptom measures improved, but acid exposure time and acid clearance did not. There was no randomized concurrent control for day-to-day change. No study funding/support was declared; outside author commercial ties and hospital product-payment terms remain relevant. This short sequence is preliminary evidence, not proof of routine infant benefit (Full original methods, outcome tables and declarations).
After feeding advice, Baldassarre treated 72 infants: 53 formula-fed in an unblinded randomized crossover and 19 breastfed in an uncontrolled arm. Both crossover treatments improved symptom scores. The between-sequence comparison and cumulative alginate-versus-thickened-formula comparison were nonsignificant; this was not a formal equivalence trial. There was no untreated or placebo comparison. Aurora explicitly gifted preparations and the lead author disclosed consultancy, so the study remains Tier 4 (Full original flow, tables, funding and conflicts).
Current NICE guidance allows a professionally supervised 1–2-week alginate trial in selected infants with persistent regurgitation and marked distress after feeding assessment. For formula-fed infants, review feeding volumes/frequency and try thickening first; stop thickened formula before alginate. Successful short trials should be reassessed with attempts to stop. The 2018 joint guideline weakly advises against chronic antacid/alginate use. These decisions do not supply an infant self-dosing regimen (Current recommendations 1.2.1–1.2.5; Original NICE evidence assessment; Joint recommendation 5.1).
Newer mixed barrier products Insufficient independent evidence
GENYAL randomized 100 people to a mixed barrier product plus omeprazole or omeprazole alone; 96 were described as per-protocol, while the rescue-use table contains 95. The open-label study reported fewer rescue tablets over 28 days. Sample termination followed a favorable interim analysis, and participant-flow counts are internally inconsistent. Later follow-up had no concurrent control and no repeat endoscopic healing assessment was reported. Nekkar supplied products and partial support, Fondazione Roma was acknowledged, and a CRO-employed author participated. This is limited evidence for a multi-ingredient regimen, not isolated alginate or proven healing (Full original methods, tables, limitations and finance).
An August 2026 report describes a large comparison of sucralfate/alginate capsules with omeprazole. Its abstract reports noninferiority for heartburn-free days and more regurgitation-free days with the combination. Complete methods, the noninferiority margin, funding and procurement details were not accessible in this audit. It remains an unresolved combination study and does not establish independent efficacy for alginate alone. Shahbazi 2026 abstract
Endoscopic healing and prevention Insufficient
Heartburn relief, less regurgitation, fewer rescue doses, a different pH tracing and endoscopic healing are separate outcomes. Having mild esophagitis at enrollment does not turn a symptom trial into a healing trial. Likewise, a lower laryngeal finding score does not demonstrate healing of erosions in the esophagus (Rescue outcome without repeat endoscopy; Laryngeal score endpoint).
This audit did not establish independent evidence that isolated alginate heals erosive esophagitis, prevents strictures, reverses Barrett's esophagus or prevents cancer. The ACG guideline treats erosive disease and alarm symptoms as matters requiring appropriate diagnosis and management. Improvement after an over-the-counter preparation does not settle those questions. ACG guideline
What works and what does not
| Proposed use | Verdict | Meaning |
|---|---|---|
| Selected formulated products for short-term adult reflux symptoms | Insufficient independent evidence; positive commercial trials | Plausible clinical option, but the strict eligibility criterion is not met (Abstract-reported tablet response; Specified short trial). |
| Add-on treatment for everyone still symptomatic on a PPI | Mixed overall; insufficient independent evidence | A larger confirmatory study did not outperform placebo (Larger null confirmation; Selected smaller benefits). |
| Plain food-grade sodium alginate as a substitute for a tested medicine | Insufficient | Concentration and formulation are not equivalent (Specific liquid formulation). |
| Laryngopharyngeal reflux | Insufficient | Null placebo trial and weakened noninferiority claim (Null placebo comparison; Revised-margin comparator). |
| Routine infant or chronic pediatric treatment | Insufficient | Limited studies, product-specific risks and professional assessment required (Sequential study; Unblinded crossover; Selected supervised use). |
| Healing or complication prevention inferred from symptom relief | Does not establish the claim | The required clinical endpoint was not demonstrated (Rescue, not repeat endoscopy; Healing and diagnosis). |
| Seaweed consumption as an equivalent reflux treatment | Insufficient | Whole foods and specified medicines are different interventions (Food-material identity; Specified medicine). |
None of the finite benefit claims reviewed here meets this review’s strict commercial-exclusion rule. That does not show that every regulated alginate medicine is ineffective or unsuitable for clinician-selected care.
Risks and side effects
“Acts physically” does not mean that the complete product is free of systemic considerations. Its salts, antacids and other ingredients still matter (Mineral and excipient warnings; Other active antacids).
| Issue | Specific preparation or situation | What the evidence or label says |
|---|---|---|
| Sodium and potassium load | UK Advance Peppermint suspension | Per 10 mL, calculated from its 5 mL label values: sodium 115.7 mg and potassium 78.12 mg. Salt-restricted diets and reduced kidney function need attention; label |
| Sodium, calcium and kidney disease | UK Double Action Mint suspension | Per 10 mL: sodium 127.88 mg; per 20 mL: calcium 260 mg. The label excludes moderate/severe renal insufficiency and cautions about high calcium or recurrent calcium stones; label |
| Calcium in a product whose active ingredients omit it | UK Advance Peppermint | It also contains 200 mg calcium carbonate per 10 mL. Calcium-carbonate mass is not the same as elemental-calcium mass; label |
| Kidney disease or restricted mineral intake | US Gaviscon liquids | The label asks for professional review with kidney disease, sodium or magnesium restriction; a laxative effect may occur; Haleon label |
| Allergy | Individual active ingredients, preservatives or flavorings | A formulation-specific possibility; UK labels include hypersensitivity warnings. Prior reaction warrants avoiding re-exposure (Hypersensitivity/bronchospasm warnings; Formulation-specific allergy warnings). |
| Over-thickening and obstruction | UK Gaviscon Infant | Must not be combined with thickened feeds; obstruction, abdominal distension and bezoar are listed with unknown frequency; infant label |
| Dehydration and sodium disturbance | Infants with relevant illness or renal impairment | Product-specific contraindications are stricter than adult-use assumptions; clinical supervision is essential (Specific infant contraindications). |
| Persistent or changing symptoms | Repeated self-treatment | Relief can delay recognition of a different condition; the appropriate next step is review, not indefinite escalation (Seven-day reassessment; Specific persistent-symptom guidance). |
Safety note: Amounts in this table describe the named products, not an intake target. Actual daily mineral exposure depends on the formulation and quantity used. Trial tolerability over a few days or weeks cannot establish every rare adverse effect or the safety of indefinite use (Short selected safety sample; Actual label risks; Different contraindications).
Interactions
| Medicine or combination | What warrants checking | Scope of the evidence |
|---|---|---|
| Oral medicines with UK Advance | Its label advises considering a two-hour interval, naming drugs such as iron, thyroid hormones, tetracyclines, fluoroquinolones and bisphosphonates | Product-specific SmPC; not a universal alginate-only rule |
| Oral medicines with UK Double Action | Calcium/carbonate antacid components can affect coadministered medicines; its two-hour advice covers several drug classes | Product-specific SmPC; the other medicine may require a longer interval |
| Prescription medicines with US Gaviscon | The aluminum/magnesium antacid formulation requires an interaction check | Haleon label; do not copy UK instructions automatically |
| Infant thickeners or anti-regurgitation formulas | Combined thickening can be excessive | UK Gaviscon Infant specifically prohibits this combination; label |
| Other antacids, calcium, sodium or potassium products | Total ingredient exposure may accumulate | Requires the actual products and clinical context; no universal safe stacking rule was established (Sodium, potassium and calcium cautions; Different calcium/renal cautions). |
| PPIs | Some studied regimens deliberately combine treatments | A combination trial is not a blanket interaction clearance for every formulation or medicine schedule (Selected add-on trial; Different add-on comparison). |
The selected trials reviewed here are not a comprehensive interaction program for every alginate, medicine or supplement. Ask a pharmacist to reconcile the instructions for both actual products. UK labels advise considering two-hour spacing with named medicines; a companion medicine’s longer requirement still needs checking. These are formulation-specific antacid/mineral precautions, not a universal alginate-only interval (Advance interaction instructions; Double Action interaction instructions; US prescription-medicine warning).
Who should avoid self treatment
Food stuck in the oesophagus, inability to swallow liquids or saliva, or excessive salivation needs urgent medical care; complete obstruction may require emergency endoscopy. Vomiting blood, coffee-ground material or black tarry stools needs prompt medical help; shock symptoms require emergency help. New or progressive swallowing difficulty, unexplained weight loss or persistent vomiting also needs prompt assessment rather than prolonged self-treatment. Symptom relief does not settle the cause (Obstruction and urgent endoscopy guidance; Bleeding and shock warnings; Alarm symptoms and investigation).
People with heart failure, kidney impairment or prescribed sodium/potassium restrictions need the specific product checked. The contraindication for moderate/severe renal insufficiency quoted above belongs to UK Double Action Mint; it should not be carelessly restated as an identical rule for every alginate (Salt restrictions and kidney function; Specific renal contraindication).
Infants require a feeding and clinical assessment. The UK infant label excludes intestinal obstruction, established diarrhea, relevant dehydration risk and known/suspected renal impairment, and requires a health-professional recommendation. Premature infants and those under one year need medical supervision. Do not make an infant treatment by diluting an adult medicine or weighing culinary powder. Gaviscon Infant SmPC
For pregnancy or breastfeeding, consult the exact medicine’s local label and a clinician or pharmacist rather than adopting a category-wide ban or reassurance. This audit did not establish safety for every alginate blend, all coingredients or every pregnancy complication (If-needed pregnancy/lactation label; Different formulation label).
Research regimens and clinical instructions
The rows record adult trial regimens, not recommendations. A milliliter amount applies only to the tested preparation; it cannot be converted into a household-powder dose.
| Study and setting | Research regimen | Observation period | Important limit |
|---|---|---|---|
| Pouchain, episodic heartburn | French Gaviscon 10 mL four times daily versus omeprazole 20 mg/day | 14 days | Manufacturer-supported combination; paper |
| Reimer, PPI add-on | Gaviscon Advance 10 mL four times daily | 7 days | Sponsor/support verified in Protocol; Results; full final journal methods unavailable; Abstract |
| Kim, non-bicarbonate preparation | Lamina G 20 mL three times daily, 50 mg/mL, alongside omeprazole in the main comparison | 4 weeks | Maker support; paper |
| Tseng, throat symptoms | Alginos providing sodium alginate 1,000 mg three times daily | 8 weeks | Maker-funded, placebo superiority not shown; paper |
| Pizzorni, LPR | Gastrotuss 20 mL three times daily versus omeprazole 20 mg/day | 2 months | Blend, maker funding and revised margin; paper |
| Pediatric investigations | Product-, weight- and feeding-specific professional regimens | One-day assessment to short treatment periods | No caregiver dosing instruction can be inferred from this summary (Short monitored exposure; Infant research design; Product-specific clinical instructions). |
These sources do not establish a universal optimal alginate dose, duration or long-term safety ceiling. Follow the exact product’s local label and clinician instructions. Where the label calls for reassessment after persistent symptoms, a longer research protocol does not authorize bypassing that instruction (Specific reassessment directions; Different product instructions; Infant clinical supervision).
Animal and in vitro evidence
Bench testing can characterize gel strength, floating behavior or adhesion. Animal and tissue experiments can explore mechanisms. Those findings do not establish symptom benefit, endoscopic healing or long-term safety in humans (Physical mechanisms versus clinical outcomes; Nonhuman toxicology context).
EFSA's food-additive assessment includes animal toxicology and submitted industry data. Such material can inform the regulator's specified safety assessment, but is excluded here from human benefit grades. The assessment also identifies limits for some infant/young-child special-medical-food exposures. “No numerical ADI needed” in that context must not become “unlimited concentrated doses are safe.” EFSA 2017
A study of a protective blend in a laboratory model likewise cannot assign the result to alginate alone. This review does not use animal-only results to fill gaps in the clinical trials (Multiple ingredients and laboratory background).
Reported funding and access limits
Research funding at a glance
24 disclosure entries. The counts below summarize independence tiers explicitly assigned in this article. They count disclosures, not studies, funding amounts or evidence quality.
Consult this article’s source and funding notes for named funders, countries, relationships and exceptions where available. Institutional backing, researcher interests and trial sponsorship are separate questions. Public funding alone does not establish independence; commercial ties alone do not prove a claim false. This overview is not a new financial audit.
How sources were classified
The commercial screen applies to grants, company-employed authors, sponsored operations and donated materials. Buying a commercial product at arm's length is not sponsorship. The word “provided” alone does not prove donation. When purchasing terms are absent, the gap stays visible.
Baldassarre explicitly reports a gift, whereas Salvatore declares no study funding or other support and used preparations already available in hospitals. Those are different stated records. The latter still leaves hospital payment terms and indirect author ties unresolved (Actual product gift and declarations; Actual support and sourcing statement).
A non-interference declaration describes the reported sponsor role. It does not remove the financial relationship. Similarly, a public guideline or independently financed review cannot make its underlying company trials independent (Sponsor/support despite design independence; Guideline and source conflicts).
Makers and their backers
Reckitt is a UK-incorporated listed consumer-products group with Gaviscon in its portfolio. Its 2025 annual report reproduces historical voting-right notices of 5.00% for Massachusetts Financial Services and 4.99% for Morgan Stanley Investment Management Limited. Footnotes say both decreased in early 2026 without new percentages. These are dated financial disclosures, not verified current stakes or proof of control of a trial (Pertinent annual-report portfolio and shareholding sections).
Haleon is a separate UK-listed group with its registered office in England; Haleon US Holdings is named on the US liquid label. The 2025 report gives BlackRock’s 5.22% notification dated 16 January 2025 and says Pfizer sold its remaining stake in March 2025. These are dated disclosures, not current portfolio verification. The US label should not be attributed automatically to Reckitt (Pertinent annual-report identity and shareholder sections; Actual US labeler).
DMG Italia identifies Pomezia, Italy as its base and describes itself as a family-rooted company. Its website records Luigi Mercuri and Antonio De Nisi as founders. That history does not verify their present holdings. DMG funded Pizzorni's Gastrotuss trial. Current ultimate ownership percentages were not established. Company disclosure, trial funding
Other disclosed commercial participants include TTY Biopharm in Taiwan, Taejoon in South Korea, and Aurora Biofarma and Nekkar Lab in Italy. Their study roles are documented in the cited papers; ultimate owners and all upstream investors were not resolved. No ownership relationship between two companies is inferred from their involvement with a similar formulation (TTY funding and Taiwan affiliation; Taejoon support and Korean study; Aurora gift and Italian context; Nekkar support and Italian context).
Revenue from medicines, devices and supplements creates an incentive for favorable positioning. Researchers have publication and career incentives; professional societies and regulators have institutional interests. These incentives warrant scrutiny without proving that a result is false. Company filings and labels can document their own business facts while remaining interested sources.
Documented money map
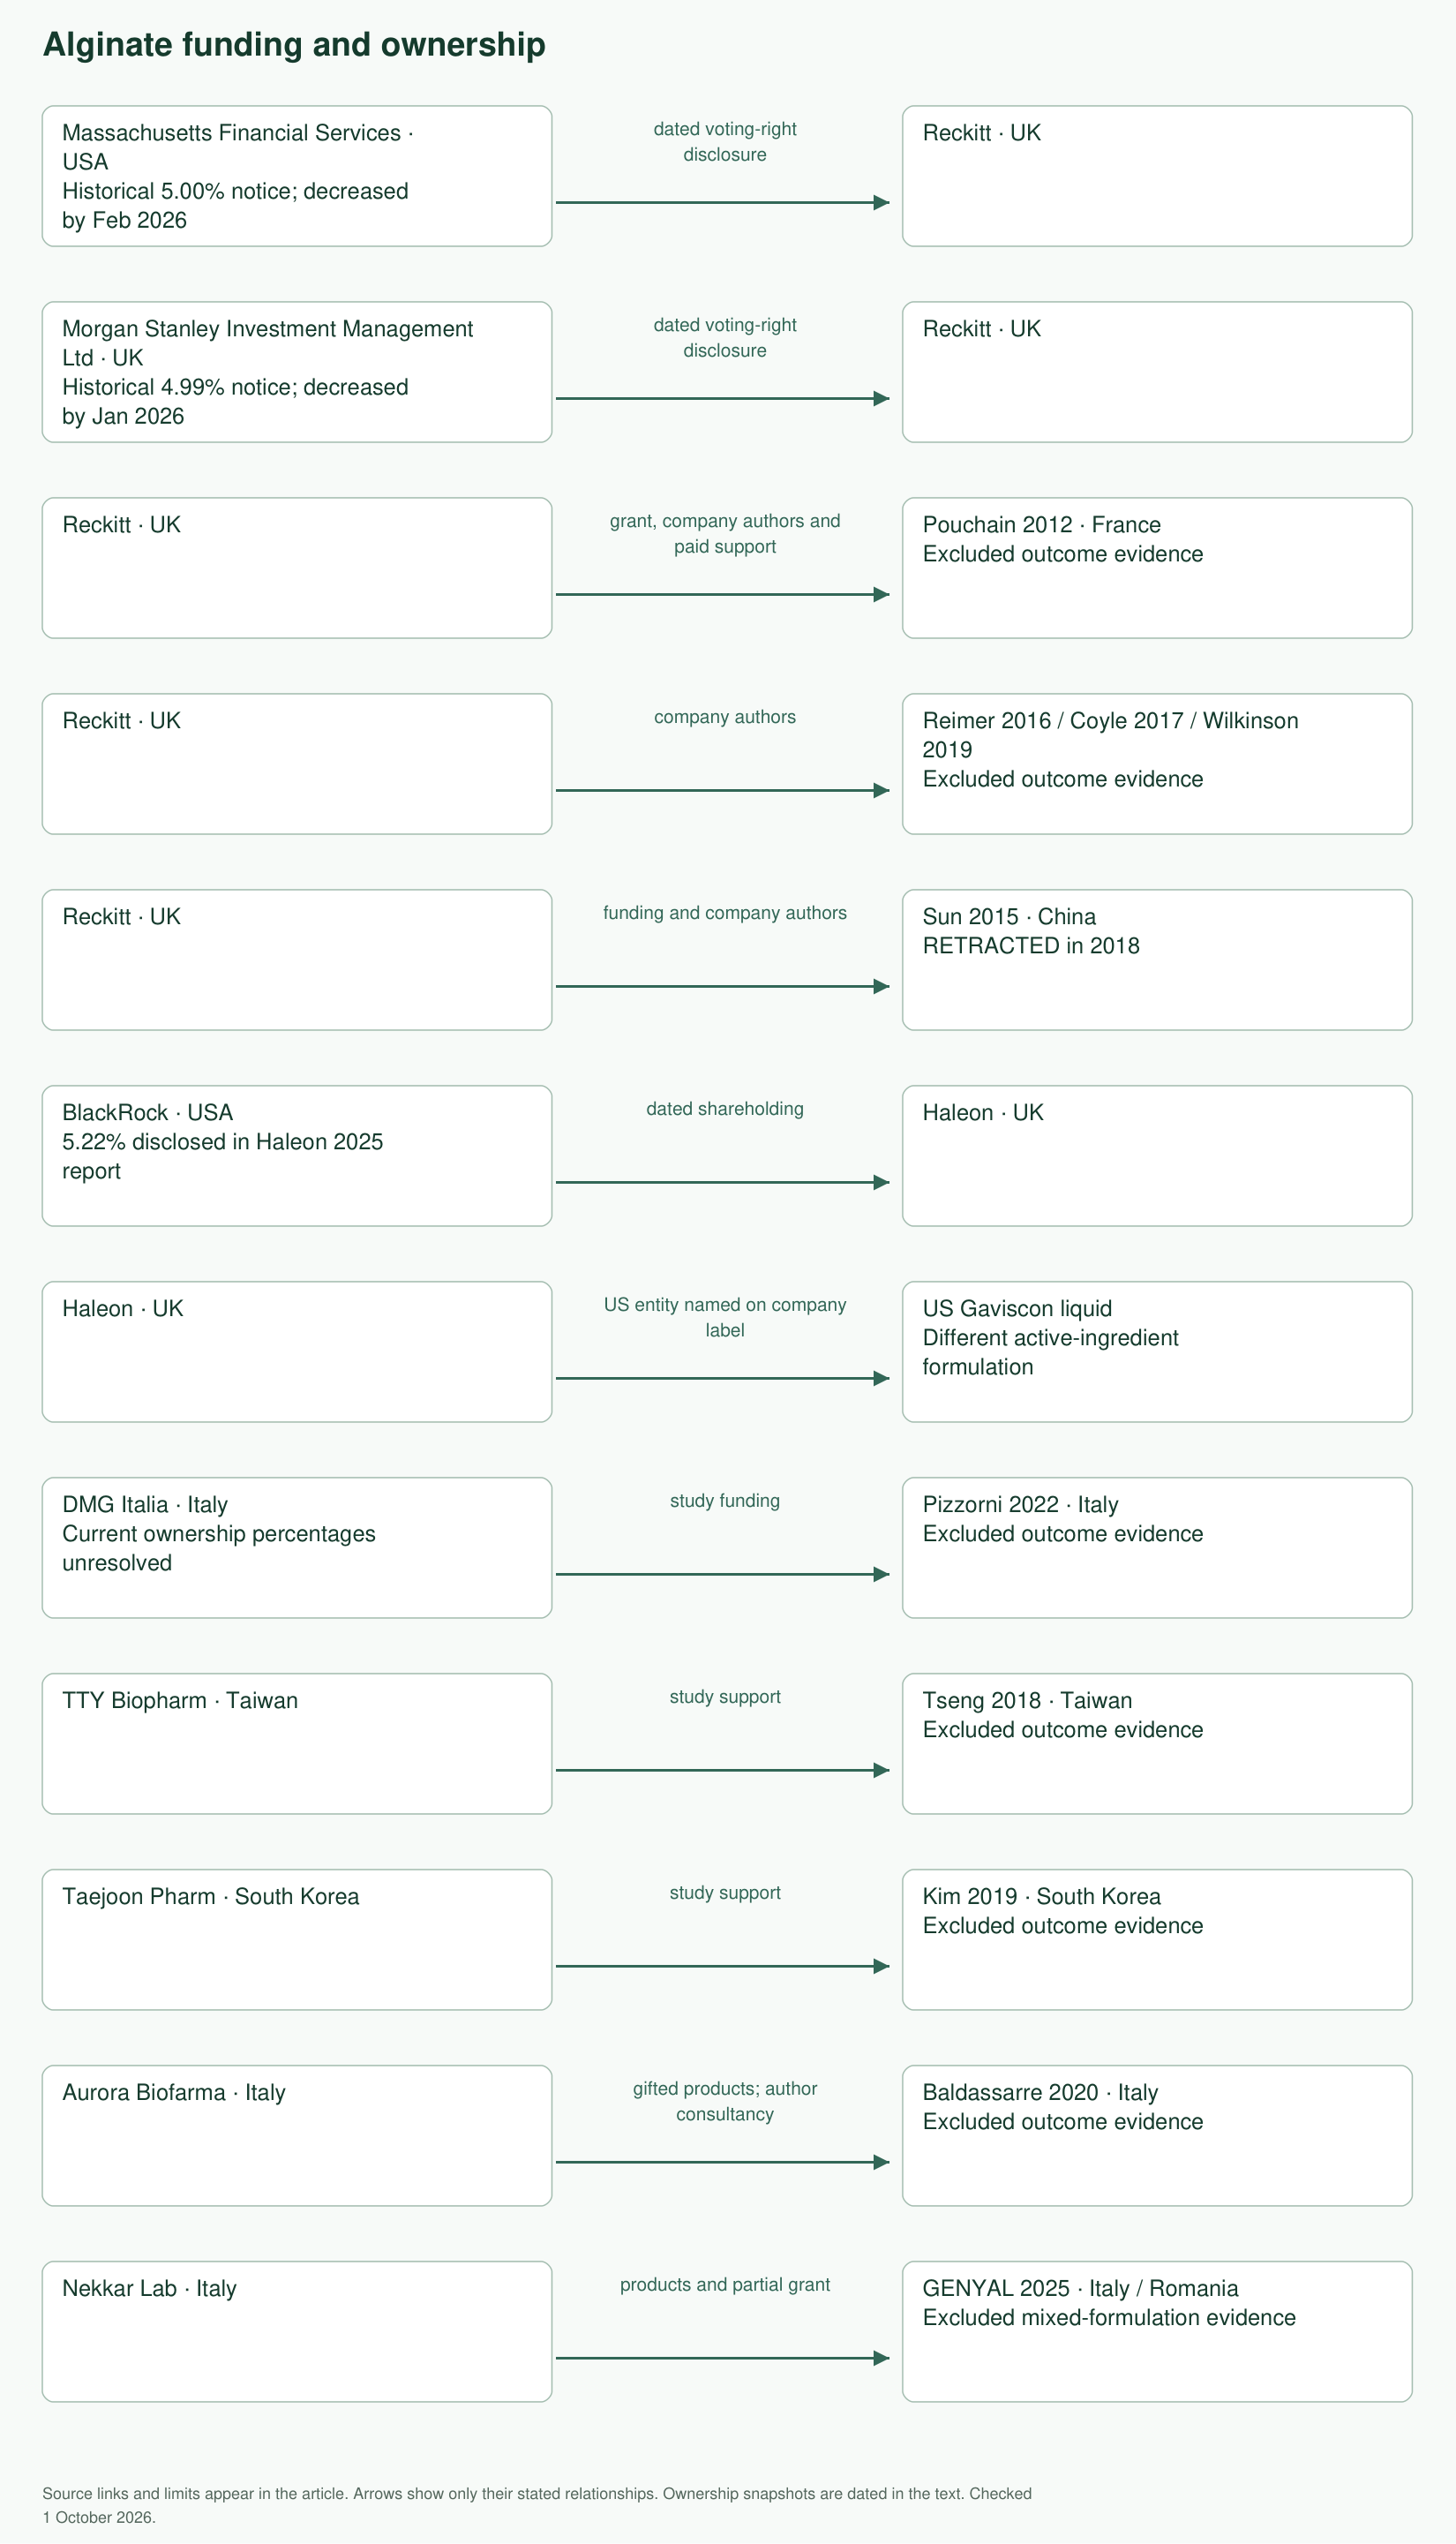
The cited text below records the relationships represented in the figure. Dated shareholdings are not allegations of trial interference; current ownership and private payment chains are not comprehensively verified.
Accessible relationship list:
- Historical MFS and Morgan Stanley voting-right disclosures → Reckitt; both later decreased, with new percentages undisclosed in the cited report (Historical notifications and later decreases) (MFS Boston/US identity; Exact MSIM Limited English registration).
- Reckitt → Pouchain funding and paid support; company authors in Reimer, Coyle and Wilkinson; funding/authorship in the retracted Sun study (Grant and paid support; Reimer sponsor; Coyle funding; Company affiliations; Retracted trial disclosures).
- BlackRock’s dated disclosed holding → Haleon; the US product label names a Haleon entity (Dated interest; Haleon labeler) (BlackRock original SEC cover: Delaware and New York).
- DMG → Pizzorni funding; TTY → Tseng support; Taejoon → Kim support (DMG support; TTY funding; Taejoon support).
- Aurora → gifted preparations and a disclosed consultant relationship in Baldassarre (Explicit gift and consultancy).
- Nekkar → products and partial grant support in GENYAL (Actual support statement).
The studies span several countries, but multiple sites using the same sponsor's products do not necessarily constitute independent replication. Headquarters, legal jurisdiction, algal harvest location, polymer processing and final medicine manufacture are different facts. Lot-specific supply chains were not comprehensively verified.
Regulatory status
United Kingdom
The UK examples above are medicinal products with product-specific SmPCs. Those documents are supplied by Reckitt on emc (Advance SmPC; Double Action SmPC; Infant SmPC).
United States
The US DailyMed page is a Haleon-submitted OTC drug label, identifying the listed products under an OTC monograph. Government hosting does not change a company-authored label into an independent clinical trial (OTC Monograph Drug M001 and labeler).
Medical devices and food additives
Gastrotuss was described in the Pizzorni study as a medical device. This category and the product’s formulation do not establish that every alginate powder is equivalent or that its clinical evidence is independent. Local classifications and permitted uses must be checked for the actual product (Specified device and study).
EFSA's assessment concerns alginic acid and specified salts as food additives under defined exposures. It is not an authorization of alginate as a universal GERD treatment. The assessment includes submissions from Marinalg International, Mars Chocolate UK, food-industry associations and other businesses; those inputs retain their commercial provenance. EFSA report
Approval or lawful sale, a permitted label indication, and this review's independent benefit verdict are separate judgments.
FAQs
Is alginate an antacid?
The polymer is a gel-forming ingredient. Many reflux products combine it with antacids, so the finished formulation can have both physical and acid-neutralizing actions (Formulation mechanism; Active combination).
Is sodium alginate the same as alginic acid?
They are related acid and salt forms, not interchangeable label terms. The actual formulation determines solubility, processing and how the ingredient is used (Specified acid and salt identities).
Is every Gaviscon product the same?
No. The examples above differ substantially by country and product line. Check the full active-ingredient list and concentration rather than relying on the name (UK Advance; UK Double Action; US active ingredients).
Can I replace a reflux medicine with seaweed or food-grade alginate?
The reviewed evidence does not establish that substitution. A food or culinary powder has not thereby become the formulation tested in a reflux trial (Specific tested preparation).
Does symptom relief mean my esophagus has healed?
No. That requires a different endpoint and sometimes investigation. Relief does not rule out an important underlying condition (Healing and alarm diagnosis; Different symptom/rescue endpoint).
Does noninferiority mean two treatments are identical?
No. It depends on a predefined acceptable difference, adequate power and the population and endpoint tested. Changing the margin after recruitment problems weakens the conclusion (Prespecified margin; Post hoc revised margin).
Can a baby take a diluted adult formulation?
Do not improvise that substitution. Infant preparations, mixing instructions, feeding combinations and contraindications require professional assessment (Specific infant instructions/contraindications).
Can alginate safely be taken with all medicines?
That has not been established. The complete product matters, and a companion medicine may require more separation than the reflux product’s general advice (Specific drug-spacing advice; Different antacid warnings; Medicine review).
Does industry funding mean the results should be ignored?
No. Positive and null findings are reported here with their limitations. They are excluded from the independent verdict because that is the review’s stated standard. Retraction is a separate, stronger reason not to rely on a result (Commercial positive comparison; Commercial null comparison; Separate retraction).
Sources and funding notes
Tier 1 means no identifiable relevant financial stake in the declarations and finite checks available here; Tier 2 indirect ties; Tier 3 interested professional relationships; Tier 4 maker/seller support or affiliation; U unresolved terms. These provisional editorial classifications do not clear every payment, individual interest or ultimate donor. A–D grades describe accountability/provenance for the stated use, rather than certainty of clinical benefit. An inaccessible disclosure or no-conflict statement is not proof of financial independence.
Company materials are graded Tier 4/C for limited factual use here. Their regulatory obligations make labels useful for composition and warnings, but do not turn them into independent efficacy evidence.
| Source | Funding, ownership or revenue | Country / jurisdiction | Tier; grade | Accuracy incentive and residual limitation |
|---|---|---|---|---|
| Wilkinson 2019 | Five Reckitt-affiliated authors; complete project/supply and COI terms unrecovered | UK author affiliations | 4; C | Complete original abstract/affiliations read; final full Methods/tables unavailable; seven-day symptom endpoint |
| Pouchain 2012 | Reckitt grant, paid research operations/writing and company authors | France / UK | 4; C | Detailed methods and disclosure; short noninferiority endpoint (Full relevant methods/results/finance). |
| Reimer 2016; Protocol; Registered results | Reckitt commercial sponsor and monetary/material support; employee coauthors | Denmark / UK affiliations | 4; C | Original abstracts plus actual protocol/results read; full final journal Methods/tables/COI unavailable |
| Coyle 2017; Published erratum | Reckitt commissioned/funded study and Cello writing; company authors | UK / Denmark affiliations | 4; C | Original abstract/front funding and full erratum read; full main Methods/tables unavailable; confirmatory comparison null |
| Kim 2019 | Taejoon study support despite no-conflict declaration | South Korea | 4; C | Detailed controlled trial; sponsor interest and non-bicarbonate-specific result (Full relevant main and declarations). |
| Tseng 2018 | TTY Biopharm funded; no-role and no other interests declared in publisher record | Taiwan | 4; C | Original complete abstract/front declarations read; full main tables/Methods unavailable; placebo superiority not shown |
| Pizzorni 2022 | DMG Italia funding | Italy; Belgian collaboration | 4; C | Transparent revised margin; under-recruitment, unblinded participants and blend (Full relevant main and declarations). |
| Salvatore 2018 | No study funding/support declared; outside nutrition/pharma ties; hospital-payment terms unknown | Italy / Belgium | 2; B provisional; procurement U | Full relevant main/tables/declarations read; sequential design; acid-time and clearance null |
| Baldassarre 2020 | Aurora-gifted products; lead-author consultancy | Italy | 4; C | Material support disclosed; unblinded crossover and no placebo (Full relevant main/table/funding). |
| Spada 2025 GENYAL | Nekkar products/partial grant; CRO-employed author; Fondazione Roma acknowledged | Italy / Romania; Italian sponsor | 4; C | Full relevant main/tables/declarations read; open label, adapted sample termination, inconsistent flow; no repeat healing endpoint |
| Shahbazi 2026 | Complete funding, supplier terms and final methods unresolved | Study country unverified; publisher Switzerland | U; B provisional | Original complete indexed/publisher abstracts read; full paper pay-per-view/inaccessible; mixed sucralfate regimen |
| Sun 2015 | Fully Reckitt-funded; company authors and paid writing | China / UK sponsor | 4; D for outcomes | Retracted; used only to identify the excluded record (Original identity and finance; Formal status). |
| 2018 retraction notice | Journal/publisher correction agreed with authors; Wiley commercial publishing revenue | UK journal / international publisher | 2; A for status notice | Formal correction accountability; no efficacy role |
| UK Advance SmPC | Reckitt company-authored medicine information on emc | UK | 4; C | Product-information obligations; applies to named formulation only |
| UK Double Action SmPC | Reckitt company-authored medicine information on emc | UK | 4; C | Precise label warnings; not a trial or universal alginate instruction |
| UK Infant SmPC | Reckitt company-authored medicine information on emc | UK | 4; C | Product-specific contraindications; does not supply independent pediatric benefit proof |
| US Gaviscon DailyMed label | Haleon US Holdings company submission, government-hosted | USA; parent UK | 4; C | Label accountability; distinct OTC active ingredients and unquantified inactive alginate |
| EFSA 2017 | EU public assessment; includes industry-submitted specifications, use and safety data | Italy / European Union | 2 for mixed input base; A for regulatory scope | Public methods; underlying commercial and animal data remain contextual (Specified assessment and submitted commercial data). |
| NICE NG1 original; Current recommendations | NICE commissioning/support; individual committee Appendix D not inspected | UK | U for individual finances; B for guidance | Relevant original methods/evidence chapter and current exact step-care recommendations read; supporting-trial finance not globally cleared |
| NASPGHAN/ESPGHAN 2018 | Society financing and NIH author support; A. Staiano disclosed investigator/advisory/consulting/speaker roles with D.M.G. Italy and other companies | USA / Europe | 3; C | Joint methods and disclosure; recommendations do not erase source conflicts (Actual society support and complete COI). |
| ACG 2022 | Full declared author pharma/device consultancy/research ties read; separate guideline cash budget not identified | USA | 2; B for clinical guidance | Relevant main diagnosis, healing/formulation sections and complete individual COI read; finite alarm/diagnostic role |
| Reckitt 2025 annual report | Consumer-product sales and shareholder capital | UK | 4; C | Financial-reporting obligations; historical notices are not live holdings (Finite dated portfolio/holder sections). |
| Haleon 2025 annual report | Consumer-health sales and shareholder capital | UK | 4; C | Listed-company reporting; dated interests only (Finite dated office/holder sections). |
| DMG corporate disclosure | Medicine/device/supplement sales; family-rooted company account | Italy | 4; C | Identifiable business/history; founders do not establish current beneficial ownership (Actual corporate history/identity). |
This is a focused critical review of the sources cited here through 1 October 2026, rather than an exhaustive registered systematic review. Relevant original main Methods, results/tables and declarations were personally read where accessible. Wilkinson and Shahbazi remain abstract-only; Reimer additionally has actual protocol/results, Coyle has original funding and erratum, and Tseng has original funding/COI records. Those partial records do not certify inaccessible complete journal Methods/tables. No retracted outcome supplies benefit or safety evidence.
Unresolved items include full journal papers for several studies, individual or unreported disclosures, separate supplements/protocol histories, hospital and other product-payment terms, grant amounts, current ultimate ownership and lot-specific ingredient supply chains. Retrieved text, abstracts, reported declarations and complete original outcome sections were not treated as interchangeable. Unknowns do not establish independence, donation or misconduct. Stronger confirmation requires reliable preparation-specific clinical outcomes with transparent funding and sourcing.
Last reviewed: 1 October 2026
Have a question — or want us to cover something?
Ask about anything on this page, or request the next deep dive: an ingredient, a supplement, or a health concern. We use published research, evidence syntheses, and regulatory guidance, with clear source links.
One daily research roundup
Get the topics, key findings and links from our new articles in one email. At most one digest a day, only when there is something new.