
Key takeaways
- The sleep findings reviewed here are inconsistent. They do not establish a dependable, clinically important benefit for a generic valerian product (Original sleep trial; Review methods and results).
- Newer positive research includes a manufacturer-funded proprietary extract trial; it is not proof that every valerian capsule works (Original proprietary-extract trial).
- Root powder, tea, water extracts, alcohol extracts, valepotriates and valerian–hops combinations are different interventions (Preparation and route assessment).
- The 2017 US sleep guideline makes a weak recommendation against valerian for chronic adult insomnia. European herbal-medicine rules recognize specified preparations and indications, including traditional use; these assessments are not interchangeable (2017 recommendation; Adopted EU monograph).
- Digestive and potentially sedating effects are reported. Liver injury is a rare regulatory signal, without a reliable population incidence here; long-term and pregnancy safety remain uncertain (Official safety summary; Liver-warning decision).
- Australia’s later decision required liver-risk labels for oral valerian ingredients, with transition ending 1 March 2024. The no-warning statement in its 2020 alert is historical (Dated alert; Final decision).
Evidence verdict: Insufficient for a dependable sleep or anxiety benefit in the evidence reviewed here. Positive and negative results concern different preparations and selected populations. Confidence is moderate that this evidence does not justify valerian as a dependable chronic-insomnia therapy, and low in a precise general benefit estimate or retail-product ranking. Funding and product support are assessed separately from methodological limitations. Original sleep trial; Review; 2017 guideline.
Valerian is not an empty research topic: it has controlled human studies, regulatory assessments and meaningful safety information. The problem is that “valerian” covers preparations with different chemistry, and the more appealing findings are not automatically the more independent or generalizable findings. This review keeps those distinctions visible rather than treating all trials as votes for or against a single standardized product.
Contents
Evidence summary · What it is · Forms · Mechanism · Hype · Benefits · Verdicts · Risks · Interactions · Who should avoid · Studied doses · Laboratory evidence · Funding · Regulation · FAQs · Sources
Evidence summary
Maker-funded outcomes and donated-product trials are shown as context, not used to establish the independent benefit verdict. A study with public grant support can also contain commercial support. Where the paper says “supplied” without payment terms, this review leaves procurement unknown rather than silently converting it into either a gift or a purchase.
| Claim or setting | Key result and limit | Funding and product trace | Independent grade |
|---|---|---|---|
| Short-term adult insomnia | Oxman 2007, 434 randomized; 405 analyzed: primary sleep-quality response difference did not reach statistical significance; some secondary findings favored valerian | Norwegian public research center; manufacturer prepared/blinded tablets, financial terms unclear | Insufficient dependable benefit |
| Insomnia in older women | Taibi 2009, sixteen women: no superiority across subjective, PSG and actigraphy outcomes | NIH grants; Pharmavite explicitly donated softgels | Commercial in-kind support; not independent efficacy basis |
| Cancer-treatment sleep problems | Barton 2011: main endpoint negative; 227 randomized, only 119 evaluable for it | US public grants; Hi-Health supplied study products, transfer terms unresolved | No established benefit in this setting |
| Proprietary standardized extract | Chandra Shekhar 2024: 80 randomized, 72 analyzed; favorable eight-week subjective/objective findings, with PSG in 20 per group | OmniActive funded study and publication fee; selected adults aged 18–50 without comorbidities | Tier 4 context; per-protocol analysis and no stated multiplicity correction |
| Generalized anxiety | Andreatini 2002, 36 outpatients: main between-group anxiety comparison negative | BYK commercial support/product supply plus Brazilian fellowships | Insufficient; specialized valepotriates, not generic tea |
| Chronic adult insomnia treatment | AASM 2017 weak recommendation against use | Society-funded guideline; several authors disclose medicine-industry relationships | Guidance context, not independent trial replication |
| Mild nervous tension or sleep aid under EU herbal rules | EMA assessment distinguishes specific extract evidence from traditional use | EU regulator, fee/public funding; underlying studies have mixed provenance | Preparation-specific regulatory status, not class-wide retail efficacy (Specific preparation assessment; 2026 agency revenue). |
What valerian is
This article focuses on Valeriana officinalis root and rhizome preparations taken orally. The species is native to Europe and Asia and is grown elsewhere. “Valerian” is sometimes used loosely for other species, which should not inherit the evidence for V. officinalis. NCCIH overview
The active material is chemically complex. Root weight, extract weight, extraction solvent, drug-to-extract ratio and measured constituents answer different questions. A label stating 500 mg can mean plant material or an extract, with very different exposure. Botanical identity and preparation therefore belong beside every clinical claim, not in fine print (Preparation categories).
Forms and grades
| Preparation | What matters | Evidence boundary |
|---|---|---|
| Dried root or rhizome powder | Species, plant part, amount and batch composition | Not automatically equivalent to a concentrated extract (Root preparations). |
| Tea or infusion | Plant quantity, water volume and preparation | Traditional use cannot supply an exact equivalence to capsule trials (Tea category). |
| Water extract | Extraction changes which constituents are concentrated | Evaluate the exact extract, not simply the plant name (Water extracts). |
| Ethanolic dry extract | Extract ratio and solvent range affect identity | EMA’s well-established-use assessment applies to specified preparations, not every supplement (Specified dry extract). |
| Tincture or liquid extract | Ratio and residual alcohol | Alcohol content may create additional practical concerns (Tincture categories and ethanol labeling). |
| High-valerenic-acid proprietary preparation | Standardization marker and formulation | Marker content is not proof of superiority without direct comparison (Formulated intervention). |
| Valepotriate preparation | Another constituent profile, sometimes another species | Do not transfer a psychiatric pilot to common root capsules (Valepotriate pilot). |
| Valerian with hops, lemon balm, passionflower or California poppy | Multiple active ingredients | A combination trial cannot isolate valerian’s contribution (Combination-trial review). |
| Essential oil or aromatherapy product | Different concentration and route | Never assume it is a substitute for an oral medicinal preparation (Essential-oil and route assessment). |
The EMA technical report treats preparations separately. Its specified well-established-use dry extract has a drug-to-extract ratio of 3–7.4:1 and ethanol 40–70% as extraction solvent. Those details define a regulatory evidence category; they do not make all products sharing one number interchangeable.
Sleeproot illustrates the importance of formulation: the tested 200 mg powder contained 26.23% hydroalcoholic root extract, 73.27% cellulose polymer and 0.5% colloidal silica, standardized to 2% total valerenic acid. Its findings belong to that formulation and selected mild-symptom population, with OmniActive sponsorship. They do not establish superiority to ordinary root powder or other extracts. Original materials and trial.
How it might work
Laboratory work explores GABA-related signaling, adenosine pathways and several constituents rather than one proven universal “active ingredient.” The Shinjyo review maps this pharmacology and the differences between extracts. Its hypothesis that chemistry and stability help explain inconsistent results is plausible, but it is not a randomized demonstration that a particular retail formulation is better.
Binding in a laboratory assay does not establish how much reaches the relevant human tissue, whether the exposure lasts, or whether someone feels or functions better. Valerian is therefore not appropriately described as a plant equivalent of a benzodiazepine. Similar pathways do not establish equivalent effectiveness, withdrawal behavior or safety.
Hype versus evidence
The popular claims usually collapse three separate questions: can an extract affect a nervous-system pathway, can a person feel sleepier, and can it treat persistent insomnia? The first does not establish the second, and neither establishes the third.
A favorable comparison with baseline is also not enough. People often improve in both active and placebo groups through symptom fluctuation, expectation, study contact and changed routines. The useful treatment estimate is the difference between randomized groups, with its uncertainty. Subscale or secondary improvements cannot erase a failed main endpoint (Primary versus exploratory results; Between- versus within-group anxiety analysis; Primary versus secondary cancer results).
Statements such as “works like a sleeping pill without the risks,” “non-addictive for everyone,” “safe because it is natural,” or “higher valerenic acid means better sleep” go beyond the evidence reviewed. Likewise, counting everyone in a broad review as if they all participated in high-quality trials of the same product exaggerates what the number means (Heterogeneous review and mechanism limits; Long-term safety limits).
Benefits by claim
Adult sleep quality — Insufficient independent evidence
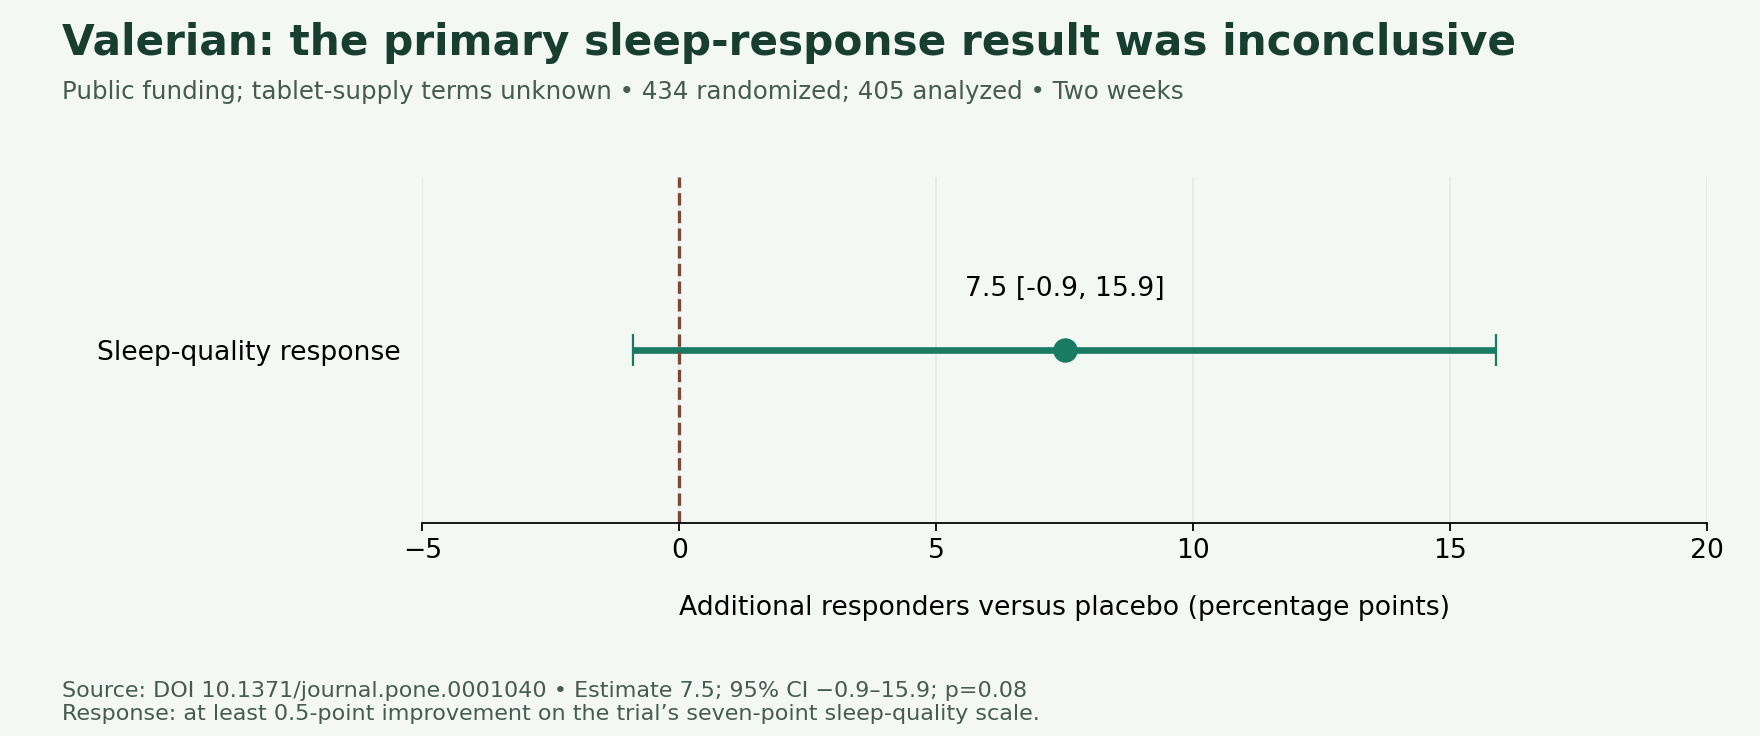
Oxman’s web-based trial randomized 434 adults and analyzed 405 who started treatment for two weeks. Its prespecified primary response was at least a 0.5-point improvement on a seven-point self-rating; the authors assumed this was important rather than validating a sleep-specific threshold. Response was 28.7% versus 21.2%, a 7.5-percentage-point difference (95% CI −0.9 to 15.9; p=0.08). Some exploratory findings favored valerian without multiplicity adjustment. Public funding was reported, with manufacturer preparation of tablets and unspecified payment terms. Oxman 2007.
Public funding and an unresolved product transaction are separate facts, not evidence of misconduct. The short self-report trial constrains dramatic marketing claims but does not establish that every preparation fails or that longer treatment necessarily works. Original design and disclosures.
Older adults — Insufficient
Taibi’s crossover trial of 16 generally healthy women aged 55–80 found no significant valerian–placebo differences in subjective, PSG or actigraphy outcomes. A within-baseline increase in PSG wake time did not establish worsening versus placebo. The front matter says no industry support or financial conflict, while the acknowledgments explicitly record Pharmavite’s donated softgels and NIH grants. Original methods, tables and declarations.
This is not an accusation of misconduct. It is a classification decision: a donated intervention is a material commercial input under this review's rules. The small sample also cannot settle uncommon harms, falls or complicated medication regimens. A null small trial and a guarantee of no possible benefit are different claims.
Sleep during cancer treatment — Insufficient
The cancer-treatment trial randomized 227 people, but only 119 were evaluable for the primary PSQI endpoint, which did not differ significantly (p=0.696). FOSQ outcomes were also negative; exploratory fatigue and change-score findings favored treatment. Selected eligibility, extensive missing data and multiple secondary comparisons limit generalization. Public grants and Hi-Health product supply were reported, but purchase or donation terms were not. Original accepted manuscript.
These findings do not justify recommending valerian throughout cancer treatment. Causes of sleeplessness and medicine interactions need individual assessment. They also do not establish that valerian is categorically incompatible with every anticancer treatment; that would require a separate interaction claim with supporting evidence.
The newer positive extract trial — Commercial context
The Indian trial randomized 80 adults aged 18–50 with mild insomnia symptoms and no comorbidities; 72 completers entered the per-protocol efficacy analysis. At day 56, PSQI changed by −2.05 points with the formulated extract versus −0.09 with placebo. Actigraphy favored treatment; the main text also reports benefits in a PSG subset of 20 per arm, but the retrieved supplement omits the promised complete PSG table. Multiple endpoints and visits were analyzed with simple t-tests without a stated multiplicity adjustment. OmniActive paid for the study and publication fee, despite the authors’ no-competing-interests declaration. Original study.
A sponsor can fund a well-conducted trial, and a sponsored result can be true. It still needs independent confirmation before carrying this article's verdict. Differences from older findings could reflect formulation, population, methods, chance or reporting; the available evidence does not allow one explanation to be declared proven. A positive proprietary trial is not a license to recommend untested valerian powder.
Stress, anxiety and depression — Insufficient
The four-week GAD pilot randomized 36 outpatients to flexible-dose valepotriates, diazepam or placebo. Its primary between-group HAMA comparison was negative; within-group psychic-symptom improvement is not superiority to placebo. Valepotriates averaged 81.3 mg/day, and the small trial also failed to separate diazepam from placebo. BYK partially funded the study and supplied drugs; CAPES/FAPESP fellowships were disclosed. This constituent mixture cannot be equated with ordinary root capsules or tea. Original pilot.
Mild nervous tension in a herbal indication is different from diagnosed anxiety or major depression. The reviewed clinical sources do not establish valerian as a treatment for those disorders or a replacement for prescribed care (Defined indication; GAD pilot; Evidence summary).
Why reviews and regulators can sound different
The 2020 Shinjyo review included 60 diverse studies and selected the most effective dose when several were tested. Its 10-study sleep meta-analysis had a pooled effect of 0.36 (95% CI −0.08 to 0.81) and substantial heterogeneity (I² 85.33%). Its favorable root subgroup is not a direct root-versus-extract comparison, and some narrative positives concern failed primary outcomes. The full review declares no funding or conflicts; Heartwood affiliation indicates a professional herbal-education interest, not proof of manufacturer payment. Original review; Heartwood fees.
AASM’s 2017 recommendation is weak and concerns chronic adult sleep-onset or sleep-maintenance insomnia, using limited valerian and valerian–hops trials. It is not proof of zero effect for every preparation. The adopted EU monograph applies a separate preparation-specific medicinal framework, with well-established and traditional-use categories. Recommendation and Appendix S24; EU monograph.
What works and what has not been established
| Question | Verdict | Important qualification |
|---|---|---|
| Is there a human research signal? | Yes, but inconsistent | Positive proprietary studies coexist with negative controlled trials (Original negative primary result; Positive proprietary trial). |
| Is a reliable independent sleep benefit established? | No | Funding/procurement and replication gaps remain (Trial and procurement limits; Donated-product trial). |
| Is it first-line chronic-insomnia treatment? | No | CBT-I is established first-line care; valerian is not a replacement (CBT-I first-line guidance; Valerian recommendation). |
| Is generic valerian equivalent to a tested extract? | Not established | Chemistry and complete formulation matter (Preparation definitions; Formulated extract). |
| Is there sufficient anxiety/depression evidence? | No | Mild stress, anxiety diagnoses and depression are different claims (GAD pilot; Anxiety/depression summary). |
| Is long-term use risk-free? | No such conclusion is supported | Rare reactions and poorly studied populations remain important (Long-term uncertainty; Liver-risk decision). |
For persistent insomnia, NHLBI guidance places cognitive behavioral therapy for insomnia first. There is no need to frame a supplement as a choice between doing nothing and taking a drug; assessment and behavioral treatment are part of evidence-based care.
Risks and side effects
| Risk | Evidence and uncertainty | What readers should understand |
|---|---|---|
| Sleepiness, mental dullness or dizziness | Recognized concerns with potentially sedating preparations | Do not drive or operate machinery if impaired (Driving precaution; Reported symptoms). |
| Headache, stomach upset, vivid dreams or paradoxical restlessness | Reported adverse effects; reliable rates vary by preparation | A product promoted for calm can still cause unwanted symptoms (Reported adverse effects; GI frequency unknown). |
| Liver injury | Rare but clinically important regulatory signal | Stop the product and seek medical advice for jaundice, dark urine or unusual fatigue, nausea, abdominal pain or itching (Exact liver warning). |
| Abrupt cessation after chronic/heavy use | Withdrawal-like symptoms have been reported | Frequency and risk at ordinary doses are uncertain; discuss sustained use with a clinician (Chronic-use withdrawal reports). |
| Pregnancy, breastfeeding, younger children | Adequate safety evidence not established | No routine self-treatment recommendation follows (Specified age and pregnancy restrictions). |
| Product variation or mixtures | Botanical identification, extraction and other ingredients matter | A favorable safety study cannot cover every retail formulation (Preparation and safety limits). |
NCCIH summarizes short-term tolerability and the limits on long-term use. Absence of serious events in a short trial cannot exclude rare injury: studies designed for sleep outcomes are usually too small and short for that task.
Liver safety: do not use the obsolete label statement
Australia's 2020 alert describes reports involving both mixtures and valerian-only products. Its statement that no label warning was required was true of that dated notice, not a safe summary of later regulation. The final decision required a rare-liver-harm warning for oral valerian ingredients; the transition ended in March 2024.
The warning does not mean most users develop liver injury. Case reports also do not provide a trustworthy incidence denominator. However, uncertainty about the exact frequency is not a reason to dismiss a regulatory signal. Rechallenge after a suspected liver reaction is not an appropriate home experiment.
Interactions
| Exposure | What is known | Boundary |
|---|---|---|
| Alcohol or potentially sedating medicines | NCCIH advises against alcohol/sedative combinations because an additional sleep-inducing effect is possible, although not proven | Review exact medicines with a clinician or pharmacist; the size of any interaction is not established Safety guidance |
| Other calming or sleep supplements | Mixtures can add active ingredients and uncertainty | Do not assume a “natural stack” has been tested (Medicines and supplement precautions). |
| CYP2D6- or CYP3A4-metabolized medicines | A small open before-and-after probe study found a modest alprazolam peak increase and no significant changes in other main measures | Valerian was taken at night and probes next morning; not simultaneous-sedation or every-drug safety Original study record |
| Anesthesia or planned procedures | The product and potentially sedating combinations need professional review | Tell the care team about all supplements and follow its instructions; these sources establish no universal stop interval Provider and medicine precautions |
| Medicines or herbs associated with liver injury | Combined risk is not reliably quantified | Review the complete regimen, especially after a previous liver reaction (Liver injury assessment and precautions). |
Donovan’s open, fixed-order study tested 12 healthy volunteers before and after 1,000 mg/day extract for 14 days. Valerian was taken at night; alprazolam and dextromethorphan were given the next morning. Alprazolam peak concentration rose from 25 to 31 ng/ml, while the reported paired tests for other main measures were nonsignificant. The table and narrative use differing statistical summaries, so precise interaction claims warrant caution. NIH support and Schwabe’s donated extract were disclosed; no separate comprehensive conflict statement was located. This does not test simultaneous additive sleepiness or all medicines and patients. Original trial record.
Laboratory enzyme inhibition should not be converted into a clinically established drug interaction. Equally, a small reassuring pharmacokinetic experiment cannot exclude additive sleepiness, which is a different kind of interaction. The EMA assessment discusses that distinction.
Who should avoid self-treatment
- People with a previous suspected valerian-related liver reaction should not restart it on their own (Rechallenge warning).
- People with liver disease or unexplained abnormal liver tests need professional review before considering it (Vulnerable liver populations).
- Pregnant or breastfeeding people and children should not infer safety from adult trials (Age/pregnancy restrictions).
- Anyone taking sedating medicines or preparing for anesthesia should have the complete product reviewed (Medicines/provider precautions).
- People with persistent sleep difficulty should seek assessment rather than rely on a supplement; CBT-I is usually first-line treatment for long-term insomnia (Insomnia care guidance).
- Anyone who feels impaired should not drive; severe confusion, breathing difficulty or collapse requires urgent help (Driving precaution; Emergency symptoms).
Some of these are precautionary boundaries because research is inadequate, rather than proven contraindications in every situation. Not all sleep problems respond to a sedating substance, and suppressing symptoms is not the same as treating their cause.
Studied doses, not a dosing recommendation
| Study | Preparation and amount | Duration | Why it cannot be generalized |
|---|---|---|---|
| Oxman 2007 | Three 200 mg extract tablets nightly, about one hour before bed | Two weeks | Extract amount and root equivalent are different units (Original dose). |
| Taibi 2009 | 300 mg standardized root extract, 30 minutes before bed | Single-dose and two-week assessments | Older-women sample; donated commercial preparation (Original dose and duration). |
| Barton 2011 | 450 mg ground root, one hour before bed | Eight weeks | Cancer-treatment population, incomplete primary-endpoint data (Original intervention). |
| Chandra Shekhar 2024 | 200 mg formulated standardized extract, one hour before bed | Fifty-six days | Proprietary composition and manufacturer-funded research (Original formulated dose). |
| Andreatini 2002 | Flexible valepotriate regimen, mean about 81 mg/day | Four weeks | Constituent preparation in supervised psychiatric research (Original flexible dose). |
See the primary papers in the evidence table. These are neither equivalent amounts nor a ranking of potency. A larger extract number cannot be interpreted without its ratio, solvent and composition. The trials do not establish one optimum for all readers.
Do not increase a dose to imitate a more concentrated product or copy a psychiatric protocol from a table. A registered herbal medicine’s instructions apply to that medicine and jurisdiction, not to a differently composed supplement (Medicine-specific instructions and review trigger).
Animal and laboratory findings stay separate
GABA-related and other mechanistic findings are useful for hypothesis generation. They cannot establish human insomnia treatment, antidepressant action, protection against neurodegeneration or a reduction in medicine requirements. Laboratory constituent stability can explain why preparation matters without proving that instability accounts for every negative trial (Mechanism and stability limitations; Pharmacology context).
The EMA technical assessment and Shinjyo review provide pharmacology context. This article does not use cell or animal outcomes to upgrade the independent human-benefit grade.
Follow the money, countries and backers
Research funding at a glance
24 disclosure entries. The counts below summarize independence tiers explicitly assigned in this article. They count disclosures, not studies, funding amounts or evidence quality.
Consult this article’s source and funding notes for named funders, countries, relationships and exceptions where available. Institutional backing, researcher interests and trial sponsorship are separate questions. Public funding alone does not establish independence; commercial ties alone do not prove a claim false. This overview is not a new financial audit.
Commercial interests
The plant is not owned by a single company. Farmers, extract producers, supplement brands, herbal-medicine manufacturers and retailers can all earn revenue. A specific branded extract may have its own intellectual property and sales channel, but that does not give one company ownership of valerian as an ingredient.
OmniActive is relevant because it funded the newer positive extract trial. Its 2021 investment announcement documents TA Associates' investment and founder Sanjaya Mariwala's increased personal holding. Transaction adviser Investec reports a 54% stake acquired by TA in that January 2021 transaction. This is a dated transaction figure, not a verified October 2026 ownership percentage. It does not demonstrate control over the trial's result.
The same corporate announcement identifies Indian R&D/manufacturing operations and offices in India and the United States. The trial identifies the supplier in Mumbai, India. Neither fact establishes the botanical origin of every batch or the final manufacturing country of every retail capsule containing the ingredient.
Pharmavite, which donated the older-women study product, is a California-based subsidiary of Otsuka Pharmaceutical according to its company page. The parent relationship is relevant background; it is not evidence that any parent-company medicine influenced this trial. The exact historical donation is the demonstrated connection.
Universities, reviewers and regulators also need screening
The Norwegian trial’s public center funding is documented, but the manufacturer’s handling of study materials leaves a procurement question. The US studies show why “NIH funded” is not the end of the audit: donated or supplied products require separate attention (Public funding and tablet preparation; Grant/donation statements; Grants and supplied product).
The Shinjyo review reports no funding or competing interests and acknowledges Heartwood. Heartwood’s currently linked page publishes course fees and a Herbal Medicine Trust-funded bursary. This supports disclosure of a professional herbal-education interest; it does not identify who financed the review, every institutional donor or a manufacturer payment. Review disclosures; Current fees and bursary page.
AASM’s guideline was society-funded, with disclosed author consulting/research relationships to pharmaceutical and sleep-technology firms. Its recommendation remains useful clinical guidance, but this review does not label every author financially independent of insomnia treatment markets. NCCIH’s appropriations history documents public funding. Its complementary-health remit and reliance on a mixed literature are residual considerations, not grounds to assume either promotion or hostility (Complete guideline declarations; Enacted appropriations history).
TGA’s 2024–25 cost-recovery statement forecast about 78% of funding from fees and charges, with appropriations for specified public-good activities. EMA’s 2026 budget likewise reports substantial fee revenue alongside public contributions. These dated institutional accounts disclose financing mechanisms, but do not establish a valerian maker’s control over a warning or assessment. TGA fiscal model; EMA budget.
Documented relationship map

The diagram shows only the following supported links:
- TA Associates → OmniActive: 54% acquired in the January 2021 transaction, as reported by the seller’s adviser; current percentage not verified (January 2021 transaction).
- OmniActive, India → funding and publication fee for the proprietary-extract trial (Study and fee support).
- Pharmavite, US → donated product for the Taibi trial (Original donation acknowledgment).
- NIH, US → grants for the Taibi trial (NIH grants).
- Otsuka Pharmaceutical, Japan → parent of Pharmavite, whose company page gives a California address (Current parent and address statement; Tokyo head office).
- Norwegian Knowledge Centre → public funding for the Oxman trial; Cederroth handled study tablets, payment terms unknown (Original funding and materials).
- Dr. Willmar Schwabe, Germany → donated extract for Donovan’s interaction experiment (Original interaction study).
- BYK, Brazil → partial support and supplied drugs for the anxiety pilot (Original support and supply).
- Heartwood, UK → author affiliation in the Shinjyo review; no manufacturer-funding link claimed (Original affiliation; Fees and bursary).
An arrow records the stated relationship; it does not prove control over research. Current beneficial ownership, all institutional donors, individual historical regulator declarations and several older product-payment terms remain incompletely traced. Those gaps are not filled with assumptions.
Regulation and quality
European medicinal-use categories are preparation specific. The EMA assessment distinguishes well-established use for a particular ethanolic dry-extract category from traditional use for other preparations. A traditional-use registration is not a modern randomized trial of every claimed benefit (Adopted medicinal-use categories).
The live EMA listing retains the adopted 2016 monograph and lists a 2025 call for data under revision 2, with consultation closed. A data call is not an adopted new efficacy conclusion. Its current public summary explicitly excludes food supplements and other products from the medicinal assessment. Current document status.
US supplements are not FDA preapproved for effectiveness or safety in the manner of medicines. FDA explanation Australian oral valerian labeling has a liver-risk warning following the later TGA decision. Rules differ by product category and jurisdiction.
A purity certificate, pharmacopoeial identity check or good-manufacturing statement addresses quality, not clinical benefit. This review did not test a retail batch, audit every brand or identify a best-buy product. Root origin, extraction site, corporate headquarters and final packaging location should not be conflated.
Frequently asked questions
Does valerian help sleep?
Some trials report benefit, others do not. A dependable independent benefit has not been established for a generic retail valerian product (Original short trial; Proprietary trial; Inconsistent evidence summary).
Why does one regulator recognize it while a sleep guideline advises against it?
They ask different questions about specific preparations, traditional use and chronic insomnia. Regulatory status and the independent clinical evidence grade are separate judgments (Chronic-insomnia question; Preparation-specific medicinal framework).
Is standardized valerian better than tea?
The products differ, but a standardization marker alone does not prove comparative effectiveness. Do not translate milligrams of extract into an equivalent tea without validated information (Preparation definitions; Specified formulation).
Can I combine it with melatonin or a sleeping pill?
A favorable trial of one ingredient is not evidence for a stack. Sedating medicines, alcohol and other sleep products warrant professional review (Sedative/medicine precautions).
Does it damage the liver?
Liver injury appears rare, but the signal is serious enough to have prompted regulatory labeling. Stop and obtain advice for symptoms suggesting liver injury rather than dismissing them as normal supplement effects (Dated safety signal; Later warning and symptoms).
Is it addictive?
The literature does not establish benzodiazepine-like dependence for ordinary use, but withdrawal-like reports and inadequate long-term data make “never addictive, safe to stop in every circumstance” too strong (Long-term and withdrawal uncertainty; Historical withdrawal reports).
Can it treat anxiety or depression?
The evidence is insufficient. A mild-stress herbal indication is not proof of treatment for a diagnosed psychiatric disorder (Original GAD pilot; Mild-tension indication; Anxiety/depression uncertainty).
What would improve confidence?
Independently funded, preregistered trials of chemically characterized preparations, transparent product procurement, patient-important outcomes, adequate follow-up and replicated safety monitoring.
Sources and funding notes
Scope: the cited oral V. officinalis sleep and stress evidence, with related preparations identified separately. Pertinent original methods, results and disclosed support were checked; private data, every underlying review trial, all unpublished evidence and older supply contracts were not audited. A null result is not proof of no effect, and a favorable commercial result is not independent confirmation. This article is informational and does not replace qualified clinical assessment.
Tier 1 denotes provisionally noncommercial funding from available disclosures; Tier 2 indirect ties; Tier 3 interested professional/advocacy stakes; Tier 4 maker/seller funding or material support. U means unresolved information. Grades A–D are purpose-specific editorial assessments, not study-quality ratings or guarantees that every payment, donor and conflict was disclosed.
| Source | Funder/employer/revenue; HQ country or jurisdiction | Tier / grade | Accuracy incentive and residual limitation |
|---|---|---|---|
| Oxman 2007 | Norwegian public center support and employee authors; Cederroth tablet preparation, payment/donation terms not reported | Funding 1; procurement U / B provisional | Relevant full original methods/results/Tables1–4/disclosures read; short self-report trial, assumed primary threshold and exploratory multiplicity |
| Taibi 2009 | University of Washington/NIH, US; Pharmavite donated softgels | 4 / C | Academic accountability and objective measures; donated product, small sample |
| Barton 2011 | Mayo/NCCTG US public grants; Hi-Health supply, purchase/donation terms unknown; separate complete COI statement not located | U / B provisional | Accepted original manuscript main methods/results/Tables1–5/grant footnotes read; 119 primary-evaluable of 227 randomized |
| Chandra Shekhar 2024 | Indian clinical/CRO authors; OmniActive paid study and publication fee; authors declared no competing interests | 4 / C | Relevant main original methods/results/disclosures read; selected 18–50 population, per-protocol analysis and multiple unadjusted endpoints; Retrieved supplement table read; complete PSG table not reported there |
| Andreatini 2002 | Brazilian universities; BYK partial support and drug supply; CAPES/FAPESP fellowships; separate COI statement not located | 4 / C | Complete relevant five-page original Methods/Tables1–2/Results/discussion/support read; tiny flexible-dose pilot with negative primary between-group analysis |
| Shinjyo 2020 | Japan/UK academic and Heartwood affiliations; no funding or competing interests declared | 3 professional interest / C | Relevant full original methods/results/pharmacology/disclosures read; mixed studies, selected best dose, heterogeneous null-crossing sleep estimate; trial finances separate |
| AASM 2017 | US professional society funded guideline; author commercial consulting/research and PSQI intellectual property; complete society revenues not audited | 2 / B | Valerian recommendation, Appendix S24 and complete declarations read; historical weak guidance, not independent trial replication |
| NCCIH valerian | NIH public appropriation model, Bethesda US | 1 provisional / A for health summary | Public accountability; summarizes imperfect evidence, page-specific financing not itemized |
| NCCIH budget | US Congressional appropriations | 1 provisional / A for funding facts | Public record; no trial finding |
| EMA technical assessment | EU agency; fees/public contributions; current HQ Netherlands, EU/EEA remit | 2 institutionally / B | Regulatory accountability; dated mixed-provenance evidence, not sponsor-filtered benefit synthesis |
| EMA ingredient listing | Same agency and finance | 2 / B for document status | Official status record; review call is not a result |
| EMA 2026 budget | EU agency, Netherlands; fees and public support | 2 / A for finance facts | Public budget accountability; no efficacy role |
| Donovan 2004 | US university/NIH grants; Schwabe Germany donated extract; comprehensive individual COI statement not located | 4 / C | Actual full original methods/Table1/results/discussion read; small open fixed-order experiment, nightly valerian then morning probes; statistical/reporting and financial limits |
| TGA 2020 alert | Australian public regulator with cost recovery and some public funding | 2 / A for dated alert | Pharmacovigilance mandate; reporting bias and no incidence denominator; old labeling wording superseded |
| TGA final decision | Same Australian regulator; published consultation assessment | 2 / A for action and safety signal | Reasoned, accountable decision; case-causality uncertainty and industry submissions |
| TGA cost recovery | Australia; statutory fees/charges and government contributions | 2 / A for finance model | Public accounting; institutional self-report, no efficacy role |
| NHLBI insomnia guidance | US NIH public education; exact institute budget/editorial financial chain not audited | U / B for standard-care context | Entire official treatment page actually read; CBT-I first-line statement, not valerian comparison or financial clearance |
| FDA supplement guidance | US federal regulator; agency appropriation/user-fee accounts not verified by this page | U / B for regulatory remit | Entire official supplement overview read; product status is not efficacy approval or an agency financial audit |
| Adopted EU valerian monograph | EU regulatory document; agency fee/public budget separately verified, individual historic declarations not audited | 2 / B for specified medicinal instructions | Entire nine-page original read; preparation, age, pregnancy, driving and review instructions, not food-supplement efficacy |
| NHS emergency guidance | UK public clinical guidance; editorial and institutional finance not separately audited | U / B for emergency actions | Official symptoms/actions actually read; not valerian adverse-event incidence or effectiveness evidence |
| OmniActive investment announcement | Ingredient supplier, India/US offices; sales/investor interests | 4 / C for business facts | Investor/customer scrutiny; promotional self-presentation, historical snapshot |
| Investec deal account | Exclusive adviser to Everstone and other sellers in the January 2021 transaction; commercial financial interest, exact fee not stated | 3 / C | Actual original deal/date/54% statement read; historical transaction, not current cap table or verified ultimate investors |
| Pharmavite company | California US supplement company, Otsuka subsidiary | 4 / C for corporate relationship | Corporate accountability; sales interest; not benefit evidence |
| Heartwood fees | UK fee-charging herbal education; named trust-funded bursary; full donor/revenue/governance chain not audited | 3 / C for professional incentives | Current linked URL redirects to fees/enrolment; actual whole main page read, with review affiliation checked separately |
The conclusion rests on inconsistent and limited clinical evidence reviewed here. Reported commercial support and unresolved transactions affect the strict independence assessment without proving a result false. Methodological limitations, source role and finances remain separate judgments.
Have a question — or want us to cover something?
Ask about anything on this page, or request the next deep dive: an ingredient, a supplement, or a health concern. We use published research, evidence syntheses, and regulatory guidance, with clear source links.
One daily research roundup
Get the topics, key findings and links from our new articles in one email. At most one digest a day, only when there is something new.