
Key takeaways
- The reviewed Silexan trial program shows a positive short-term anxiety signal, with manufacturer support. It does not provide adequate sponsor-independent confirmation (Pooled trials).
- This evidence belongs to a defined swallowed preparation. It does not validate lavender tea, a diffuser or swallowing an aromatherapy oil
- Sleep findings here concern selected people with anxiety. They do not establish an immediate hypnotic effect or treatment for every form of insomnia (Original sleep reanalysis).
- The manufacturer-supported LEAD depression trial showed a clinician-rated benefit over eight weeks. Its September 2026 symptom analysis reuses the same participants (LEAD trial; Secondary analysis).
- Claims of equivalence or superiority to antidepressants and benzodiazepines require more caution than similar-looking symptom changes
- The Spanish Lasea label lists burping as common, but frequencies of other digestive complaints and severe allergy are unknown. Liver impairment, pregnancy and medicine combinations have product-specific restrictions (Authorized label).
Evidence verdict: Insufficient sponsor-independent confirmation for treating anxiety, insomnia or depression in the evidence reviewed here. The manufacturer-supported human program is clinically relevant. Confidence is moderate that a short-term anxiety signal exists within those trials; its generalizability and comparative effectiveness remain uncertain. Sponsorship does not prove results false, and no disclosure certifies every payment or product-supply relationship. Anxiety synthesis; Sleep reanalysis; Depression trial.
The useful question is not whether lavender smells relaxing. It is whether a defined oral preparation improves clinically important outcomes, in which patients, at what exposure, and with what uncertainty. Silexan and generic lavender oil should not be treated as one interchangeable category. Equally, counting multiple analyses of the same participants as separate confirmations makes the literature appear more replicated than it is.
Contents
Evidence summary · Identity · Forms · Mechanism · Hype · Benefits · Verdicts · Risks · Interactions · Who should avoid · Studied doses · Laboratory evidence · Funding · Regulation · FAQs · Sources
Evidence summary
The table separates the result from its eligibility for an independent benefit verdict. Public open-access support or an academic coauthor does not cancel manufacturer funding of the research.
| Claim | Human evidence and limitation | Funding trace | Independent verdict |
|---|---|---|---|
| Anxiety symptoms | Dold 2023: five ten-week placebo-controlled trials, 1,213 randomized; pooled positive signal, one individual trial not significant | All five manufacturer initiated; analysis/publication supported by Schwabe; employee and consulting ties | Insufficient independent confirmation |
| Generalized anxiety versus placebo/paroxetine | Kasper 2014, 539 randomized; Silexan superior to placebo, paroxetine not significant in full analysis | Schwabe sponsorship and author ties | Relevant commercial result; no broad drug-equivalence verdict |
| Generalized anxiety versus lorazepam | Woelk 2010, 77 randomized, six weeks, no placebo | Sponsor consultant and Schwabe employee | Does not establish a general benzodiazepine substitute |
| Sleep disturbed by anxiety | Seifritz 2019: mediation analysis of an earlier anxiety trial | Manufacturer-supported reanalysis, employee and honoraria ties | Not independent chronic-insomnia efficacy |
| Mild-to-moderate major depression | LEAD trial, 500 randomized, 498 treated/analyzed; eight-week clinician-rated benefit over placebo | Schwabe sponsored research and publication, company coauthors | Encouraging sponsored signal; independent replication needed |
| September 2026 depression findings | Item-level analysis of LEAD | Same sponsor and underlying patients | Exploratory secondary analysis, not another trial |
| Long-term and adolescent safety | 2025-online/2026-issue database analysis | Schwabe funding and employee/IQVIA authors | Limited observational reassurance, not definitive safety or pediatric efficacy |
| All oral lavender products | NCCIH highlights preparation, funding and participant-diversity limitations | US public health-information source | No class-wide benefit can be assumed |
What oral lavender and Silexan are
Lavender refers to a group of aromatic plants and many preparations. Silexan is a proprietary essential-oil preparation from Lavandula angustifolia flowers, produced for oral administration. Linalool and linalyl acetate are prominent constituents. Steam-distilled oil, a water infusion and a topical fragrance have different compositions and exposures. Clinical/pharmacological review
This article focuses on oral oil and the Silexan evidence program. Aromatherapy, topical products and tea are discussed only to prevent inappropriate transfer of claims. Do not substitute an aromatherapy essential-oil bottle for an oral medicinal or supplement preparation. No safe home conversion from drops or diffuser oil to the clinical capsule dose is established here.
Forms and grades
| Form | What it represents | What the evidence can support |
|---|---|---|
| Silexan oral soft capsule | Defined proprietary lavender-oil preparation | The preparation in the main anxiety program; sponsorship still matters (Preparation review). |
| Licensed Lasea medicine in a particular country | Product with a jurisdiction-specific authorization and leaflet | Follow that product’s approved scope; not a global approval for every mental-health claim (Spanish label). |
| US Silexan-containing supplement | Supplement regulatory category, potentially different instructions/excipients | Ingredient identity does not make the product an FDA-approved treatment (US product; FDA regulatory explanation). |
| Other oral lavender oil capsule | May differ in species, chemistry and manufacture | Do not assume equivalence without product-specific evidence (Preparation and route). |
| Tea, syrup or non-oil extract | Different extraction and composition | Requires its own clinical evidence (Extraction differences). |
| Topical oil, massage or inhaled fragrance | Different route and contextual effects | Cannot inherit oral trial estimates (Route-specific overview). |
| Multi-ingredient calming formula | Several active substances | Cannot isolate lavender’s contribution (Preparation-specific evidence). |
The Spanish regulator-hosted Lasea information and the US CalmAid supplement label illustrate why readers must specify the product and jurisdiction. Their age warnings, use instructions and regulatory categories should not be merged into a fictional universal label.
How it might work
Research explores calcium-channel signaling, serotonin-related pathways and changes in neuronal function. The Kasper/Eckert review describes these hypotheses; both authors disclose Schwabe-related financial relationships. Its mechanistic narrative is context, not an independently demonstrated explanation of every clinical effect.
A constituent acting on a receptor is not the same thing as a proven treatment. Exposure, distribution, the mixture of compounds and the actual patient outcome still matter. Silexan should not be described as “natural serotonin,” a nutritionally necessary deficiency correction, or a drug-equivalent solely because a pathway overlaps with that of another treatment.
Hype versus evidence
The commercial program is more substantial than a few anecdotes, but three shortcuts deserve resistance.
First, publication count is not replication count. Anxiety totals, sleep mediation, physical symptoms, depression subscales and later pooled analyses may reuse the same participants. They can answer additional questions without becoming new trials (Pooled trial set; Reused sleep data; Reused LEAD data).
Second, similar average improvement is not established equivalence. A comparator dose, a trial’s purpose, its noninferiority margin and whether the comparator worked against placebo all affect interpretation. “As good as an SSRI” is too broad a conclusion from one short fixed-dose study (Placebo/active-comparator design; Lorazepam study).
Third, a non-sedating profile is not permission to ignore impairment or combinations. Someone may still experience adverse effects, use other medicines or be unsafe to drive because of the underlying illness. The label and clinical context remain relevant (Fatigue and combination precautions).
Benefits by claim
Anxiety symptoms — Positive sponsor evidence; insufficient independent confirmation
The five-trial pooled program favored 80 mg/day Silexan by 2.93 HAMA points (95% CI 1.07–4.77); the standardized difference was 0.35 (0.13–0.56). It included 1,213 randomized participants, with 1,172 in the efficacy analysis. Between-study heterogeneity was substantial (I² 72.7%). All trials lasted ten weeks, took place in Germany and were manufacturer initiated. Dold 2023.
That is a real statistical signal in the reported data, not proof that every participant improved or that the finding transfers to every population. The independent question is still open. A university-led meta-analysis can assess an industry trial more critically, but it cannot turn the participants into an independently financed replication.
The 2019 Yap network review declares no competing interests, but its full text does not report project funding. Its comparative tables and narrative give discordant drug estimates and significance claims, making treatment rankings unreliable. The newer network review was supported by Schwabe Pharma AG and relies on indirect comparisons. Neither adds sponsor-independent original participants. Yap review; Newer network review.
Comparison with antidepressants — No broad equivalence conclusion
The 539-person paroxetine-controlled trial primarily tested Silexan superiority to placebo and stopped at a prespecified interim analysis. Paroxetine 20 mg/day did not significantly outperform placebo in the full-analysis comparison (p=0.10), but did in the observed-case analysis. Greater premature withdrawal in the paroxetine group affected carried-forward estimates. No formal drug-equivalence hypothesis was specified. Original design and results.
Comparative effectiveness also includes relapse, functioning, discontinuation, interactions and harms over time. One short trial cannot establish a ranking for everyone with an anxiety disorder. It is inappropriate to stop or replace prescribed treatment on the strength of a supplement advertisement quoting that comparison.
Comparison with lorazepam — Limited, commercially linked experiment
The six-week study randomized 77 adults to 80 mg/day Silexan or 0.5 mg/day lorazepam, without a placebo arm. Mean HAMA reductions were 11.3 and 11.6 points; the 90% confidence interval for their difference ran from −2.3 to 2.8 points. The primary Methods describe a confidence-interval comparison without stating a numerical equivalence margin. The small sample, fixed comparator dose and absent placebo constrain a broad equivalence or acute-rescue claim. Woelk and Schläfke 2010.
Sleep — Anxiety-associated improvement, not a universal hypnotic
The post-hoc sleep analysis reused a ten-week trial of adults with subthreshold anxiety, restlessness and disturbed sleep. It modeled improvement as largely mediated through anxiety reduction. Subjective sleep outcomes and mediation assumptions do not establish a causal biological pathway, an acute hypnotic effect or primary-insomnia efficacy. Seifritz 2019.
A change in a sleep questionnaire after weeks of anxiety treatment does not establish immediate sedation, more objectively measured deep sleep or treatment of sleep apnea, circadian disorders or primary chronic insomnia. The practical sleep claim should remain narrower than the marketing category “sleep support.” Persistent insomnia needs its own assessment; NHLBI identifies CBT-I as the usual first treatment option.
Major depression — Newer sponsored signal, not independent confirmation
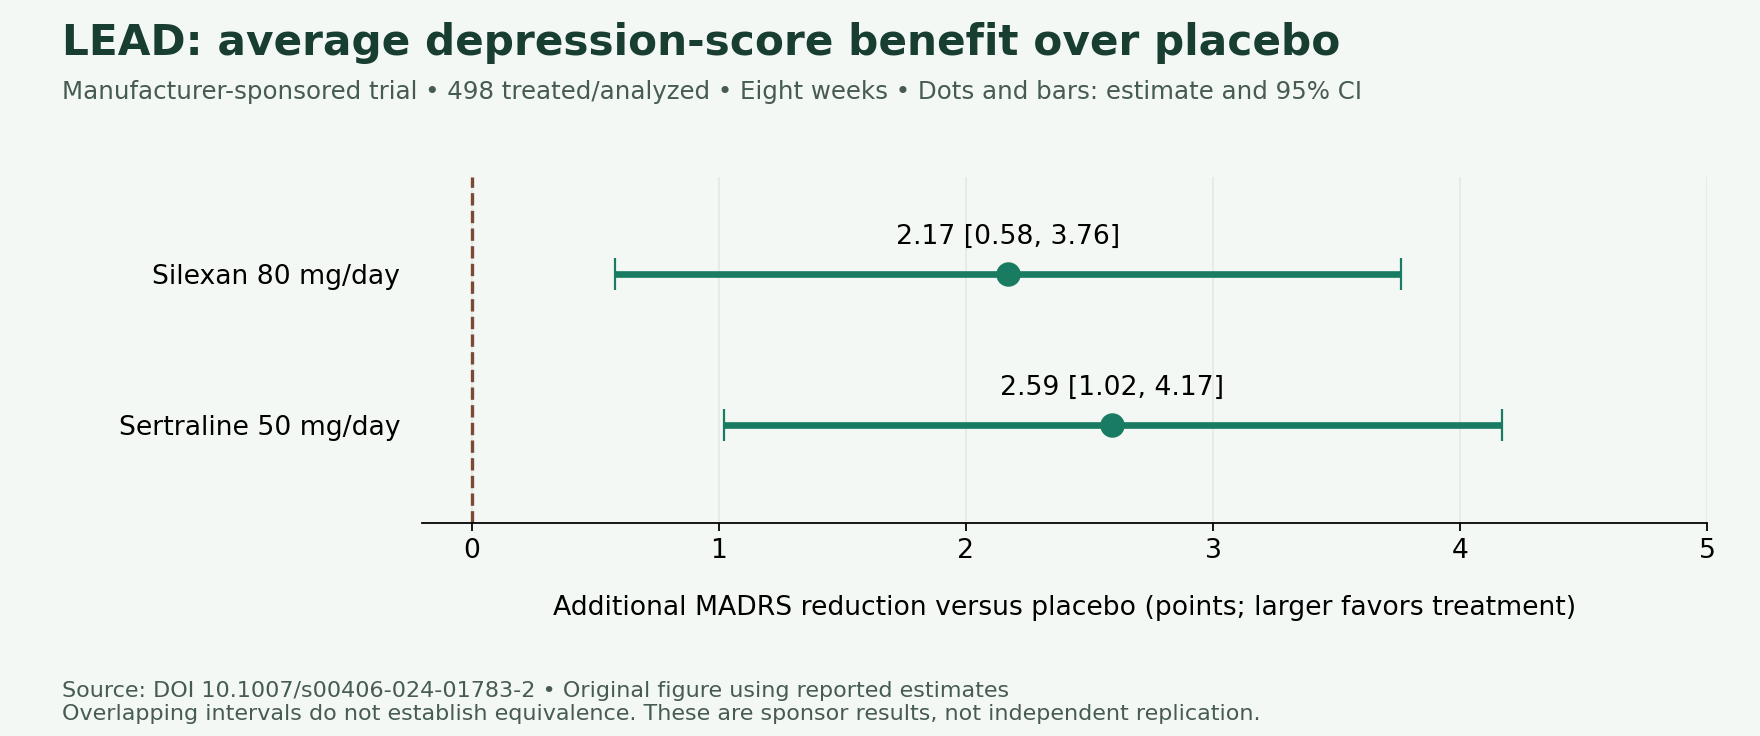
LEAD found an average advantage over placebo of 2.17 MADRS points (95% CI 0.58–3.76) after eight weeks. The lower bound allows a smaller benefit than the authors’ preferred clinical-importance threshold. BDI-II and PHQ-9 self-rated depression comparisons were not significant (p=0.085 and p=0.077). Original LEAD report.
Participants had mild-to-moderate depression; important anxiety, suicidality, treatment resistance and psychotherapy were excluded. These findings do not establish benefit in those excluded groups. Similar observed performance to fixed-dose sertraline is not formal broad equivalence (Eligibility and trial purpose).
The September 2026 paper examined symptom items from the same LEAD data. Its exploratory analyses had no studywise multiplicity control; the sleep item did not significantly favor Silexan. It adds detail rather than new replication. “Independent” in its proposed depression mechanism does not describe independent funding. Original secondary analysis.
Everyday stress, panic or other disorders — Insufficient
A diagnosed anxiety trial cannot automatically establish benefits for performance stress, panic attacks, obsessive-compulsive disorder, trauma symptoms or post-COVID complaints. Different target populations and outcomes require separate evidence. Uncontrolled improvement or a case series is not enough to distinguish a treatment effect from concurrent care or natural recovery.
For clinically important anxiety, NICE's treatment guidance includes psychological treatment and medicines within a stepped-care approach. This article does not position lavender as a substitute for assessment or established care.
What works and what is not established
| Question | Evidence-based answer | Remaining gap |
|---|---|---|
| Does the reported sponsor trial program show an anxiety signal? | Yes | Independent original replication and broader populations (Trial synthesis). |
| Is the independent benefit verdict strong? | No | Direct financial ties dominate the key clinical program (Original disclosures; LEAD disclosures). |
| Is it a proven immediate sleeping pill? | No | Sleep evidence largely concerns anxiety-related disturbance (Sleep analysis). |
| Is the depression finding worth following? | Yes | Sponsor-independent replication, durability and broader clinical settings (LEAD trial). |
| Is it interchangeable with antidepressants or benzodiazepines? | Not established | Appropriate comparative designs and longer follow-up (Paroxetine comparison; Lorazepam comparison). |
| Can a diffuser or tea reproduce the capsule effect? | Not established | Route and composition differ (Preparation and route). |
| Is indefinite use or pediatric use proven safe? | No | Controlled longer follow-up and age-specific research remain inadequate (Observational limits; Age/duration restrictions). |
Risks and side effects
| Issue | Evidence | Important boundary |
|---|---|---|
| Lavender-flavored burping and digestive symptoms | Spanish Lasea: burping common; frequency of other GI complaints unknown (Label section 4.8). | A different product or study need not have the same frequency |
| Severe allergy | Swelling, circulatory or breathing problems reported; frequency unknown (Label). | Stop the product. Sudden throat/tongue swelling, breathing difficulty or collapse needs immediate emergency help (Emergency guidance). |
| Liver impairment | Contraindication in the inspected Spanish Lasea label | A product-specific restriction, not proof that lavender routinely damages the liver |
| Dialysis and older age | Lasea not recommended during dialysis; limited safety/efficacy data above 65 (Product precautions). | Product-specific limits; do not generalize healthy-volunteer findings |
| Pregnancy and breastfeeding | Spanish Lasea not recommended in pregnancy; breastfeeding patients must not take it (Product restrictions). | Broader lavender safety information is inadequate (Clinical overview). |
| Children and adolescents | Spanish Lasea is adult-only and not recommended below 18; the US supplement directions also specify adults (Medicine label; Supplement directions). | Observational adolescent prescriptions do not establish efficacy or unsupervised suitability |
| Long-term use | Routine-care data add context, not definitive exclusion of harm | Missing recorded complaints can reflect under-recording |
The regulator-hosted label is authoritative for that product's instructions and warnings. NCCIH separately summarizes gastrointestinal effects and pregnancy uncertainty. A short trial with similar overall adverse-event counts cannot rule out rare events or guarantee safety in excluded groups.
What the newer long-term data do and do not show
The Volz database study, published online in 2025, combined German and Swiss prescribing data. Its headline 67,340 adults were not all followed as long-term users with systematic safety examinations: the German long-term adverse-complaint analysis had 1,141 eligible patients, and the Swiss database lacked safety outcomes. Treatment duration was inferred from prescriptions. Schwabe funded the research, with company and IQVIA employees among authors.
That is useful pharmacovigilance context, but it does not prove that months or years of use are harmless. People who tolerate and continue a product differ from those who stop it, and routine records miss events. Nor does observed adolescent prescribing establish pediatric effectiveness or override an adult-only medicine label.
The fifty-patient Israeli chart review was uncontrolled; 46% received other medicines and the investigator could not extract Silexan doses. Manufacturer-paid writing and publication support are explicitly disclosed alongside a no-conflict statement. It provides observational context, with uncertain attribution and safety recording, rather than independent efficacy confirmation. Original chart review.
Hormonal headlines need route-specific caution
Reports of breast-tissue changes in children exposed to topical lavender-containing products do not establish the same effect from adult oral Silexan. NCCIH regards causation in those reports as uncertain. Conversely, uncertainty is not evidence that every preparation has been proven hormonally inert. Keep topical observations, laboratory endocrine experiments and adult oral safety separate (Route-specific safety).
Interactions
| Exposure | Evidence level | What the finding does not prove |
|---|---|---|
| Ethinyl estradiol/levonorgestrel combined contraceptive | 24 women randomized; 22 in PK analysis. Selected concentrations and hormonal measures were reassuring at 160 mg/day (Original crossover trial). | 30 µg ethinyl estradiol / 150 µg levonorgestrel; additional nonhormonal contraception required. Not a pregnancy-outcome study or every formulation |
| CYP-metabolized medicines | 16 completed an eleven-day 160 mg/day crossover experiment. Primary CYP2C19 measure did not meet the no-interaction interval; secondary measures were reassuring (Original study). | Authors attribute the result to variability, but explicitly could not formally exclude CYP2C19 inhibition. Not every drug, dose or additive effect |
| Anxiolytics, sedatives or alcohol | Regulated label advises against the combination as a precaution because clinical data are lacking | This is not a quantified demonstrated interaction for each possible medicine (Combination precaution). |
| Antidepressant add-on use | Comparing separate trial arms is not combination evidence | No automatic authorization to stack or switch (Anxiety trial arms; Depression trial arms). |
| Planned anesthesia | NCCIH notes theoretical sedative interactions relevant to surgery (Clinical overview). | Tell the procedural team the exact product; no universal stop interval established here |
The contraceptive study and CYP study were manufacturer-supported work-for-hire studies with company coauthors. They provide bounded human data, not independent proof of zero interaction risk. The Lasea label preserves precautions despite those findings.
Clinical and pharmacokinetic questions are different: unchanged drug concentration cannot exclude additive symptoms, and a small concentration change does not automatically predict serious harm. A pharmacist should assess the exact regimen rather than relying on a generic “no interactions” badge.
Who should avoid self-treatment
- The inspected Spanish Lasea label contraindicates liver impairment and does not recommend use during dialysis; seek product-specific clinical advice (Contraindications and precautions).
- Pregnant or breastfeeding people and anyone under eighteen should not infer suitability from the adult Silexan trials (Product restrictions; Safety uncertainty).
- People taking psychiatric or sedating medicines should involve the prescribing clinician before adding, stopping or switching treatment (Combination precaution).
- Those with severe, worsening or function-limiting depression/anxiety need clinical care; this evidence does not justify delaying it (Clinical care; Depression assessment).
- Sudden throat or tongue swelling, breathing difficulty or collapse after a product requires immediate emergency help; stop using it (Product allergy warning; Anaphylaxis guidance).
- Anyone experiencing fatigue or impaired alertness should not drive, regardless of a “non-drowsy” marketing claim (Fatigue and driving).
These precautions are not a claim that all lavender exposure is dangerous. They distinguish ordinary fragrance or food exposure from purposeful treatment with concentrated oral preparations.
Studied doses, not a personal prescription
| Research setting | Amount and schedule | Duration |
|---|---|---|
| Main anxiety placebo-controlled program | Silexan 80 mg once daily | Ten weeks (Original pooled protocols). |
| Paroxetine-controlled anxiety study | Silexan 80 or 160 mg/day | Ten weeks (Original protocol). |
| Lorazepam comparison | Silexan 80 mg/day | Six weeks (Original protocol). |
| LEAD depression study | Silexan 80 mg once daily, morning | Eight weeks (Original protocol). |
| CYP interaction experiment | Silexan 160 mg/day | Eleven-day experimental periods (Original protocol). |
| Contraceptive interaction experiment | Silexan 160 mg/day with the specified combined pill | Two 28-day crossover cycles |
The primary sources above define the preparation. These are not generic lavender-oil amounts and must not be translated into drops from a fragrance bottle. The table does not establish that 160 mg is the best dose for a given person, that an immediate effect should occur, or that treatment should continue indefinitely.
The Spanish Lasea label specifies adults, 80 mg once daily, no more than three months; consult a doctor if unchanged after one month or worse. It does not recommend use below 18. The US CalmAid page instructs adults to use one 80 mg softgel once or twice daily, and warns against use during pregnancy, nursing or below 12. That warning does not itself authorize use at ages 12–17. Follow the exact product’s label and clinical advice. Spanish medicine label; US supplement directions.
Animal and laboratory evidence stays separate
Calcium signaling, serotonin-receptor findings, cell survival and animal behavior can motivate research. They cannot establish clinical antidepressant equivalence, a cure for insomnia, brain repair or prevention of psychiatric disease. The mechanistic review includes human and nonhuman work, and its authors disclose product-company relationships.
The independent clinical verdict is not upgraded because the proposed mechanism sounds similar to that of an established medicine. A hypothetical mechanism also cannot determine the direction or magnitude of a clinical drug interaction without relevant data.
Follow the money, countries and backers
Research funding at a glance
25 disclosure entries. The counts below summarize independence tiers explicitly assigned in this article. They count disclosures, not studies, funding amounts or evidence quality.
Consult this article’s source and funding notes for named funders, countries, relationships and exceptions where available. Institutional backing, researcher interests and trial sponsorship are separate questions. Public funding alone does not establish independence; commercial ties alone do not prove a claim false. This overview is not a new financial audit.
Who profits
Silexan is associated with Dr. Willmar Schwabe’s commercial product program. The manufacturer funds original trials, several pooled analyses, interaction studies and newer routine-care research. That is a direct financial interest in demonstrating benefit and acceptable tolerability. Academic collaborators have scholarly incentives and, where disclosed, consulting or lecture relationships; those ties are reported rather than inferred from a person’s nationality or profession (Pooled program disclosures; LEAD disclosures; Interaction support; Database support).
The group's legal imprint identifies Dr. Schwabe Holding SE & Co. KG in Karlsruhe, Germany. Its ownership statement says the group remains fully Schwabe-family owned and identifies Olaf Schwabe's leadership. These are company disclosures, not independent audited cap-table verification. Individual family holdings and all subsidiary percentages were not traced.
The US CalmAid page documents a Silexan-containing product and its commercial claims. It is useful for identifying the marketed ingredient, not as proof of effectiveness. The article does not rank sellers or infer that every lavender supplier belongs to this group.
Research countries are not manufacturing countries
The core anxiety trials were conducted in Germany. LEAD included German and Polish sites. Pooled author groups include Austria, Germany and Switzerland. The newer routine-care database study used German and Swiss data, and the small chart review came from Israel. This extends setting coverage but not automatically independent replication (Anxiety trial sites; LEAD sites; Databases; Chart setting).
The pharmaceutical company's headquarters, botanical growing location, extraction facility and final capsule manufacturing country are different facts. The audited records do not verify the raw-material origin and manufacture of every currently sold batch. Mediterranean plant origin is not proof of present sourcing.
“University funded” can be a partial truth
The LEAD report and the 2023 meta-analysis list university open-access support while also disclosing manufacturer support. The 2025 network analysis likewise lists university open-access support and a Schwabe Pharma grant. Reporting only the university line would conceal material information (Anxiety research/OA funding; LEAD research/OA funding; Review grant/OA funding).
The full Yap review declares no competing interests but has no project-funding statement. Financing therefore remains unreported, rather than established as noncommercial. Its internal comparative-reporting conflicts also limit rankings. Review financing and the funding of its underlying trials are separate questions. Original review.
NCCIH's appropriations record provides public-source provenance. AEMPS publishes budget/governance information and regulatory fee information. Public agencies have legal accountability and potential institutional/resource pressures; a medicine label hosted by a regulator is not a new independent efficacy experiment.
Documented relationship map
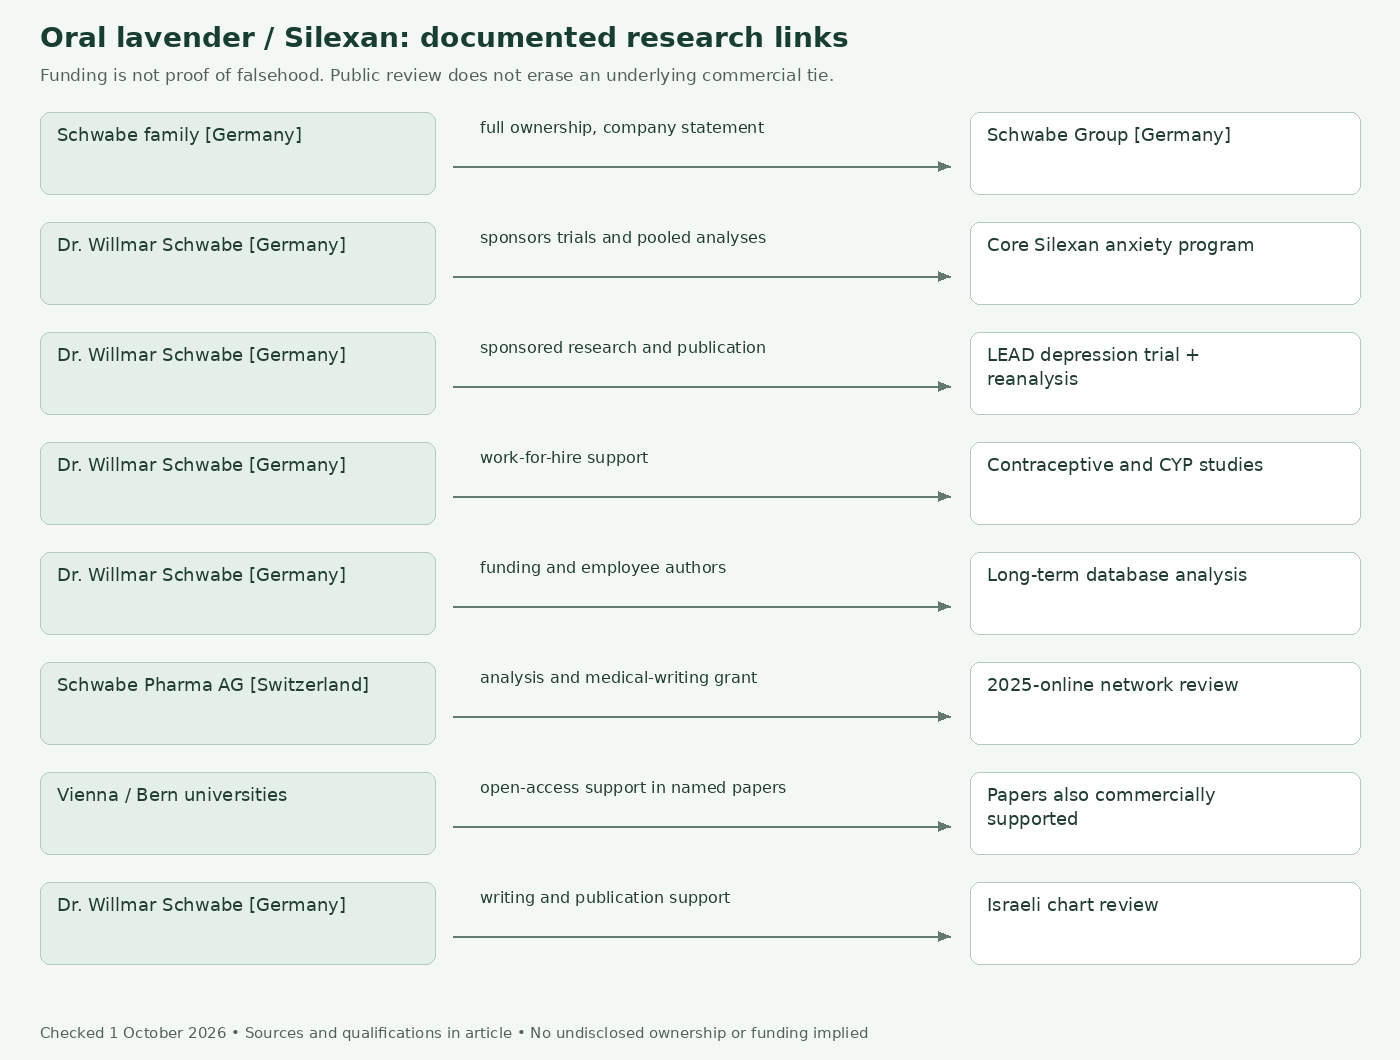
- Schwabe family → full group ownership according to the company; individual stakes not independently verified (Company ownership statement).
- Dr. Schwabe Holding → disclosed legal group entity in Karlsruhe, Germany (Legal imprint).
- Dr. Willmar Schwabe → disclosed sponsor of anxiety trials and pooled research (Original trial funding; Pooled research funding).
- Dr. Willmar Schwabe → LEAD research/publication support and the later symptom analysis (LEAD disclosures; Secondary-analysis disclosures).
- Dr. Willmar Schwabe → interaction work-for-hire studies and routine-care database research (Contraceptive trial; CYP trial; Database study).
- Schwabe Pharma AG, Switzerland → grant including analysis/writing for the 2025-online network review (Original funding declaration).
- Medical University of Vienna / University of Bern → disclosed open-access support alongside commercial research support in specified papers (Vienna: anxiety analysis; Vienna: LEAD; Bern: network review).
- Dr. Willmar Schwabe → paid medical writing/editorial assistance and open-access publication for the Israeli chart review (Original funding declaration).
The diagram deliberately does not imply that paying a publication fee proves manipulation, that every coauthor is an employee, or that the legal holding company directly paid each invoice. Exact flows and supplier contracts not disclosed remain unknown.
Regulation and product quality
In Spain, Lasea's authorized information specifies an adult herbal medicine for transient anxiety symptoms. It is not a blanket authorization for all depression or insomnia claims. The marketing authorization holder is Dr. Willmar Schwabe, Germany.
In the United States, CalmAid is presented as a dietary supplement with the usual FDA disease-treatment disclaimer. FDA's supplement explanation clarifies that supplements do not undergo drug-like premarket efficacy approval. Shared ingredient branding does not erase the regulatory difference.
No retail batch was independently tested for this review. Product identity, correct oral-use formulation, contaminants, stability and complete excipients matter. Even a valid quality certificate would not establish comparative clinical benefit.
Frequently asked questions
Does oral lavender work for anxiety?
The Silexan sponsor-funded trials show a positive overall signal. Independent original confirmation is inadequate under this review’s stricter funding rule (Reviewed trial program).
Is lavender tea or aromatherapy equivalent?
No. Route, extraction and exposure differ. Do not borrow capsule effect sizes or doses (Preparation and route).
Can I swallow lavender essential oil sold for a diffuser?
Do not use it as a substitute for the studied oral preparation. This article provides no safe home conversion or ingestion protocol for such products (Defined oral preparation; Label-specific safety).
Will it make me sleep immediately?
The main evidence is treatment over weeks in people with anxiety, with sleep assessed as a related outcome. It is not proof of an immediate hypnotic effect (Weeks-long anxiety/sleep analysis).
Is it as effective as an SSRI?
The comparisons do not establish broad equivalence. Study purpose, comparator dose, response to placebo and patient selection matter (Original comparator purpose).
Is the 2026 depression paper a new confirming trial?
No. It analyzes symptom items from LEAD. Its exploratory findings should not be counted as independent replication (Exploratory analysis).
Does it interfere with the pill?
One manufacturer-supported crossover study analyzed 22 women using the specified ethinyl estradiol/levonorgestrel pill. Concentration and hormonal findings were reassuring, but additional nonhormonal contraception was required; it did not test pregnancy prevention or every formulation. Discuss the exact regimen with a pharmacist (Original trial).
Is long-term or adolescent use now proven safe?
No. Newer observational records add information but have incomplete exposure and adverse-event ascertainment. They do not replace controlled age-specific evidence or product labeling (Observational limitations; Label restrictions).
Sources and funding notes
Scope: the cited oral lavender and Silexan evidence for selected anxiety, sleep and depression claims. Pertinent original methods, results and disclosed finances were checked; supplements, private raw data, all unpublished trials and every product-supply transaction were not independently audited. This article is informational and does not replace qualified clinical assessment.
Tier 1 is provisional from available noncommercial disclosures; Tier 2 indicates indirect ties, Tier 3 an interested party, and Tier 4 maker/seller-supported material. U means unresolved information. Purpose-specific grades A–D are editorial assessments; neither a tier nor a no-conflict declaration certifies every donor, author relationship or study method. Research affiliations need not identify manufacturing or publisher headquarters.
| Source | Money, employer or revenue model; country/jurisdiction | Tier / grade | Accuracy incentive and residual limitation |
|---|---|---|---|
| Dold 2023 | Schwabe research/publication support, company employee; university open-access support; Germany/Austria/Switzerland | 4 / C | Registered trials and explicit disclosures; shared sponsor, one-country trials and heterogeneous outcomes |
| Kasper 2014 | Schwabe study funding; employee coauthors and consultant/speaker/research relationships; Germany/Austria | 4 / C | Complete relevant original methods/results/disclosures read; prespecified interim stopping, LOCF/withdrawal and descriptive comparator limits |
| Woelk 2010 | Schwabe expressly named sponsor; consultant Woelk and employee Schläfke; Germany | 4 / C | Complete relevant original read; small no-placebo, fixed-dose comparison; primary Methods lack stated numerical equivalence margin |
| Seifritz sleep analysis | Schwabe support; employee and educational-honoraria ties; Germany/Switzerland | 4 / C | Full pertinent original methods/results/disclosures read; reused selected anxiety trial and post-hoc mediation assumptions |
| LEAD trial | Schwabe sponsorship/publication and employees; Vienna open-access support; German/Polish sites | 4 / C | Larger blinded trial; selected mild/moderate population and sponsor dependence |
| September 2026 analysis | Schwabe funding and employee; other author ties; European investigator group | 4 / C | Explicit exploratory status; same trial, no multiplicity control |
| Yap 2019 | Academic authors in Malaysia/Australia/UK/Pakistan; no competing interests declared; project funding not reported in full text | U / C for comparative rankings | Full pertinent original read; sparse commercial trial network plus discordant comparative tables/narrative; no independent original replication |
| 2025-online network review | Schwabe Pharma AG grant including analysis/writing; Bern open-access support; Swiss/European author ties | 4 / C | Main original methods/results/disclosures read; indirect comparisons; complete supplements and underlying-trial finances not independently audited |
| Volz long-term database study | Schwabe funds; Schwabe/Holding/IQVIA employees and consultancy; Germany/Switzerland | 4 / C | Defined database methods; incomplete actual use/safety recording, no efficacy endpoint |
| Marchevsky chart review | Israeli clinician; Schwabe paid medical writing/editorial assistance and OA; no-conflict statement also present | 4 / C | Relevant original main text/disclosures read; uncontrolled retrospective cohort, 46% comedication, doses not extractable; individual supplement not separately checked |
| Contraceptive trial | Schwabe work-for-hire; company authors; German/Dutch organizations; exact supply payments unreported | 4 / C | Original relevant methods/results/disclosures read; 24 randomized, 22 PK analyzed, selected pill and surrogate endpoints; not pregnancy efficacy |
| CYP study | Schwabe work-for-hire, employee/honoraria ties; German research organizations | 4 / C | Relevant original methods/results/disclosures read; 16 completers, eleven-day exposure; primary CYP2C19 no-interaction criterion failed |
| Kasper/Eckert review | Vienna OA; both authors disclose Schwabe grants/advisory/consulting relationships; Austria/Switzerland; medical-writing payer not specified | 3 + U / C | Relevant original identity/mechanism/clinical synthesis/disclosures read; narrative review, reused program; review-specific support and underlying supply terms incomplete |
| NCCIH lavender | US NIH public-information service | 1 provisional / A for safety/evidence overview | Public accountability; mixed underlying research and limited product detail |
| NCCIH appropriations | US public funding record | 1 provisional / A for finance | Auditable history; no clinical outcome role |
| NHLBI insomnia | US NIH public education; exact institute budget and editorial financial chain not audited here | U / B for care context | Official CBT-I recommendation personally read; no lavender comparison or financial clearance of underlying research |
| NICE GAD guidance | UK public guidance body; historic panel-specific ties not fully re-audited here | 1 provisional / B | Accountable care guidance; scope/context only, not lavender efficacy source |
| AEMPS-hosted Lasea label | Holder Schwabe, Germany; regulator Spain; regulated manufacturer product document | 4 provenance / B for authorized instructions | Legal labeling accountability; not independent trial evidence |
| AEMPS budget/governance | Spanish public agency, Madrid; public budget/transparency system | 2 institutional / A for remit | Public record; no product-specific funding conclusion |
| AEMPS fees | Spanish agency; statutory applicant fees | 2 / A for finance model | Legal accountability; no efficacy finding |
| Schwabe ownership | Private family-owned group, Germany; health-product sales | 4 / C for ownership claim | Corporate reputation; self-report, individual share register unavailable |
| Schwabe legal imprint | German commercial holding entity and legal registry details | 4 / C for identity | Legal disclosure requirements; not a full consolidated ownership audit |
| CalmAid label/sales page | Nature’s Way commercial supplement sales; contracts/ultimate ownership not audited | 4 / D for benefit advertising | Current adult instructions/facts/warnings read; no independent efficacy role and no pediatric recommendation inferred from under-12 warning |
| FDA supplement overview | US federal regulator; agency budget/user-fee accounts not reviewed for this article | U / B for regulatory remit | Official regulatory explanation personally read; supplement status is not oral-lavender treatment approval |
| NHS anaphylaxis guidance | UK public clinical guidance; institutional funding/editorial chain not separately audited | U / B for emergency recognition/actions | Official symptoms and immediate-action guidance read; not lavender efficacy or adverse-event frequency evidence |
Commercial financial relationships limit eligibility for the strict benefit verdict without erasing reported results. Methodological and reporting weaknesses are assessed separately. Source-specific declarations are recorded; unreported funding, procurement terms, exact amounts and ultimate ownership remain unknown.
Have a question — or want us to cover something?
Ask about anything on this page, or request the next deep dive: an ingredient, a supplement, or a health concern. We use published research, evidence syntheses, and regulatory guidance, with clear source links.
One daily research roundup
Get the topics, key findings and links from our new articles in one email. At most one digest a day, only when there is something new.