
Key takeaways
- Chamomile has a plausible calming effect, but its reputation as a reliable insomnia treatment runs ahead of the evidence
- A small publicly funded insomnia pilot found no significant sleep benefit; its authors explicitly denied manufacturer financial or drug support (Original pilot).
- Other sleep studies report improvements, but preparations, populations, blinding and study quality vary considerably
- Anxiety research is promising but small. The main long-term study did not significantly prevent relapse on its primary outcome
- Tea, standardized extracts, essential oils and isolated apigenin are different interventions; their doses and results are not interchangeable
- Serious allergy is possible. Warfarin, sedatives, pregnancy, breastfeeding and hormone-sensitive conditions need particular caution
Evidence verdict: Insufficient evidence for treating insomnia or generalized anxiety disorder. Selected mood findings remain preliminary. Public grants, explicit non-contribution statements and documented product purchases improve transparency, but do not audit every financial relationship. The small insomnia pilot did not demonstrate sleep benefit. Positive findings come from selected populations and have methodological, reporting or procurement limits. Confidence in a broadly applicable treatment effect remains low. Insomnia pilot; Sleep review; Anxiety continuation trial; Postpartum trial.
Chamomile is familiar as a bedtime drink. That familiarity makes two distinctions especially important: enjoying a warm herbal tea is different from demonstrating a clinically useful sleep effect, and a concentrated extract tested in a trial is different from the tea in a kitchen cupboard. This review focuses on German chamomile for sleep, anxiety and related mood claims. It does not extend these results to every herbal blend, oil or apigenin capsule sold under a calming label.
Contents
Evidence summary · Identity · Forms · Mechanism · Hype · Benefits · Verdicts · Risks · Interactions · Who should avoid · Studied doses · Laboratory evidence · Funding · Regulation · FAQs · Sources
Evidence summary
| Claim | Human evidence | Funding and procurement | Independent interpretation |
|---|---|---|---|
| Chronic primary insomnia | Zick 2011: 34 adults; double-blind, placebo-controlled, 28 days; no significant between-group sleep benefit | University/NIH support; authors explicitly denied MediHerb financial or drug contribution | Small publicly funded pilot; insufficient benefit evidence; some narrative/table p-values conflict |
| Sleep quality across populations | Kazemi 2024 review: ten studies, 772 participants; five-study PSQI pooling favored chamomile, with marked heterogeneity | Review reports no specific grant and no competing interests; underlying studies not uniformly conflict-cleared | A mixed literature cannot be treated as one independently confirmed treatment |
| Older adults’ sleep | Adib-Hajbaghery 2017: 60 participants; single-blind, wheat-flour control; positive subjective questionnaire result | Kashan University support; Ahura manufacture/coding reported; paid/donated status unknown | Assessors unblinded; original abstract and selected passages available, complete numerical/safety tables not recovered |
| Postpartum sleep | Chang and Chen 2016: 80 recruited; two-week tea versus usual care; immediate subscale findings absent at four-week post-test | National Science Council grant in primary metadata; complete procurement/COI unknown | Original abstract available; full methods/tables not recovered. Does not establish general insomnia treatment or infant safety |
| Tea for primary insomnia | Khalid 2025: 90 people, eight weeks; chamomile versus passionflower and a control labelled green tea | Flowers purchased; project financing unreported; no conflicts declared | Allocation/blinding unclear; nonstandard sleep scoring and inconsistent control/medication descriptions |
| Mild-to-moderate generalized anxiety | Amsterdam 2009: 57 randomized; eight-week positive primary anxiety score, secondary outcomes not significant | NIH grant; Spectrum preparation; procurement unknown; some authors disclose other pharmaceutical ties | Preliminary signal, not strict conflict-cleared replication |
| Anxiety relapse prevention | Mao 2016: 93 responders randomized; primary relapse result not significant | NIH support; Swedish Herbal Institute provided extract; paid/donated status unknown | Two positive and two nonsignificant secondary scales; relapse-related missing data may bias secondary estimates |
| Postpartum depression symptoms | Eradi 2024: 144 recruited, 128 in final tables; favorable final symptom scores | University reportedly covered all expenses; capsules purchased; no conflicts declared | Preliminary university-supported result; attrition inconsistency and symptom-score design limit clinical interpretation |
What chamomile is
German chamomile is described as Matricaria recutita, Matricaria chamomilla or Chamomilla recutita. Roman chamomile, Chamaemelum nobile, is a different plant. The German chamomile flower is the focus of most studies discussed here. The common name alone does not verify that a commercial product matches it. NCCIH overview
Its flower preparations contain multiple constituents, including flavonoids such as apigenin-related compounds. Extraction solvent, plant material and manufacturing process affect the resulting preparation. A milligram figure without an extract description gives incomplete information about exposure. The regulated botanical identity and range of preparations are described in the EMA matricaria-flower assessment overview.
Forms and grades
| Form | What to check | Limit of transferring evidence |
|---|---|---|
| German chamomile flower tea | Species, single ingredient versus blend, amount of flower and preparation | A brewed drink is not a dose-equivalent substitute for trial extracts |
| Standardized dry extract | Extraction ratio/solvent and the measured chemical marker | Standardization improves identity and consistency; it does not prove efficacy |
| SHC-1 extract | Specific product used in the long-term anxiety program | Results belong to that preparation and selected patients |
| Essential oil | Intended route and product-specific instructions | Inhalation findings do not demonstrate oral efficacy; do not swallow aromatherapy oil |
| Isolated apigenin | A separate chemical intervention | Chamomile trials cannot establish an effective isolated-apigenin dose |
| Multi-ingredient sleep blend | Every active ingredient and its quantity | Any effect cannot automatically be assigned to chamomile |
The 2016 anxiety paper describes SHC-1 as a dry extract standardized to apigenin-7-glycosides. That is more specific than simply claiming “1.2% apigenin.” It also contains a carrier. Extract weight, raw-flower equivalent and isolated chemical dose should not be collapsed into one number. Mao trial methods
How it might work
Laboratory studies have investigated interactions between apigenin and benzodiazepine-associated receptor sites. That supports a research hypothesis, not proof that drinking tea reproduces a prescription sedative's clinical effect. Findings are also more complicated than the popular phrase “boosts GABA”: an early study reported receptor binding and anxiolytic-like animal behavior, while a later experiment found different electrophysiological and behavioral effects. Viola 1995, Avallone 2000
To establish a human mechanism, researchers would need to connect a defined oral preparation to achievable exposure, a relevant biological change and a meaningful clinical outcome. The existing animal and receptor results do not complete that chain. Nor does a change in a cortisol sample establish that an illness was treated or that the body's stress system was “reset.”
Hype versus evidence
| Common claim | What can actually be said |
|---|---|
| “Clinically proven to cure insomnia” | The small publicly funded placebo pilot did not demonstrate sleep benefit; the broader subjective literature is heterogeneous (Original pilot; Review). |
| “Natural benzodiazepine” | A receptor-binding hypothesis does not establish equivalent effectiveness, dosing or safety |
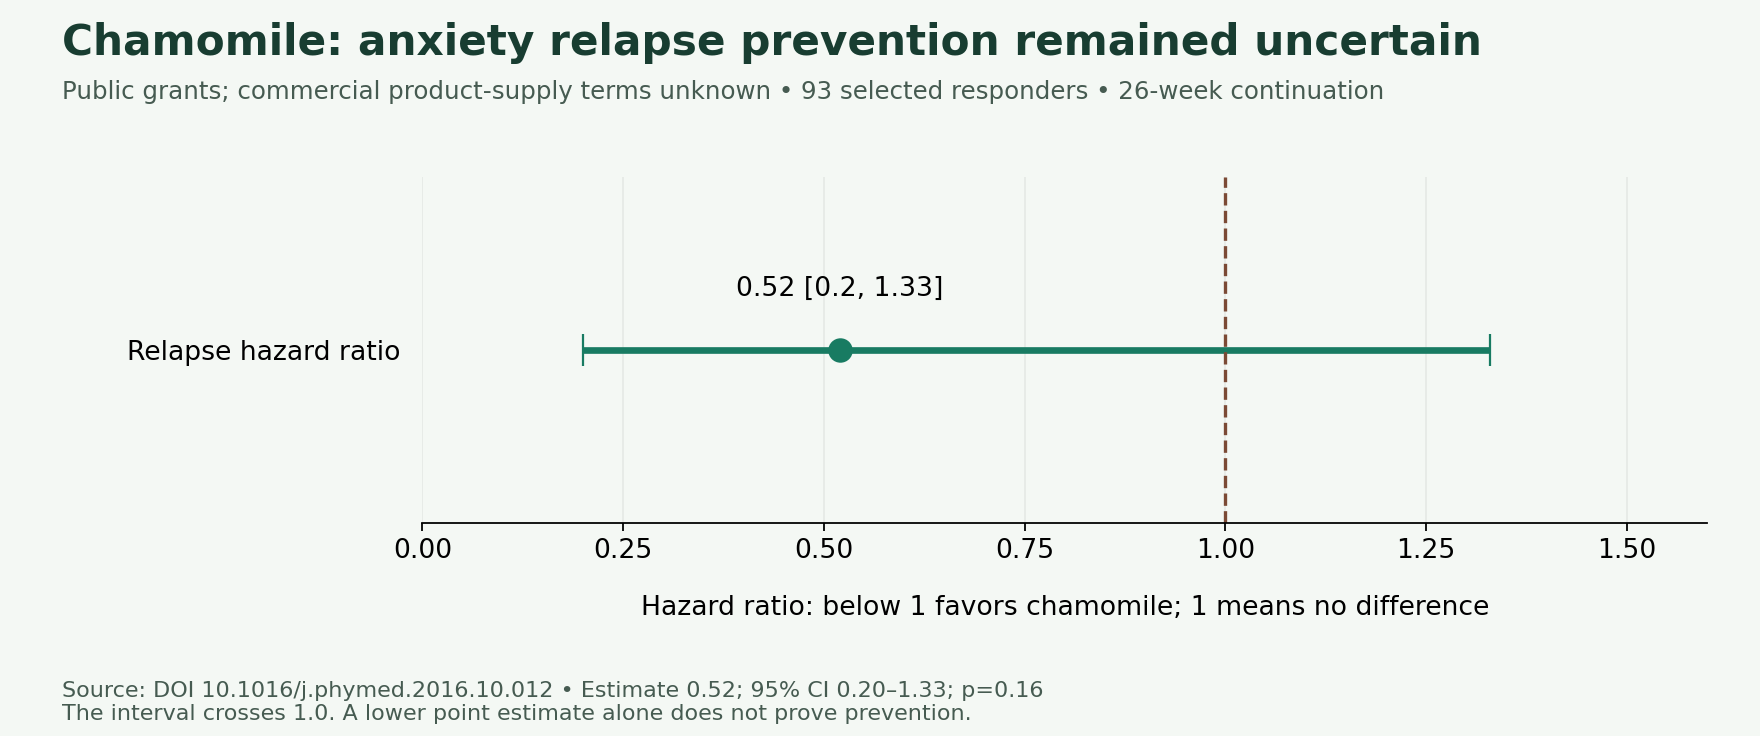
| “Halves anxiety relapse” | The long-term trial's hazard-ratio estimate was imprecise and not statistically significant |
| “NIH-funded means free of commercial influence” | Public funding does not answer whether study product was donated or authors had outside ties |
| “Apigenin content tells you the effective dose” | Different chemical forms, extracts and absorption make this unsupported |
| “Safe because it is tea” | Food use does not eliminate severe allergy or possible medicine interactions |
| “A positive postpartum study proves it is safe while breastfeeding” | A maternal symptom trial cannot establish infant exposure or safety |
Benefits by claim
Chronic insomnia: a publicly funded pilot did not demonstrate benefit
The Michigan study used 270 mg of extract twice daily for 28 days in 34 adults. Sleep diaries did not show significant between-group changes in total sleep time, efficiency, latency, time awake after sleep onset, perceived quality or awakenings. Exploratory effects varied in direction, with total sleep time favoring placebo. The paper explicitly excludes manufacturer financial or drug contribution. Its narrative and tables disagree on several p-values, including adverse-event comparisons; the sleep results remain nonsignificant, but exact statistical and safety claims need caution. Zick 2011; Full original.
A small negative trial does not prove that no person can benefit. It does mean the study should not be advertised as demonstrated efficacy by selecting a favorable, nonsignificant exploratory outcome. A pleasant bedtime ritual remains a personal experience, not a substitute for diagnosing persistent sleep problems. For chronic insomnia, cognitive behavioral therapy for insomnia is a first treatment option supported in NHLBI guidance.
Broader sleep quality: a positive pooled result with substantial uncertainty
The 2024 review reported an average PSQI reduction of 1.88 points versus control, with a 95% confidence interval of 0.31 to 3.46 points in favor of chamomile. Heterogeneity was high, I² 88.4%. The authors identified high risk of bias in most included studies, and only one study checked both product quality and whether blinding worked. Sleep duration, efficiency and daytime functioning were not consistently improved. Kazemi 2024
The review’s heterogeneous subjective score cannot predict deep sleep, extra minutes or durable insomnia recovery for an individual buyer. It declares no specific grant and no known competing interests; that is not proof that all review support or every underlying trial’s finances and procurement were conflict-free (Review declarations).
The Iranian older-adult trial’s abstract reports better self-rated sleep; selected original passages state the physician and interviewing nurse knew allocation. Complete numerical and safety tables were not recovered. The Taiwanese postpartum study’s abstract reports immediate sleep-subscale and depression differences after two weeks of tea versus usual care, absent at its four-week post-test. Its full methods, tables and procurement/COI statements were not recovered. These finite findings do not establish a general insomnia treatment. Adib-Hajbaghery 2017; Chang and Chen 2016.
The newer tea comparison does not settle the question
The eight-week 2025 study labels its control “green tea” in Table 1 but describes no active therapy elsewhere. Random sequence generation, concealment and blinding are unexplained. It calls several 1–10 ratings “PSQI” and excludes medication users while reporting medication-use scores. Flowers were purchased; project financing was unreported. These inconsistencies limit causal interpretation. Khalid 2025.
Those uncertainties prevent treating its large reported differences as reliable confirmation, or its biomarker findings as proof of liver protection or restored hormonal balance. They are methodological reservations, not evidence of misconduct. This is also why newer publication dates alone do not determine which evidence should carry most weight.
Generalized anxiety: encouraging early results, incomplete confirmation
The 2009 trial found a greater reduction in its primary clinician-rated anxiety score with chamomile, with p=0.047. Secondary outcomes were not significant. It was publicly funded, but the supplied preparation's procurement terms were not established, and some authors disclosed research or consulting relationships with other pharmaceutical firms. Amsterdam 2009
That warrants a preliminary signal, not an independently established treatment effect. Generalized anxiety disorder is also different from transient everyday stress: a result in one selected clinical group cannot support every “calm,” “cortisol” or resilience claim.
In the continuation trial, relapse occurred in 7 of 46 people continuing chamomile and 12 of 47 switched to placebo. The hazard ratio was 0.52 (95% CI 0.20–1.33; p=0.16), so relapse prevention was not demonstrated. Secondary GAD-7 symptoms and psychological well-being favored continuation; Hamilton and Beck anxiety scales did not differ significantly. Mao 2016; Full original.
Only people who responded during 12 weeks of open-label treatment were randomized. The result does not estimate starting chamomile in everyone with anxiety. Participants left follow-up after relapse, creating unequal missing data that the authors warn could bias secondary scores. The imprecise primary result and these secondary-analysis limits preclude a reliable “halves relapse” claim (Trial design and limitations).
Postpartum mood symptoms: a university-supported trial remains preliminary
The 2024 postpartum trial’s final depression scores were 18.00 versus 20.09: a 2.09-point unadjusted difference. Published baseline means give a descriptive difference in improvement of about 1.39 points; this calculation is not a separately tested treatment estimate. Table 2’s p=0.002 compares final scores. The university reportedly paid all expenses and capsules were purchased. Eradi 2024.
However, the reported dropout text does not reconcile with 144 recruited and 128 analyzed; the final tables include 63 and 65 women. The study relied on a symptom questionnaire, excluded severe depression and current depression medication, and did not establish infant safety or sustained recovery. These are substantial limits on using the result for care decisions. It does not justify replacing established treatment or delaying assessment of postpartum depression.
What works, and how confident are we?
| Use | Verdict | Confidence and reason |
|---|---|---|
| Treating chronic insomnia | Insufficient | Low confidence in benefit; small pilot did not demonstrate efficacy and the broader literature is heterogeneous (Pilot; Review). |
| Improving subjective sleep in selected groups | Possible signal | Low confidence; mixed preparations/populations, high heterogeneity and mostly high risk of bias (Review). |
| Treating generalized anxiety disorder | Preliminary, not established | Low confidence; one small positive early trial, indirect pharmaceutical author ties and unresolved product procurement (Original trial). |
| Preventing anxiety relapse | Not demonstrated | Primary result inconclusive; selected responders and differential missing data limit secondary findings (Original trial). |
| Postpartum mood symptoms | Preliminary university-supported signal | Low confidence; purchased-product trial with modest score differences, attrition inconsistency and no infant-safety assessment (Original trial). |
| Reducing everyday stress or cortisol | Insufficient | No robust, broadly applicable clinical benefit established here |
| Replacing antidepressants, benzodiazepines or insomnia care | Unsupported | No reliable general equivalence or substitution evidence |
Reported public support and product purchases are useful financial evidence, not a guarantee that all institutional donors, supply terms or author relationships have been discovered. Methodological confidence is assessed separately; a transparent funding statement cannot remove small samples, bias or inconclusive results.
Risks and adverse effects
| Risk | What is known | Practical implication |
|---|---|---|
| Allergy, including serious reactions | Severe reactions are reported; medicinal preparations must not be used with known chamomile or other Asteraceae allergy (NCCIH; EMA). | Sudden throat/tongue swelling or breathing difficulty needs emergency help (Emergency allergy guidance). |
| Nausea or dizziness | Reported possible effects (NCCIH). | Follow the exact product label and seek professional advice for troublesome symptoms (Label guidance; Provider review). |
| Long-term concentrated-extract exposure | The anxiety continuation trial studied selected responders, with mild reported events (Original trial). | A small selected trial cannot establish universal long-term safety or exclude rare harms |
| Pregnancy and breastfeeding | Reliable safety information is limited (NCCIH). | Discuss medicinal use with the maternity clinician; maternal symptom trials do not establish infant safety |
| Product variability | Species, preparations and routes differ (EMA). | Check the exact product identity and instructions; trial results do not certify an unrelated preparation |
| Persistent illness | Long-term insomnia needs assessment and established care (NHLBI). | Seek qualified assessment for ongoing sleep or significant mood symptoms; these botanical trials are not treatment-substitution evidence |
The allergy and general safety cautions follow NCCIH and the EMA botanical assessment. Short studies with few participants cannot reliably detect rare adverse events.
Medication and supplement interactions
| Combination | Evidence level | Interpretation |
|---|---|---|
| Warfarin | One bleeding case followed increased tea and topical chamomile use during illness (Original case). | Important warning signal; one case cannot prove causality or quantify incidence |
| Sedatives and sleep medicines | NCCIH identifies a theoretical sedative-interaction concern (NCCIH). | Ask the clinician/pharmacist about the exact combination; direct controlled risk estimates are not established |
| Medicines metabolized by the liver | NCCIH reports possible interactions with selected liver-metabolized medicines (NCCIH). | Review the exact medicine; a general CYP hypothesis cannot predict an individual interaction’s magnitude or direction |
| Hormonal contraception or hormone-sensitive conditions | NCCIH flags preliminary estrogen-related concerns (NCCIH). | Clinical significance is uncertain; discuss medicinal use rather than changing prescribed treatment yourself |
| Other calming herbal blends | Combination products differ from the single-botanical preparations discussed here (EMA preparation scope). | Review all ingredients and labels; this article’s chamomile trials do not establish combination efficacy or safety |
The warfarin report concerned a 70-year-old woman with increased INR and internal bleeding following greater use of tea and lotion during an illness. She was also taking other medicines, including amiodarone. This supports caution, but does not prove that every cup causes bleeding or that all naturally occurring coumarins act like warfarin. Segal and Pilote 2006
The broader interaction and hormone cautions are based on NCCIH's safety summary. Their level of certainty is lower than a quantified interaction demonstrated in a well-controlled human experiment.
Who should avoid it or seek advice first?
- Avoid medicinal chamomile with known chamomile or other Asteraceae allergy; seek clinical advice if allergy status is uncertain (EMA allergy restriction).
- People taking warfarin or other medicines with a narrow safety margin need an individualized medicine review
- Pregnant or breastfeeding people should not assume that a medicinal extract is safe because tea is familiar
- Children should not receive an adult sleep or anxiety extract dose based on these studies
- People with hormone-sensitive conditions or using hormonal treatment should discuss medicinal use with their clinician
- People with persistent insomnia, significant depression, disabling anxiety or new concerning symptoms need assessment rather than relying on a supplement
These precautions reflect the evidence gaps and NCCIH safety information; they are not a claim that all these populations have demonstrated injury from chamomile.
Doses used in research
These are research exposures, not a personal dosing recommendation or an established safe upper limit. Different preparations cannot be substituted milligram for milligram.
| Study | Preparation and exposure | Duration and context |
|---|---|---|
| Zick 2011 | 270 mg dry extract twice daily, 540 mg/day | 28 days; 34 adults with chronic primary insomnia |
| Adib-Hajbaghery 2017 | 200 mg extract twice daily, 400 mg/day | 28 days; selected older adults; complete original tables unavailable |
| Amsterdam 2009 | 220 mg extract capsules; one daily initially, response-based escalation up to five daily | Eight weeks; mild-to-moderate generalized anxiety |
| Mao 2016 | 500 mg SHC-1 capsule three times daily, 1,500 mg/day | 12-week open-label phase, then 26-week randomized continuation in responders |
| Eradi 2024 | 500 mg chamomile capsule twice daily | Eight weeks; selected postpartum women with mild/moderate symptom scores |
| Khalid 2025 | Tea from 1 g flower powder daily | Eight weeks; unclear allocation/control and nonstandard outcome reporting |
Sources: Zick, Adib-Hajbaghery, Amsterdam, Mao, Eradi, Khalid.
No extract-to-tea or chamomile-to-apigenin conversion is endorsed. A study protocol does not establish that taking more improves the result.
Animal and laboratory evidence: separate from clinical benefit
The original abstracts describe apigenin receptor binding and animal behavior in Viola 1995, and cultured-cell electrophysiology plus injected rats in Avallone 2000. The latter did not find anxiolytic activity in its rat tests. Full original methods, numerical results and financial/procurement disclosures were not recovered. These finite abstract findings support laboratory context only. Viola abstract; Avallone abstract.
Neither experiment tests a typical cup of tea in a person with chronic insomnia. Receptor affinity, reduced animal movement and human restorative sleep are different outcomes. This article therefore does not convert animal doses to consumer doses, treat sedation as proof of healthy sleep, or infer treatment of neurological disease from laboratory activity.
Funding, institutions and commercial interests
Research funding at a glance
21 disclosure entries. The counts below summarize independence tiers explicitly assigned in this article. They count disclosures, not studies, funding amounts or evidence quality.
Consult this article’s source and funding notes for named funders, countries, relationships and exceptions where available. Institutional backing, researcher interests and trial sponsorship are separate questions. Public funding alone does not establish independence; commercial ties alone do not prove a claim false. This overview is not a new financial audit.
What the funding trail changes
Zick reports university/NIH grants and explicitly denies manufacturer money or drug contribution. A named manufacturer does not by itself establish sponsorship. Conversely, Mao says the Swedish Herbal Institute provided extract without specifying purchase or donation. Those statements document different relationships; they do not resolve every institutional donor or transaction. Zick declarations; Mao acknowledgments.
Eradi states that capsules were purchased and the university paid all expenses. That adds procurement information beyond a generic no-conflict declaration, but does not correct the trial’s reporting weaknesses. Amsterdam reports public funding alongside outside pharmaceutical author relationships and unspecified Spectrum procurement. Neither public funding nor a no-conflict declaration is a complete financial audit. Eradi declarations; Amsterdam disclosures.
Documented relationship map

- US NIH and University of Michigan support → Zick insomnia pilot; MediHerb is the named Australian manufacturer; the paper explicitly denies manufacturer financial/drug contribution (Original declarations).
- US NIH support → University of Pennsylvania anxiety research; this is research funding, not NIH treatment approval (2009 support; 2016 support).
- Swedish Herbal Institute, Sweden → processed, produced and provided the later anxiety extract; paid/donated status unknown (Original supply statement).
- Kashan University, Iran → older-adult sleep study; Ahura, Iran → capsule manufacture/coding; commercial terms unknown (Original abstract and selected passages).
- Taiwan National Science Council → postpartum tea study; original full procurement/COI unknown (Primary grant metadata).
- Ahvaz Jundishapur University, Iran → reportedly all postpartum-trial expenses; Adonis Gol Daru capsules explicitly purchased (Original declarations).
- Lahore market, Pakistan → flowers purchased for the 2025 tea comparison; project financing unreported (Original methods).
These links come from the primary papers above. Company names identify documented relationships; they do not imply misconduct or common ownership.
Who is behind the sources and products?
The Swedish Herbal Institute's own contact page identifies Swedish Herbal Institute AB in Vallberga, Sweden, and calls it a pharmaceutical company. Its commercial site markets herbal products. Its name should not be mistaken for a public research agency. Ultimate ownership percentages and the financial terms of trial supply were not established.
MediHerb's company history identifies Australian origins. Integria's current brand page includes MediHerb. That commercial relationship does not override the insomnia paper's explicit denial of manufacturer support. Current ultimate beneficial ownership, exact study payments and historical ownership at the trial date are not asserted here.
NCCIH’s official budget history documents Congressional appropriations; NHLBI provides NIH clinical education. These pages do not audit each underlying researcher’s institutional donors. EMA is an EU regulator in the Netherlands, with public and regulatory-fee income documented in its 2026 budget. Agency financing is separate from the financial relationships in individual trials.
Regulation and quality
In the United States, a chamomile dietary supplement is not FDA-approved before sale as a treatment for insomnia or anxiety. A research investigational-new-drug permission allows a study to proceed; it is not marketing approval demonstrating that the product treats the disorder. NCCIH regulation summary
The EMA matricaria-flower overview describes traditional uses for specified gastrointestinal, mouth/throat, cold and skin complaints. It does not provide a general insomnia or anxiety approval. Traditional-use recognition also has a different evidentiary basis from demonstrated efficacy in modern randomized trials. National product authorization and the exact label still matter. EMA assessment
A quality certificate or standardized marker can help establish what was manufactured. It cannot establish that a particular person will sleep better. Product selection should distinguish species, route, extract characteristics and additional ingredients rather than relying on a “natural sleep” label.
Frequently asked questions
Does chamomile tea actually help sleep?
Several studies report better subjective sleep, but the heterogeneous evidence does not establish a reliable chronic-insomnia treatment. The small publicly funded placebo pilot found no significant sleep benefit (Pilot; Review).
Is chamomile better for anxiety than for sleep?
The early anxiety result is promising, but the clinical program is too limited to make a confident comparison. The main relapse-prevention result was inconclusive.
Is chamomile the same as apigenin?
No. Apigenin is one constituent-related research topic within a complex botanical. A chamomile extract trial does not validate a purified apigenin supplement or its dose.
Can I use it instead of an antidepressant or sleeping medicine?
The evidence does not support substituting chamomile for prescribed treatment. Treatment changes should be discussed with the clinician managing the condition.
Is it safe with warfarin?
A serious bleeding case has been reported. Have the anticoagulation clinician or pharmacist review use; do not change warfarin yourself.
Does a postpartum trial mean it is safe while breastfeeding?
No. Symptom outcomes in mothers do not establish the safety of infant exposure through milk. Concentrated medicinal use deserves a specific review.
How long does it take to work?
Trials generally assessed repeated use over weeks. They do not establish a dependable immediate sedative effect or an optimal duration.
Does public funding settle the credibility question?
No. Funding, product procurement, employer ties, study design and reporting must all be checked. Publicly funded studies can provide weak evidence, and manufacturer-linked findings can be accurately reported without being counted as independent confirmation.
Sources and funding notes
The scorecard covers the sources used here. Tier 1 is a provisional classification from available noncommercial disclosures; Tier 2 indicates indirect ties; Tier 3 a material interested-party stake; Tier 4 a maker or seller source. U means unresolved information. Grades A–D are editorial judgments about fitness for the stated use. Neither a tier nor a no-conflict declaration certifies every donor, financial relationship or study method.
| Source | Country, funding and relationships | Tier / grade; use and limits |
|---|---|---|
| Zick 2011; full original | US Michigan authors; university seed funding and NIH UL1RR024986; no conflicts declared; explicit denial of MediHerb financial/drug contribution | 1 provisional / B; small diary-based pilot; no sleep benefit demonstrated; internal p-value conflicts, especially safety reporting |
| Kazemi 2024 | Iranian Shiraz academic authors; no specific grant and no known competing interests declared; underlying trial finances/procurement not uniformly established | U / B; complete relevant review read; heterogeneous subjective synthesis and inconsistent risk-tool caption; declaration is not complete finance clearance |
| Adib-Hajbaghery 2017 | Iranian Kashan authors/support; Ahura manufacture/coding, paid/donated status unknown; no conflicts declared in original indexed passages | U / C; original abstract and selected methods/disclosures read, full numerical/safety tables inaccessible; assessors unblinded |
| Chang and Chen 2016; grant metadata | Taiwan investigators; National Science Council NSC 99-2628-B-006-035; full COI/tea procurement unknown | U / C; abstract plus primary grant record; full methods/tables inaccessible; usual-care comparison and short-lived subscale findings |
| Khalid 2025 | Academic/clinical authors in Pakistan, Uganda and UK; flowers purchased; project financing unreported; no conflicts declared | U / C; full relevant original text read; control, instrument, allocation and medication-use reporting problems |
| Amsterdam 2009; original manuscript | US Penn authors; NIH AT001916; Spectrum procurement unknown; Amsterdam disclosed Lilly/Sanofi/Novartis grants, Rockwell Elan consulting | 2 + U / B; indirect outside pharmaceutical ties, not established maker sponsorship; small positive primary trial |
| Mao 2016; original manuscript | US Penn/MSK authors; NIH R01 AT005074 and P30 CA008748; Swedish Herbal Institute provided extract, paid/donated status unknown; no conflicts declared | U / B; selected responders; primary relapse inconclusive; mixed secondary scales and differential missing-data bias |
| Eradi 2024 | Iranian Ahvaz Jundishapur University reportedly paid all expenses; Adonis Gol Daru capsules purchased; no conflicts declared | 1 provisional / C; modest symptom-score contrast and attrition inconsistency; no infant-safety or sustained-recovery finding |
| Viola 1995 | Argentina/Buenos Aires affiliation; complete financing/employer/procurement disclosures inaccessible | U / C; original abstract only; receptor/mouse context, no human sleep efficacy |
| Avallone 2000 | Italian academic pharmacology affiliation; complete financing/COI/procurement inaccessible | U / C; original abstract only; cells/injected rats, no human oral-dose inference |
| Segal and Pilote 2006 | McGill hospital clinicians, Canada; no competing interests declared; specific funding not stated; no supplied intervention | U / B for signal, C for causality; one spontaneous clinical case |
| NCCIH chamomile | US NIH public health-information body; appropriations; underlying cited literature varies | 1 / A for safety overview; not a new clinical trial |
| NCCIH budget | US government primary financial information | 1 / A; institutional funding provenance only |
| NHLBI insomnia treatment | US NIH public clinical education; government support | 1 / A; established-care context, not chamomile efficacy |
| EMA matricaria-flower assessment | EU agency, Netherlands; public and regulatory-fee income; product literature may include commercial studies | 2 / A for regulatory scope; traditional use does not prove sleep efficacy |
| EMA finance | EU regulator's own financial disclosure | 2 / A; funding structure only |
| Swedish Herbal Institute contact | Swedish pharmaceutical company; product-sales interest; ownership percentages unknown | 4 / B for entity/location, D for efficacy; primary self-identification |
| Swedish Herbal Institute products | Same Swedish commercial business; markets herbal products | 4 / C; commercial role only, promotional benefit claims excluded |
| MediHerb history | Australian herbal-product brand; product-sales interest | 4 / B for identity, D for efficacy; no independent quality/benefit endorsement |
| Integria history/brands | Australian commercial healthcare group/brand page; product revenue; ultimate owners not established here | 4 / B for brand association, D for efficacy |
| NHS anaphylaxis guidance | UK public clinical guidance; institutional funding chain not separately audited here | U / B for emergency recognition and actions; not chamomile efficacy evidence |
Peer review, transparent reporting and public accountability give these sources incentives to be accurate; publication incentives, commercial sales and incomplete disclosures remain concerns. Adib and Chang have incomplete original-paper access, and the older laboratory studies were assessed from abstracts. Reported grants and product purchases are documented above; undisclosed financing, supply terms and ownership remain unknown.
This article is informational and does not replace qualified clinical assessment. Research exposures are not personal dosing instructions. Source-specific financial declarations and access limits do not establish universal safety or treatment efficacy.
Have a question — or want us to cover something?
Ask about anything on this page, or request the next deep dive: an ingredient, a supplement, or a health concern. We use published research, evidence syntheses, and regulatory guidance, with clear source links.
One daily research roundup
Get the topics, key findings and links from our new articles in one email. At most one digest a day, only when there is something new.