
Key takeaways
- Enteric-coated peppermint oil has a short-term IBS symptom signal in pooled trials, but the certainty is low and newer trials have not consistently confirmed it
- This article's stricter independent-funding screen does not establish a dependable benefit for a particular retail product
- Peppermint oil, peppermint tea, isolated menthol and peppermint–caraway combinations have different evidence
- Reflux and heartburn can worsen. An enteric coating reduces early release; it does not guarantee freedom from side effects
- A large 2026 pediatric trial found no advantage over its comparator. Adult results should not be turned into a children's self-treatment recommendation
Peppermint oil is a plausible antispasmodic with genuine clinical research behind it. The most defensible conclusion is a possible short-term benefit for selected adults with IBS, with substantial uncertainty about size, formulation and independence. Confidence is moderate that the overall clinical literature contains a symptom-relief signal, but low that the funding-screened evidence establishes a reliable treatment benefit. It has no established role as a gut-healing, antimicrobial or reflux cure.
Contents
Evidence summary · What it is · Forms · Mechanism · Hype · Benefits · Verdicts · Risks · Interactions · Who should avoid · Studied doses · Laboratory evidence · Funding · Regulation · FAQs · Sources
Evidence summary
A favorable result and an independently established result are different judgments. Commercially supported studies remain visible below, including null results, but do not determine the independent benefit grade. Missing disclosure is recorded as unknown.
| Claim | Evidence | Source | Funding/conflict | Strength |
|---|---|---|---|---|
| Relieves adult IBS symptoms | Pooled benefit, with very low certainty and more adverse events | Ingrosso 2022 | Mixed underlying trial provenance; full review disclosures not retrieved | Possible benefit; insufficient independent estimate |
| Improves IBS compared with placebo in a modern US trial | No significant primary or secondary advantage | Nee 2021 | NIH funding verified; full final disclosure and procurement terms unresolved | Important null trial; not proof of universal inefficacy |
| Improves modern IBS responder endpoints | Both tested release formulations missed primary endpoints; some small-intestinal-release secondary results favored oil | Weerts 2020 | Public grant plus explicit in-kind capsules, commercial collaboration and licensing interests | Excluded from independent benefit basis |
| Helps children with IBS or functional abdominal pain | No superiority in a 228-child trial | Vermeijden 2026 | Charity support; manufacturer provision with payment terms unknown; indirect author ties | Does not establish pediatric benefit |
| Treats functional dyspepsia by itself | Combination research cannot isolate peppermint oil | Chey 2019 | IM HealthScience funding and author ties | Insufficient for oil alone |
| Raises some medicine exposure | Small human felodipine experiment; cyclosporine finding is from rats | Dresser 2002; Wacher 2002 | AvMax affiliations; complete financing unresolved | Limited interaction signal, not a universal drug-interaction rule |
What it is
Peppermint, Mentha × piperita, is a hybrid of water mint and spearmint. Its essential oil is a concentrated preparation obtained from the plant's aerial material, including leaves and flowering parts. Menthol is an important constituent, but the oil contains multiple compounds. Leaf tea, an oil capsule and isolated menthol are not dose-equivalent preparations. NCCIH ingredient overview
This article concerns swallowed preparations and digestive claims. Aromatherapy for nausea, topical treatment, dental products and clinician-administered endoscopic preparations require separate evidence. A procedural antispasmodic effect cannot establish that a retail capsule improves a chronic digestive disorder.
Forms and grades
| Form | Important distinction | What to check |
|---|---|---|
| Gastro-resistant or enteric-coated capsules | Coating delays exposure until after the stomach | Exact release system, amount per capsule and instructions |
| Small-intestinal-release microspheres | A proprietary delivery system can differ from a conventional capsule | Evidence for that complete formulation |
| Ileocolonic-release capsules | Intended delivery farther down the bowel | This formulation did not outperform placebo on the main endpoints in Weerts' trial |
| Uncoated oil or essential-oil drops | Concentrated oil can contact the mouth, oesophagus and stomach directly | Do not improvise an oral dose from an aromatherapy bottle |
| Peppermint tea or leaf extract | Different composition and exposure | Capsule findings do not establish equivalent effectiveness |
| Isolated menthol or peppermint plus caraway | Another molecule or a combination intervention | Attribute findings to the studied intervention |
Release location is part of the treatment, not a cosmetic feature. “Natural,” “ultrapurified” or “clinical strength” does not show independent clinical superiority. The examined products include a UK-authorized 0.2 mL capsule and proprietary US supplements; regulatory status and excipients differ. Colpermin product information, IBgard manufacturer page
How it works
The central rationale is relaxation of gastrointestinal smooth muscle. Laboratory pharmacology implicates calcium-dependent contraction, while menthol-sensitive sensory pathways are also being investigated. Enteric coatings aim to deliver the oil farther down the digestive tract. These mechanisms make an antispasmodic effect plausible; they do not tell us the size or durability of pain relief in everyday IBS. NHS mechanism explanation, regulated product pharmacology
IBS symptoms fluctuate, and participants can improve with reassurance, follow-up, background treatment or placebo. Consequently, a before-and-after improvement is less informative than the difference from a well-matched control. The NIH-supported peppermint study was nested within a placebo-research program, making that distinction particularly relevant. Ballou protocol
Hype versus evidence
The reasonable claim is limited symptom relief in a defined setting. Claims that peppermint repairs the intestinal barrier, eliminates SIBO, restores a microbiome, treats inflammatory bowel disease or cures every kind of bloating go beyond the human outcomes reviewed here. Laboratory antimicrobial activity would not establish eradication of a diagnosed infection, and pain relief would not demonstrate mucosal healing.
The American College of Gastroenterology's 2021 guideline conditionally suggested peppermint for global IBS symptoms using low-quality evidence. That is a treatment option within clinical care, not a guarantee of benefit or a finding that all underlying studies were commercially independent. ACG guideline
A manufacturer currently promotes targeted delivery and rapid abdominal comfort. Those statements identify what is being marketed; they do not supply independent corroboration. Manufacturer's claim
Benefits by claim
Adult IBS pain and global symptoms Insufficient independent evidence
The 2022 synthesis included 10 randomized trials and 1,030 participants. Its pooled relative risk of failing to improve was 0.65 for global symptoms and 0.76 for pain. However, the confidence interval for the global-symptom number needed to treat was extremely wide, and the authors rated the evidence very low quality. The pool is not a set of independently financed trials. Its favorable direction should be retained without presenting a headline NNT as a precise expectation for an individual. Ingrosso 2022
The US trial reported by Nee tested 180 mg three times daily for six weeks. Mean symptom-severity improvement was 90.8 points with peppermint and 100.3 with placebo, with no significant between-group difference. NIH funding is documented. The protocol identifies Pepogest softgels and a manufactured soybean-oil placebo, but does not resolve whether those products were bought or contributed. The final paper's complete disclosures were inaccessible in this audit. This is therefore a publicly funded trial with a residual provenance gap, rather than a fully cleared independent efficacy result. Nee 2021, protocol, NIH award record
The Dutch PERSUADE trial found no significant advantage on its prespecified abdominal-pain responder or overall-relief endpoints after eight weeks. Small-intestinal-release oil did improve some secondary pain, discomfort and severity measures. Will Pharma supplied capsules in kind, collaborated on the study and had relevant licensing relationships. Public funding does not remove those ties. Weerts 2020 outcomes and disclosures
A smaller, positive four-week trial of a targeted-delivery preparation involved 72 adults with diarrhea-predominant or mixed IBS. It was funded by IM HealthScience; the three authors included a company consultant and company medical/innovation officers. This provides formulation-specific context, not independent confirmation. Cash 2016
Children's IBS and functional abdominal pain Insufficient
In the 2026 multicenter Dutch trial, 228 children aged 8–18 were randomized to peppermint-oil capsules, peppermint sweets or comparator capsules. Treatment success was 44.0% with oil and 37.3% with comparator, a nonsignificant difference; sweets also showed no advantage. Adequate relief did not differ significantly. The comparator contained a small amount of peppermint oil for blinding, so it was not chemically oil-free. The funding statement names SPIN/Cultuurfonds support and products provided by Will Pharma and Fortuin; payment terms are not specified. Keszthelyi disclosed earlier Will Pharma co-funding, and Benninga disclosed several company consultancies. These findings do not justify routine pediatric self-treatment. Vermeijden 2026
Functional dyspepsia and upper abdominal discomfort Insufficient for oil alone
Some dyspepsia research tests caraway oil with peppermint oil or L-menthol. The 2019 FDREST trial, for example, tested a duodenal-release caraway/L-menthol combination, with IM HealthScience funding and extensive company roles. A combination's result cannot identify how much, if any, benefit came from peppermint oil alone. Chey 2019
This distinction also matters clinically: indigestion, reflux and IBS are different symptom patterns. Peppermint can aggravate reflux even when it is being considered for lower-bowel cramps. NCCIH IBS guidance
Gut healing, SIBO eradication and long-term prevention Insufficient
The evidence assessed here does not establish these outcomes. A short symptom trial cannot show prevention of future disease or sustained benefit after discontinuation. This is an evidence boundary, not proof that every untested effect is impossible. Long-term effectiveness remains uncertain in public clinical guidance. NCCIH IBS evidence
What works and what does not
| Claim | Verdict | Notes |
|---|---|---|
| A short-term IBS treatment option for selected adults | Possible benefit, uncertain independent magnitude | Consistent enough for a conditional guideline suggestion; conflicting modern trials and funding gaps remain |
| A proven benefit from any peppermint product | Unsupported | Preparation, population and endpoint differ |
| A reliably effective pediatric treatment | Not established | Recent controlled results were null |
| A reflux remedy | Poor fit | Can worsen heartburn |
| Peppermint tea equals an enteric-coated capsule | Unsupported equivalence | No matching exposure or delivery evidence |
| A microbiome reset or gut-lining repair | Not established | Appropriate clinical outcomes are missing |
Risks and side effects
| Aspect | Finding | Source |
|---|---|---|
| Reflux and irritation | Heartburn, indigestion and anal irritation can occur | NHS safety |
| Aggregate trial adverse events | More frequent with peppermint than placebo in the 2022 synthesis | Ingrosso 2022 |
| Allergy | Peppermint or another capsule ingredient may provoke a reaction | NHS safety |
| Product-specific allergens | The examined UK Colpermin label lists peanut oil and cautions people with peanut or soya allergy | Colpermin label |
| Liver and biliary conditions | EMA's digestive-use summary excludes liver disease, gallstones, other bile-related problems and achlorhydria | EMA public summary |
| Pregnancy and breastfeeding | Data are limited; guidance differs in caution between products and institutions | NHS pregnancy page; product label |
A 2025 case report described liver-enzyme elevations during escalating use of two peppermint-containing supplements, improving after withdrawal. A single case cannot establish incidence or isolate the responsible ingredient in a multi-product exposure. Ali 2025
Safety note: Breathing difficulty, sudden swelling of the mouth or throat, or collapse requires emergency care. Do not experiment with concentrated oil in response to persistent or unexplained abdominal symptoms. New bowel bleeding, persistent vomiting, weight loss or worsening symptoms needs medical assessment. This is a selection of relevant risks, not a complete adverse-event inventory. NHS emergency allergy guidance, NHS suitability guidance
Interactions and important gaps
| Substance or condition | Mechanism or concern | Severity/status | Source |
|---|---|---|---|
| Antacids, PPIs and H2 blockers | Altered gastric conditions can interfere with intended release | Formulation-specific caution; check the actual product and pharmacist's advice | NHS interaction guidance |
| Felodipine | A 12-person experiment using 600 mg oil increased average drug exposure to 140% of the water condition, with wide individual variation | Human pharmacokinetic signal; clinical consequences and usual-capsule relevance uncertain | Dresser 2002 |
| Cyclosporine | Increased exposure in a rat experiment | Preclinical warning, not a verified human interaction magnitude; specialist review is appropriate | Wacher 2002 |
| Other medicines and herbal products | Laboratory metabolic effects do not establish every proposed clinical interaction | Comprehensive testing is absent | NHS evidence gap |
| Alcohol | May worsen dizziness or other adverse effects | Tolerability caution | NHS common questions |
| Existing reflux or hiatus hernia | Symptoms may worsen | A clinically relevant suitability issue | NCCIH IBS guidance |
NHS advice describes a two-hour gap from indigestion medicines. That should not be interpreted as proof that simple spacing neutralizes every effect of a long-acting acid suppressant or makes every release system appropriate. The relevant question is the complete medicine list and the particular capsule, not a universal timing rule. Do not stop prescribed treatment to accommodate a supplement.
Who should avoid self-treatment
People with unexplained or alarm symptoms should first have the cause assessed. Reflux, gallbladder or liver disease, low stomach acid, pregnancy, breastfeeding and relevant allergies warrant individual review. The EMA and individual labels have different age limits; a research protocol is not permission to dose a child. EMA digestive-use restrictions, NHS suitability
A prescribed antispasmodic or an established IBS care plan should not be abandoned because a funding-screened article assigns a low benefit grade. That grade describes what this review can independently establish, not a personal instruction to discontinue care.
Dosage and how it was taken in research
These are study exposures, not dosing recommendations. Different coatings and units are not interchangeable.
| Use case | Studied exposure | Duration | Notes |
|---|---|---|---|
| Adult IBS, US trial | 180 mg three times daily | 6 weeks | No superiority over placebo; Nee |
| Adult IBS, Dutch trial | 182 mg three times daily, with two different release designs | 8 weeks | Primary endpoints null; Weerts |
| Non-constipated adult IBS | 180 mg three times daily in a proprietary microsphere system | 4 weeks | Maker-funded study; Cash |
| Pediatric IBS/functional pain | Age-dependent capsule or sweet protocol with potential escalation | 8 weeks | No proven advantage; not reproduced as home instructions; Vermeijden |
| Drug-interaction experiment | 600 mg oil with felodipine | Acute crossover | Not a therapeutic digestive regimen; Dresser |
Gastro-resistant capsules should be used according to their actual instructions rather than crushed or chewed. Oil released early can irritate the upper digestive tract. Colpermin handling instructions
Animal and in vitro evidence excluded from benefit conclusions
The cyclosporine experiment was conducted in rats and had commercial AvMax authorship. It is retained only to explain a commonly repeated interaction warning and its limits. The human felodipine paper also contains microsomal experiments; those do not prove a clinically important interaction with every medicine processed by the same enzyme. Wacher, Dresser
No animal, cell-culture or isolated-tissue result establishes the IBS benefit grade in this article. Mechanistic plausibility and efficacy are assessed separately.
Independent funding tracing
What the research money shows
The strongest point of this audit is not that all research has the same conflict. It does not. The US program has identifiable NIH financing and a remaining procurement gap. PERSUADE has explicitly documented in-kind commercial support. Cash's trial has direct company funding and company-linked authors. The pediatric funding statement identifies commercial product provision without establishing payment terms; indirect author relationships are disclosed separately. These are distinct evidence categories. NIH/protocol, PERSUADE disclosures, Cash disclosures, pediatric disclosures
An arm's-length product purchase is not sponsorship. An undisclosed procurement arrangement remains unknown. Academic control over analysis is reassuring, but it does not erase manufacturer financing, donated products, commercial authorship or a relevant licensing stake. The same eligibility rule applies to favorable and unfavorable outcomes.
Companies, countries and backers
IM HealthScience, the US sponsor of Cash's trial, later sold its relevant brands to Nestlé Health Science. Nestlé's 2020 announcement and its current IBgard page document that connection. Health Science lists its global headquarters in Vevey, Switzerland. These later ownership facts do not imply that Nestlé financed the earlier trial. Acquisition announcement, current brand and headquarters
Nestlé's 2025 governance report lists notified stakes of 5.04% for BlackRock, 5.547% for UBS Fund Management (Switzerland), and 3.006% for Capital Group. Those figures refer to notifications dated January 2022, May 2024 and January 2025 respectively, not a live October 2026 shareholder register. Investment-manager holdings do not establish control over a particular study. Ultimate fund clients and trial-level decision rights were not traced. 2025 report, significant shareholders
Will Pharma describes itself as a continuing family business with Dutch origins and Belgian operations. Its exact ultimate ownership percentages were not verified from primary filings. The business relationship to the Dutch trial is nevertheless explicit in the paper. Plant origin, oil-production country, capsule manufacturing country and a sponsor's headquarters should not be conflated. Will Pharma history
Documented money map
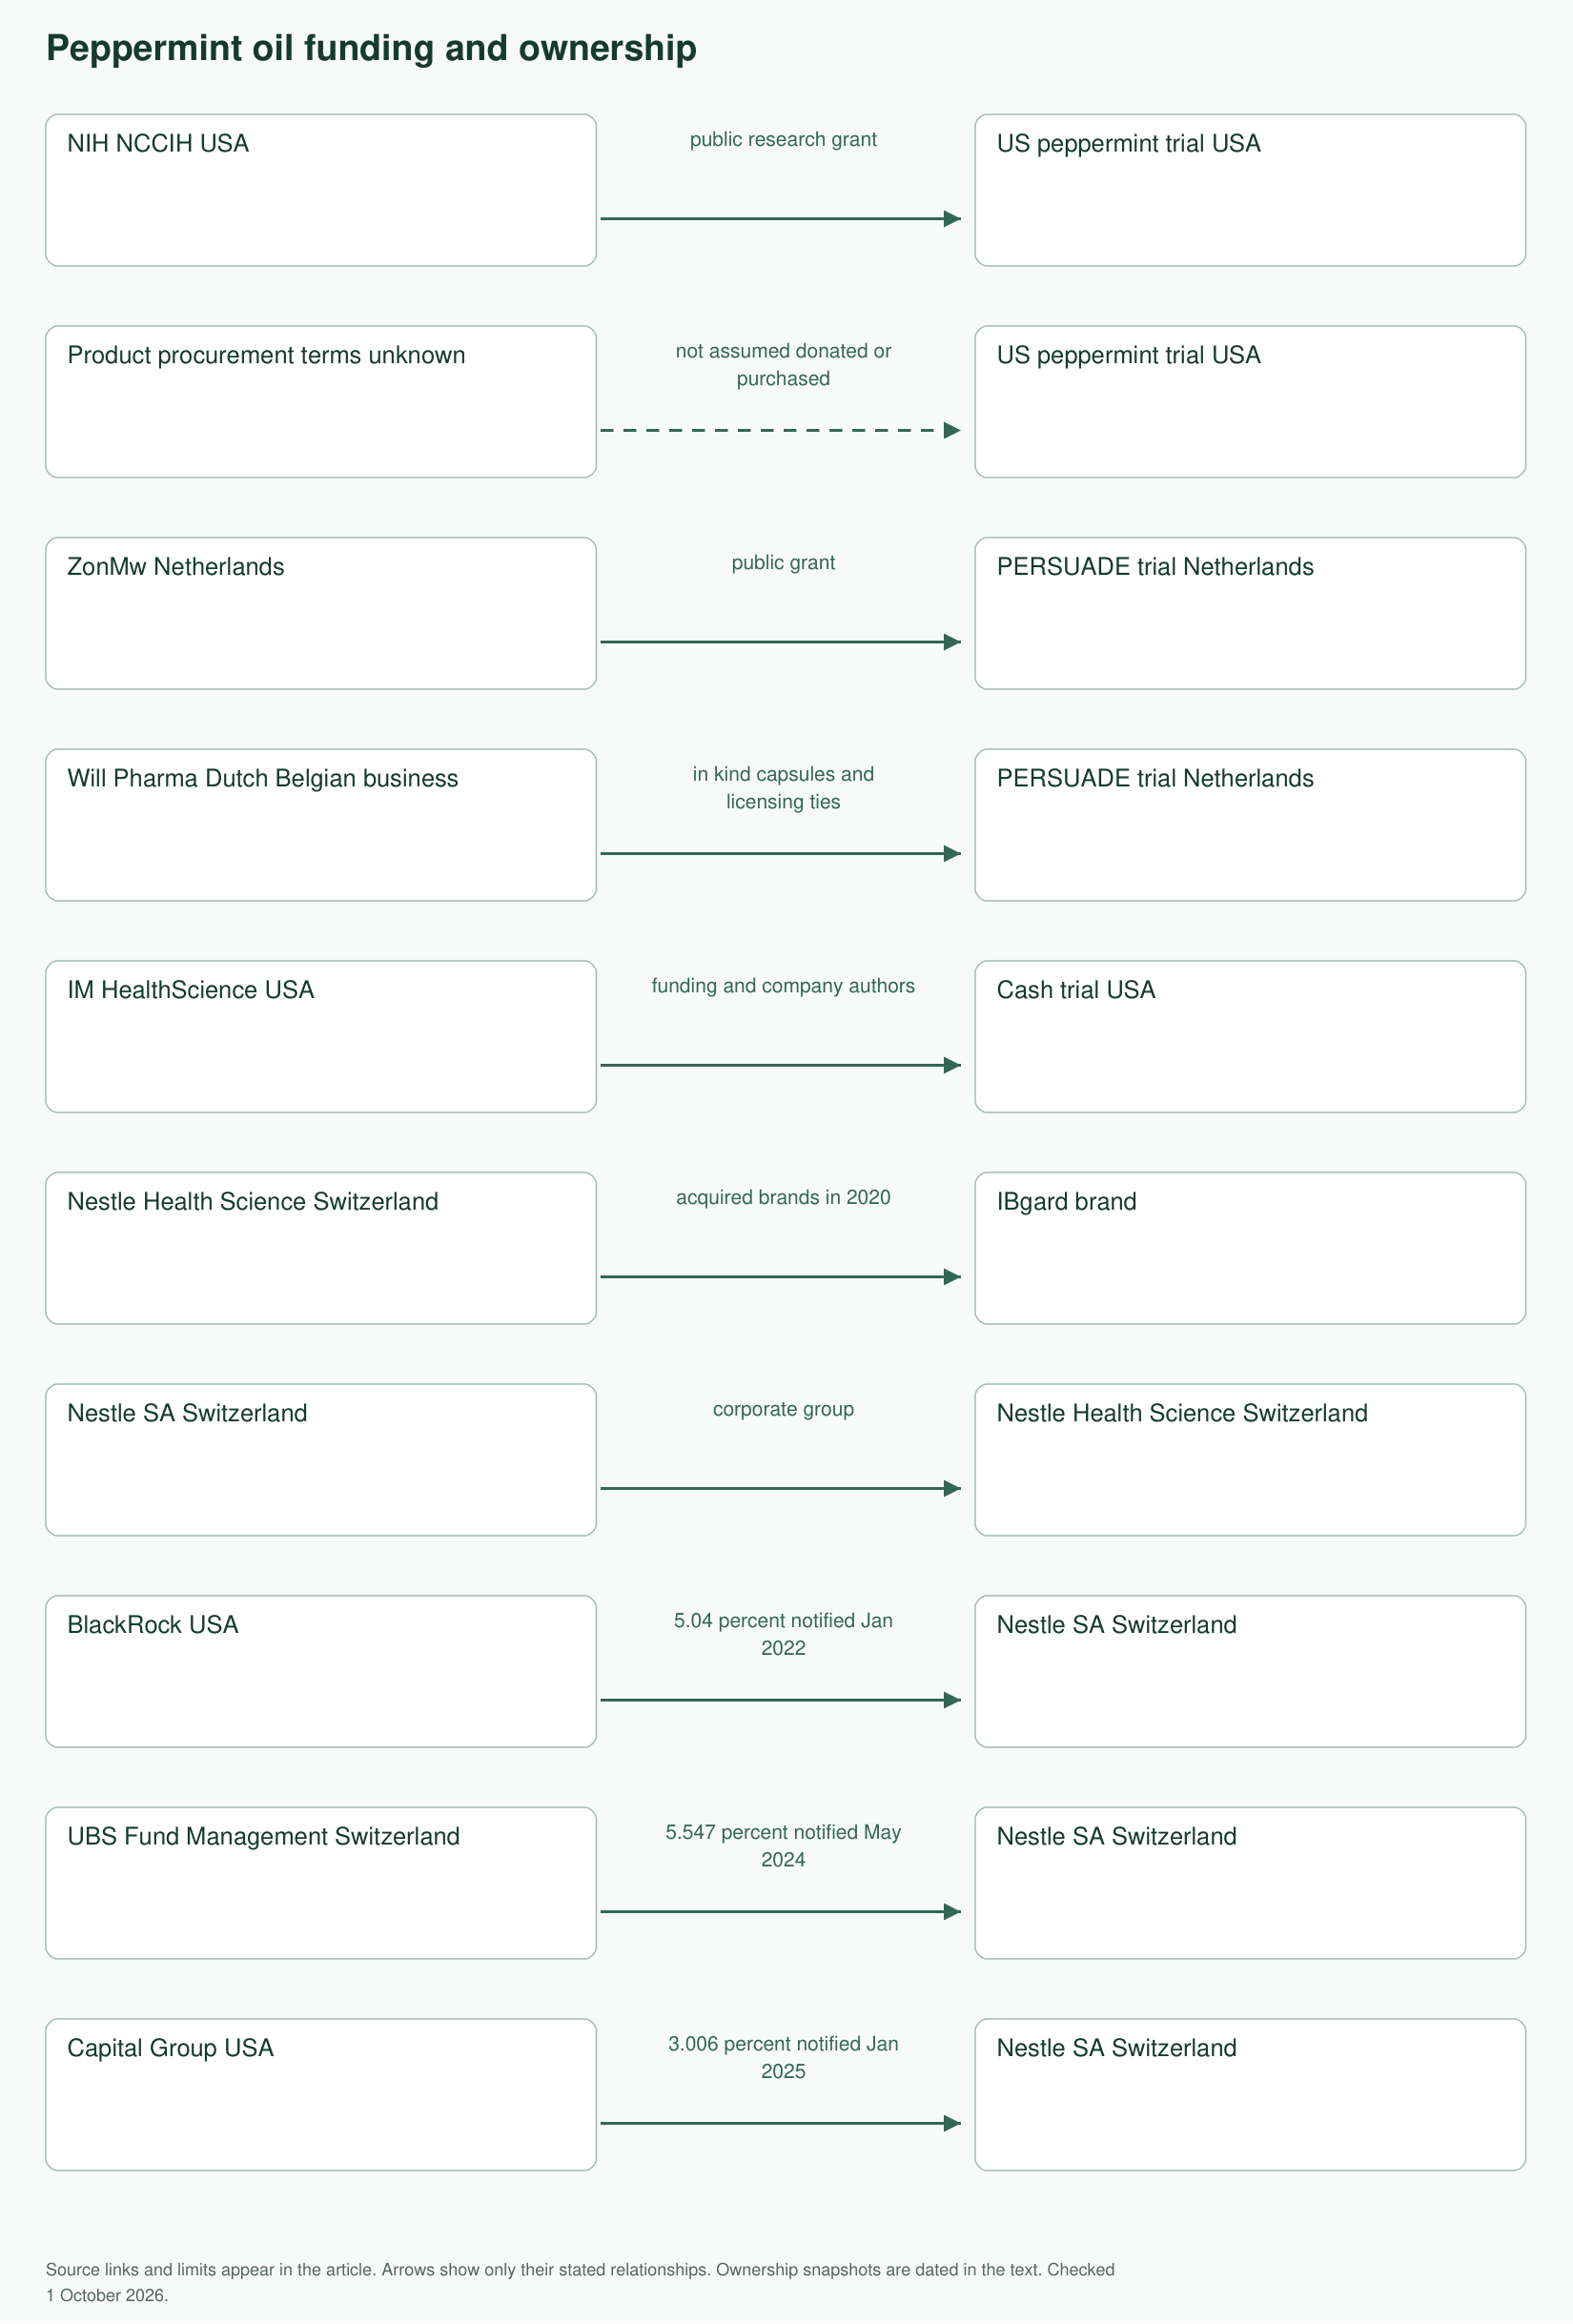
Plain-text version:
- NIH/NCCIH in the USA funded the US research program; product procurement remains unresolved
- ZonMw in the Netherlands funded PERSUADE, while Will Pharma provided in-kind capsules and held relevant commercial agreements
- US-based IM HealthScience funded the Cash trial and supplied company-linked authors
- Nestlé Health Science later acquired the IBgard business; the earlier trial is not retrospectively attributed to Nestlé
- Nestlé's report lists the dated BlackRock, UBS and Capital Group notifications above; these are corporate investments, not documented trial instructions
The trial literature spans several countries, while key product relationships in the modern studies are concentrated in US and Dutch/Belgian businesses. Nationality alone establishes neither reliability nor bias. Missing budgets, older trial disclosures and manufacturing details remain gaps. Funding is not proof of a false finding; it is relevant to the independence of corroboration.
Regulatory status
United Kingdom and European Union
The examined UK Colpermin product has a marketing authorization for IBS symptom relief. EMA has a herbal assessment for specified peppermint-oil medicinal uses; national authorities assess individual applications. Neither fact authorizes every bottle of essential oil or supplies an independent pooled treatment estimate. EMA's page also records a 2026 call for scientific data; a review process is not itself a new approval. UK label, EMA assessment record
United States
A dietary supplement is not preapproved by FDA for safety and effectiveness in the way a drug is. Disease-treatment claims and general supplement marketing operate under different rules. A study, a trademark or an ingredient label should not be represented as FDA approval to treat IBS. FDA supplement questions
Frequently asked questions
Does peppermint oil work for IBS?
There is a possible short-term benefit in the overall literature, and a conditional guideline suggestion. Modern results are mixed, and the strict independent-funding review cannot establish a dependable effect for a particular product.
Can I use peppermint tea instead?
Tea has a different composition and exposure. A preference for tea is not evidence that it reproduces a studied capsule's effect.
Why can something used for cramps worsen heartburn?
The intended lower-bowel effect does not make the same preparation suitable for the oesophagus or stomach. Reflux is a recognized adverse effect, including with some coated products.
Is the children's research positive?
The recent large Dutch comparison did not establish superiority. Its results and age-specific research protocols do not justify self-dosing children.
Does a low independent grade mean my improvement is imaginary?
No. It means this review cannot confidently attribute a predictable treatment benefit to the ingredient using the evidence eligible under its funding rule. An individual's improvement can be real while its cause remains uncertain.
Sources and funding notes
Tier 1 means no identifiable relevant financial stake after checks; Tier 2 indicates indirect ties; Tier 3 an interested party; Tier 4 direct commercial provenance or support; U an unresolved funding chain. Credibility A–D addresses accountability and interests separately from experimental design. A provisional B does not certify that undisclosed funding is independent. Manufacturer-origin labels retain their provenance even on an information host.
| Source | Funding, ownership and country | Tier / credibility | Accuracy incentive and residual gap |
|---|---|---|---|
| Ingrosso 2022 review | Academic authors in UK, Italy, USA and Canada; complete review financing/disclosures not accessible | U / B provisional | Reproducible synthesis and reputation; commercial underlying trials and very-low certainty |
| Nee 2021 | US academic trial; NIH award verified; final full disclosures and procurement unresolved | U / B provisional | Controlled design; abstract does not settle all funding questions |
| Ballou 2017 protocol | NIH/NCCIH grants, USA; no competing interests declared; commercial product sources named without payment terms | U / B provisional | Prospective methods; not a completed result or procurement invoice |
| NIH award | US federal research agency | 1 / A for grant record | Public accountability; cash award alone cannot exclude in-kind support |
| Weerts 2020 | Netherlands; ZonMw, Will Pharma in-kind products and relevant licensing agreements | 4 / C | Randomization and detailed disclosures; no independent benefit basis |
| Cash 2016 | IM HealthScience, USA, funded study; consultant and company officers authored it | 4 / C | Controlled experiment; direct commercial stake |
| Vermeijden 2026 | Netherlands; SPIN supported by Cultuurfonds; Will Pharma/Fortuin procurement terms unknown; prior Will Pharma co-funding for Keszthelyi and Benninga company consultancies disclosed separately | U / B provisional; indirect author ties | Multicenter controlled design; provision does not establish a free or discounted contribution |
| Chey 2019 | IM HealthScience financing and company roles, USA | 4 / C | Trial methods; combination cannot isolate peppermint |
| Ali 2025 case report, disclosures, PubMed record | US academic clinicians; no manuscript-preparation financial support or conflicts declared; PubMed also indexes an NIH grant | 1 / B provisional for case observation | Clinical reporting incentive; single case, multiple products, and internal reporting inconsistencies prevent firm causal or dose claims |
| Dresser 2002 | Canadian university and US AvMax affiliations; full budget and ownership chain unverified | 4 / C | Measured human pharmacokinetics; small experiment, commercially linked authors |
| Wacher 2002 | AvMax, USA; detailed financing and ultimate owners unresolved | 4 / C | Experimental methods; rat results cannot set a human interaction rate |
| ACG 2021 guideline | US professional society; no financial support reported; Chey discloses IM Health consulting and Moshiree Nestlé consulting | 3 / C | Grading and expert accountability; no industry-purified trial pool |
| NCCIH peppermint overview | US federal NIH center, public research mission | 1 / A for public guidance | Named literature and accountability; summary is not a new trial |
| NCCIH IBS guidance | Same US public institution | 1 / A for guidance | Explains limits; does not certify underlying trial independence |
| NHS common questions | UK publicly funded health service | 1 / A for practical guidance | Public safety mandate; broad advice rather than a formulation trial |
| NHS side effects | UK public health service | 1 / A | Safety accountability; cannot supply precise incidence for every product |
| NHS suitability | UK public health service | 1 / A | Triage and medicine-use guidance; individual assessment still needed |
| NHS pregnancy and breastfeeding | UK public health service | 1 / A | Public guidance; acknowledges limited data |
| NHS interactions | UK public health service | 1 / A | Explicit knowledge gaps; timing advice is not a universal compatibility study |
| Colpermin SmPC | McNeil Products, UK authorization holder; company-origin document hosted by emc; ultimate group ownership not audited here | 4 / C | Regulated label accountability; used for contents, instructions and warnings, not independent efficacy |
| EMA public summary | EU agency headquartered in Netherlands; public contributions and regulated-industry fees | 2 / A for regulatory scope | Legal mandate; assessment includes literature with commercial ties |
| EMA assessment record | Same EU agency | 2 / A for document status | Dated adopted documents distinguished from consultation |
| EMA budget program | EU public agency and fee revenue | 2 / A for institutional finance | Public budget; fee model is not evidence of a particular decision being purchased |
| FDA supplement guidance | USA; federal regulator with appropriations and agency-wide user fees | 2 / A for legal scope | Statutory accountability; not a clinical trial |
| Nestlé acquisition notice | Swiss corporate group, interested primary disclosure | 4 / C | Verifiable transaction statement; promotional language excluded |
| IBgard corporate page | Nestlé Health Science, Switzerland; product sales | 4 / D for marketing, C for identity | Commercial incentive; used to establish brand connection and stated claims |
| Nestlé 2025 governance report | Listed Swiss company; disclosed institutional investors | 4 / C | Filing accountability; dated notifications, not real-time ownership |
| Will Pharma history | Dutch/Belgian family-business self-description; exact stakes unverified | 4 / C | Public corporate identity; promotional account is not an ownership audit |
Scope: focused digestive-outcome and safety review through 1 October 2026. Older trial funding chains and inaccessible final-paper disclosures were not all resolved. No claim is made to have catalogued every peppermint product or possible interaction.
Last reviewed: 1 October 2026.
Have a question — or want us to cover something?
Ask about anything on this page, or request the next deep dive: an ingredient, a supplement, or a health concern. We use published research, evidence syntheses, and regulatory guidance, with clear source links.
One daily research roundup
Get the topics, key findings and links from our new articles in one email. At most one digest a day, only when there is something new.